



ABSTRACT:
OBJECTIVE: From a preventive perspective, this study reviewed the literature on protective factors
against depressive symptoms in high-risk children and adolescents.
METHODS: We conducted a thorough search of the PubMed, APA, EMCare, and Embase databases for
studies published between 1946 and August 25, 2023. We included only longitudinal
studies that analyzed protective factors for depressive symptoms in high-risk children
or adolescents, excluding cross-sectional studies, reviews, and pre-clinical studies.
RESULTS: A total of 29 studies with 62,405 participants were analyzed and 38 protective factors
were identified. Positive individual characteristics, family factors, peer relationships,
school-related aspects, neighborhood characteristics, and intrinsic religiosity were
associated with improved depression outcomes.
CONCLUSION: These findings have important implications for preventive strategies in this population.
Addressing protective factors can help prevent depression and enhance lifetime mental
health.
Keywords: Protective factors; systematic-review; high-risk population; depression.
FIGURES
| Received: November 08 2023; Accepted: February 23 2024 |
INTRODUCTION
According to the Global Burden of Diseases, since 1990 depressive disorders have consistently been among the top 10 causes of disability-adjusted life-years across various age groups, including people aged 10-49 years.1 In 2019, along with anxiety disorders, depressive disorders ranked among the top three causes of disability-adjusted life-years among women, highlighting their enduring impact on health burdens.1 Childhood and adolescence are particularly critical periods for brain development and the subsequent emergence of depressive symptoms.2 Approximately one in five adolescents will experience a diagnosable depressive episode by 18 years of age, which demonstrates the importance of identifying at-risk youth and mitigating the long-term impact of this disorder.3 Risk factors for mental disorders in childhood are often discussed in the literature as a combination of negative environmental exposures that typically co-occur. Early adverse experiences, such as childhood poverty, parental mental illness, family instability, exposure to violence, substance abuse or criminality, and child maltreatment are the strongest and most consistent risk factors for both depressive and anxious symptoms.4 Such experiences can disrupt parent-child attachment5 and alter the development of affect regulation and stress response systems.6
However, the significant role that protective factors play in healthy development and reducing the impact of risk factors must also be emphasized.7 These factors can be regarded as positive influences in the environment that facilitate healthy development. While they may not necessarily promote normal progression in the absence of risk factors, they can make a notable difference when risk factors come into play.8 Understanding the intricate interplay between risk factors, protective factors, and the development of depressive symptoms enhances our comprehension of depression's etiology, guiding effective prevention interventions. It is crucial to identify protective factors that promote resilience and enhance mental well-being, particularly for individuals vulnerable to depressive symptoms. Hence, this study examined the literature from a preventive perspective, focusing on longitudinal studies that investigated protective factors for depressive symptoms in high-risk children and adolescents.
METHODS
The literature search was conducted in accordance with the Preferred Reporting Items for Systematic Review and Meta-Analysis (PRISMA) guidelines - Key Items for PRISMA.9 To ensure the transparency of our methodology, the study protocol and search strategy are detailed in Supplementary Material S4. Table 1 provides a comprehensive and objective overview of our inclusion and exclusion criteria. Our focus was on longitudinal studies investigating protective factors for depression in high-risk children and adolescents (age = 18 years). High-risk criteria were defined as at least one of the following risk factors: low socioeconomic status, parental psychiatric disorders, or a history of maltreatment. We excluded studies that did not specifically explore protective factors in high-risk populations aged = 18 years. Review articles, preclinical studies, cross-sectional, case-control studies, and clinical trials were excluded.
| Inclusion criteria | Exclusion criteria |
|---|---|
| Longitudinal population studies | Review articles, clinical trials, any therapeutic or public intervention trial, pre-clinical trials, case-control studies or cross-sectional studies |
| Included individuals aged = 18 years at high-risk┼ of depression | Studies that did not specifically examine individuals at high-risk of depression OR Studies that did not examine children and adolescents (aged = 18years) |
| Studies assessing protective factors during childhood that reduced the incidence of depression | Studies that did not investigate protective factors for depression |
| Original studies published in any language |
┼ High-risk criteria (at least one of the following): 1) low socioeconomic level; 2) positive parental psychiatric history; 3) maltreatment.

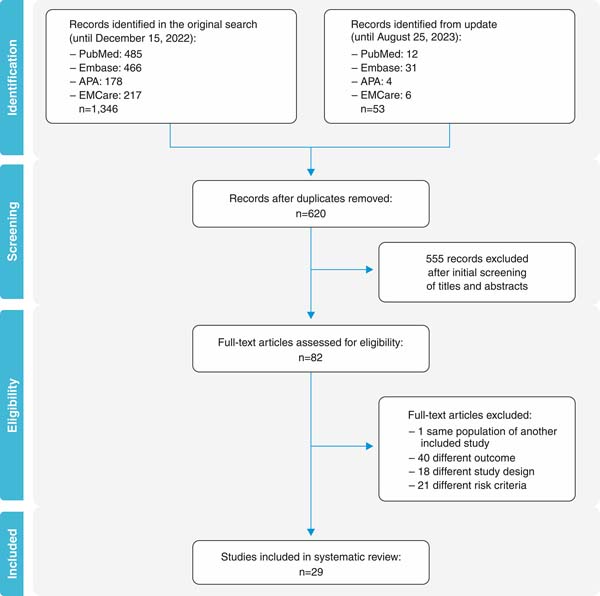
We conducted a comprehensive search of the PubMed/MEDLINE, Embase, EMCare, and APA databases for studies published between 1946 and December 15, 2022, including cohort studies in any language. When language posed a barrier, we engaged translation services to ensure inclusivity. The primary outcome was a reduced incidence or diagnosis of depressive symptoms. On August 25, 2023, we performed an updated search to ensure the most current data for our study. Six investigators were paired to independently conduct primary and secondary screening. Primary screening consisted of title and abstract assessment. PDFs of potentially eligible articles were obtained, and each pair of researchers performed an independent secondary screening. Any discrepancies during the primary or secondary screening phases were resolved through consensus.
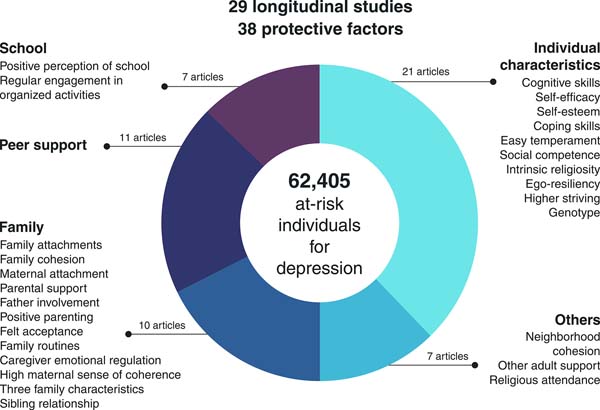
After the screening phase, the six authors were paired to systematically extract data from each article, including the sample's population type, geographical location, publication year, sample size per group, follow-up duration, sex distribution, mean baseline age, and the investigated risk factors (e.g., low socioeconomic level, parental psychiatric history, or maltreatment). We also collected details about the instruments used to measure risk and protective factors, the authors' key conclusions, and the studied outcome in each article. The outcomes ranged from depressive symptoms, diagnosis of major depressive disorder, internalizing/externalizing problems, and emotional and behavioral issues. We used this systematic approach to study outcomes due to the studies' varied depressive symptomatology assessment methods. Figure 1 is a comprehensive overview of the literature search process, and Figure 2 demonstrates the study's flowchart.


Quality assessment
The studies' methodological quality was determined using a heat map created using the Research Triangle Institute (RTI) item bank, which assesses sample size and representativeness, comparability between groups, the thoroughness of the statistical reports, and the determination of outcomes and protective factors. Further information on this process is presented in Supplementary Table S1. Each study was scored according to the number of applicable RTI items and was subsequently graded as low (0.00-0.40), moderate (0.41-0.70), or high (0.71-1.00) methodological quality/risk of bias.10 The critical appraisal was performed independently by two authors, with discrepancies resolved through discussion. We used the Grading of Recommendations, Assessment, Development, and Evaluations criteria (GRADE) to evaluate the evidence quality (classified as high, moderate, low, or very low).11 This assessment resulted in an overall score for each study. To construct the evidence map (Supplementary Table S2), we calculated the mean individual scores from each study that explored the corresponding protective factor, subsequently arranging them from low to high risk of bias.
RESULTS
We identified 29 articles, all published between 2002 and 2023, that reported a total of 38 protective factors. The number of participants per study varied from 72 to 14,694, totaling 62,405 individuals. Most of the studies were conducted in the United States (n=20), with others from the United Kingdom (n=2), Germany (n=3), Australia (n=1), Spain (n=1), Sweden (n=1), and China (n=1). The median follow-up was 4 years (interquartile range 2.06-10 years), and the mean age at baseline was 9.75 years (interquartile range 6.53-14 years). Some studies took a comprehensive approach to defining high-risk populations, considering multiple risk factors simultaneously. The most frequently employed criteria for high-risk populations in longitudinal studies were childhood maltreatment (n=13), followed by socioeconomic risk (n=12), and parental mental health problems (n=9). For detailed information on each article, see Table 2. The majority of studies received a low overall risk-of-bias score (= 40%), with a 15.70% mean overall risk of bias. The heat map, produced from RTI-bank scores, is presented in Supplementary Table S3. Of the 38 protective factors, 18 (47.36%) had high certainty of evidence according to GRADE, as shown in the evidence map in Supplementary Table S2. A comprehensive list of the protective factors is provided in Table 3.
| Author | N (% male), country | Mean age at baseline (years) ± SD (or range) | Mean follow-up time (years) | At-risk criteria(measure) | Relevant findings | GRADE evidence | |||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Outcome/depressive symptoms(measure) | Protective factor (measure) | Direction of affect | Additional information | Effect size (95%CI) | Risk of bias | Inconsistency | Indirectness | Imprecision | Publication bias | Overall certainty of evidence | |||||
| Agnafor12 | 889 (52.8), Sweden | Birth | 12 | Childhood maltreatment (LSS), parent with mental health problems (EPDS) | Internalizing and externalizing problems (CBCL) | A high maternal sense of coherence (SOC) | Protective | Internalizing B -0.05 (CI -0.08 to -0.01, p = 0.005); externalizing B -0.05 (CI -0.09 to -0.01, p = 0.005) | Very low | Very low | Very low | Very low | Very low | High | |
| Easy temperament (form created based on the concept of the "difficult child"). | Protective | Only protective for externalizing problems | Internalizing NS; externalizing B -0.14 (CI -0.21 to -0.07, p = 0.001) | ||||||||||||
| Good social functioning (CBCL) | Protective | Internalizing B -0.07 (CI -0.13 to -0.18, p = 0.001); externalizing B -0.34 (CI -0.52 to -0.16, p = 0.001) | |||||||||||||
| 5-HTTLPR genotype | Protective | Internalizing B -0.97 (CI -1.66 to -0.30, p = 0.005); externalizing B -0.84 (CI -1.61 to -0.07, p = 0.033) | |||||||||||||
| Bayer13 | 283 (53.4), Australia | 1 | 3 | Parent with mental health problems (DASS); psychosocial risk (health service screening questions assessed home violence, substance misuse and social isolation). | Internalizing and externalizing problems (CBCL) | Potentially protective aspects of maternal parenting: nurturing, appropriate developmental expectations, and low harsh discipline (PBC) | Protective | Only low harsh discipline fostered resilient child outcomes | Canonical R = 0.45; chi-square F12, 1 = 20.87, p = 0.05) | Moderate | Very low | Very low | Moderate | Low | Moderate |
| Cahill14 | 14,694 (52.3), United Kingdom | Birth | 23 | Childhood maltreatment (parent questionnaire with 87 questions about the child's exposure to 15 ACEs between the ages of 11 and 16 years) | Depressive symptoms (SMFQ) | Higher IQ (Task WISC I, II); | NS | B 1.47 (CI -0.10 to 3.04, p = 0.066) | Very low | Very low | Very low | Very low | Very low | High | |
| Easy temperament (EAS); | Protective | B 0.28 (CI 0.24 to 0.32, p = 0.001) | |||||||||||||
| Internal locus of control (PPNSIE); | NS | B 0.25 (CI -0.07 to 0.57, p = 0.127) | |||||||||||||
| High mental flexibility (stop signal); | NS | B 0.02 (CI -0.36 to 0.33, p = 0.928) | |||||||||||||
| High self-esteem (Harter's SPPC); | Protective | B 0.08 (CI 0.01 to 0.14, p = 0.033) | |||||||||||||
| High linguistic ability - reading skills and accuracy (NARA); | Protective | B 0.21 (CI 0.06 to 0.35, p = 0.008) | |||||||||||||
| High cognitive skills (15 questions answered by the mother); | Protective | B 2.75 (CI 0.97 to 4.53, p = 0.004) | |||||||||||||
| Attachment to grandparent (mother asked whether child was particularly attached to grandparent); | NS | B -0.04 (CI -0.33 to 0.26, p = 0.803) | |||||||||||||
| Sibling relationship (7 questions answered by the mother); | Protective | B 0.05 (CI 0.02 to 0.09, p = 0.007) | |||||||||||||
| High school engagement/school attendance (total number of days off school the child had taken in the last year); | NS | NS | |||||||||||||
| Positive perception of school (questions answered by the child aged 11 years 2 months and 14 years 1 month on how strongly they agreed with 7 positively stated opinions of school); | Protective | B 0.13 (CI 0.09 to 0.18, p = 0.001) | |||||||||||||
| Regular engagement in extracurricular activity (two questions answered by the mother); | Protective | B 0.54 (CI 0.26 to 0.82, p = 0.001) | |||||||||||||
| Supportive friendships (friendships questionnaire from the Cambridge Hormones and Moods Project); | NS | NS | |||||||||||||
| Engagement with religion (two questions). | NS | NS | |||||||||||||
| Carbonell15 | 102 (44.85), United States | 5 | 21 | Parent with mental health problems and psychosocial risk (FHAM) | MDD (DIS-IV) | Family cohesion (FACES-III); | Protective | t = 1.96 (p = 0.05) | Moderate | Low | Moderate | Low | Very low | Moderate | |
| Social support (ASSIS); | Protective | ?2 = 3.60 (p = 0.05) | |||||||||||||
| Positive outlook of self (TSCS on the Self-Appreciation Subscale, the RSES, and one item on the CDI "Things will work out for me okay"); | Protective | t = 4.33 (p = 0.001) | |||||||||||||
| Interpersonal relations (The Piers-Harris Popularity Subscale). | Protective | t = -1.81 (p = 0.05) | |||||||||||||
| Causadias16 | 136 (55.14), United States | 4 | 28 | Psychosocial risk (sociodemographic questionnaire) | Internalizing and externalizing problems (ASR) | Ego-control: the capacity to regulate and express emotions and feelings (CCQ); | Risk | Risk for externalizing problems | Internalizing NS; externalizing ß 0.29 (p = 0.001) | Low | Very low | Very low | Low | Low | High |
| Ego-resiliency: the capacity to adapt and be flexible in responding to situational demands (CCQ). | Protective | Internalizing ß -0.31 (p = 0.001); externalizing ß -0.26 (p = 0.05) | |||||||||||||
| Chester17 | 242 (N/A), United States | 7-15 | 1 | Psychosocial risk (sociodemographic questionnaire) | Depressive symptoms (CDI) | Peer relationship quality (BFQ); | Protective | ß -0.18 (p < 0.001) | Moderate | Low | Very low | Moderate | Very low | Moderate | |
| Positive parenting (MCQ and the short form of the IBQ). | Protective | ß -0.17 (p < 0.01) | |||||||||||||
| Cotter18 | 5,894 (49.1), United States | 11-13 | 3 | Psychosocial risk (belonging to economically disadvantaged counties) | Internalizing and externalizing symptoms (YSR) | Future optimism (Future Optimism Scale); | NS | NS | Very low | Very low | Low | Low | Very low | High | |
| Parent support (Parent Support Scale) | Protective | Prevented internalizing symptoms but did not affect externalizing symptoms. | Internalizing ß 0.975 (p = 0.01); externalizing NS | ||||||||||||
| Friend support (measured with a 5-item Likert scale) | Significantly buffered against externalizing behavior for girls only | Internalizing NS; externalizing ß 1.025 (p = 0.01) | |||||||||||||
| Teacher support (Teacher Support Scale); | NS | NS | |||||||||||||
| Religious Orientation (three-item ROS) | Protective | Significantly buffered against externalizing behavior for girls only. | Internalizing NS; externalizing ß 0.980 (p = 0.01) | ||||||||||||
| School satisfaction (School Satisfaction Scale) | Protective | Prevented externalizing symptoms for girls but did not affect internalizing symptoms | Internalizing NS; externalizing ß 0.950 (p = 0.001) | ||||||||||||
| Ethnic identity (Phinney's 6-item MEIM). | NS | NS | |||||||||||||
| Doom19 | 13,341 (50.9), United States | 15.9 | 14 | Childhood maltreatment (retrospective questionnaire about child maltreatment) | Depressive symptoms (CESD) | Striving (sum of 6 Likert-style questions about belief in hard work, school engagement, optimism, and educational aspirations). | Protective | Higher striving was also associated with lower CVD risk, higher income, and completed university | B -0.19 (CI -0.22, -0.17, p < 0.001) | Moderate | Very low | Very low | Very low | Moderate | High |
| Ezpeleta20 | 72 (56.0), Spain | 9-13 | 3 | Psychosocial risk (SRF) | Internalizing and externalizing symptoms (MAGIC) | Children's social skills and self-esteem (questionnaire); | NS | NS | Moderate | Low | Very low | Low | Moderate | Moderate | |
| Good school achievement (questionnaire); | NS | NS | |||||||||||||
| Low perception of marital discord (FHE); | Protective | OR = 0.83 (CI 0.26 to 2.59, p = 0.044) | |||||||||||||
| Family's characteristics (Family APGAR, PMS, PDS, CPIC, DAS). | NS | NS | |||||||||||||
| Gaylord-Harden21 | 393 (49.0), United States | 10-16 | 1 | Psychosocial risk (sociodemographic questionnaire) | Depressive symptoms (CDI) | Maternal attachment (IPPA) | Protective | Higher maternal attachment predicted higher active coping, which in turn predicted fewer depressive symptoms at time 2 | ß -0.299 (p = 0.001) | Low | Low | Low | Very low | Low | High |
| Coping strategies (CCSC) | Protective | Greater use of active coping strategies predicted fewer depressive symptoms for girls but not boys | ß -0.236 (p = 0.001) | ||||||||||||
| Hardaway22 | 312 (50.0), United States | 14 | 2 | Psychosocial risk (sociodemographic questionnaire) | Internalizing problems and externalizing problems (CBC and YSR) | Parental involvement (PSI) | Protective | Internalizing ß -1.47 (p = 0.01); externalizing ß 1.53 (p = 0.01) | Very low | Low | Moderate | Low | Very low | Moderate | |
| Kinship support (KSS) | Protective | Internalizing ß -1.13 (p = 0.05); externalizing NS | |||||||||||||
| Harold23 | Sample 1: 100 (0.0); sample 2: 145 (0.0), United Kingdom | Sample 1: 11.54; sample 2: 11.70 | Sample 1: 2; sample 2: 2.25 | Sample 1: childhood maltreatment (living in foster care); sample 2: parent with mental health problems (individuals with a history of recurrent unipolar depression recruited predominantly from general practices across southern Wales) | Depressive symptoms (CESD) | Maternal caregiver involvement (time they spent with their caregiver) | Risk/protective | Time with caregiver had a protective effect on initial symptoms in sample 1, but was related to increased symptoms over time in both samples | Sample 1 (T1): ß 0.28 (p = 0.01), sample 1 (T2): NS, sample 1 (T3): NS, sample 2: NS | Low | Moderate | Moderate | Moderate | Low | Moderate |
| Helms24 | 313 (56.0), United States | 17.13 | 1 | Psychosocial risk (belonging to low-income high schools) | Depressive symptoms (MFQ) | Intrinsic religiosity (DUREL Index); | Protective | ß 0.64 (p = 0.001) | Low | Very low | Low | Low | Low | Moderate | |
| Religious attendance (7-point Likert question on frequency of service attendance). | NS | Attendance was only protective when not controlling for intrinsic religiosity | NS | ||||||||||||
| Jain25 | 911 (51.0), United States | 11-16 | 7 | Psychosocial risk (My ETV) | Depressive symptoms (YSR and YASR) | Family support (PSR); | Protective | ß -0.24 (p = 0.001) | Very low | Very low | Very low | Low | Very low | High | |
| Friend support (PSR); | Protective | ß -0.08 (p = 0.05) | |||||||||||||
| Other adult support (PSR); | Protective | ß -0.10 (p = 0.01) | |||||||||||||
| Positive peer influence (10 items from Deviance of Peers); | Protective | ß -0.16 (p = 0.001) | |||||||||||||
| Time spent in structured activities (calculated based on 2 items from the school questionnaire); | NS | NS | |||||||||||||
| Neighborhood social cohesion (5 items from the community survey). | NS | NS | |||||||||||||
| Kasen26 | 126 (41.1), United States | > 6 | 20 | Parent with mental health problems (based on RDC) | MDD (DSM-III-R diagnoses) | Religious importance (questionnaire); | NS | NS | Low | Very low | Low | Low | Low | High | |
| Service attendance (questionnaire). | Protective | Attendance was protective for any mood disorder in the offspring of depressed parents | OR = 0.94 (CI 0.58 to 1.53, p = 0.05) | ||||||||||||
| Klasen27 | 1,643 (49.4), Germany | 11-17 | 2 | Parent with mental health problems (SCL-S9) | Depressive symptoms (CES-DC) | Social support (Social Support Survey); | Protective | ß -0.104 (p = 0.001) | Very low | Very low | Very low | Low | Low | High | |
| Self-efficacy (GSE); | Protective | ß -0.190 (p = 0.001) | |||||||||||||
| Family climate (FCS). | Protective | ß -0.065 (p = 0.012) | |||||||||||||
| Kliewer28 | 70 (55.0), United States | 11.15 | 0.5 | Psychosocial risk (children's exposure to community violence) | Internalizing and externalizing problems (CBCL) | Caregiver emotional regulation (Meta-Emotion Philosophy Interview); | Protective | Internalizing ß -0.29 (p = 0.001); externalizing ß -0.42 (p = 0.001) | Moderate | Low | Low | Moderate | Moderate | Low | |
| Felt acceptance (Acceptance/Rejection Subscale from the Child Report of PBI); | Protective | Internalizing ß -0.58 (p = 0.001); externalizing ß -0.55 (p = 0.001) | |||||||||||||
| Child emotional regulation (ERC) | Protective | Internalizing ß -0.41 (p = 0.001); externalizing ß -0.42 (p = 0.001) | |||||||||||||
| Caregiver-child relationship quality (observed caregiver-child interaction); | Protective | Internalizing ß NS; externalizing ß -0.30 (p = 0.05) | |||||||||||||
| Neighborhood cohesion (NCI). | Protective | Internalizing ß -0.39 (p = 0.01); externalizing ß NS | |||||||||||||
| Kuper29 | 3,374 (49.8), United States | 15 | 7 | Childhood maltreatment (retrospective questionnaire) | Depressive symptoms (CES-DC) | Verbal intelligence (age-normed Add Health PVT). | Protective | ß -0.019 (p = 0.01) | Very low | Low | Low | Moderate | Low | Moderate | |
| Kwak30 | 790 (40.9), United States | 12-16 | 3 | Childhood maltreatment (caseworkers reported maltreatment) | Depressive symptoms (CDI) | Family attachments (5 Likert-scale questions); | Protective | ß -0.062 (p = 0.01) | Moderate | Low | Low | Moderate | Moderate | Moderate | |
| Organized activity participation (open-ended question from the YSR instrument). | Protective | Participation in academic organizations was the only type of activity related to lower depressive symptoms. | ß -1.49 (p = 0.05) | ||||||||||||
| Laucht31 | 348 (48.8), Germany | 0.25 | 8 | Psychosocial risk (FAI) | Internalizing and externalizing problems (the number of problem behaviors was summed up, leading to a total problem score) | Healthy mother-infant dyads (the videotaped interactions were rated using the MRS-MII). | Protective | Children of depressed mothers had especially favorable development (and did not differ from the control group in the number of externalizing problems), if their mothers had displayed more reactivity and used more baby talk during interaction with their infants | Not available | High | Moderate | Moderate | High | High | Low |
| Markowitz32 | 8,570 (47.7) United States | 12-18 | 14 | Childhood maltreatment (retrospective questionnaire) | Depressive symptoms (CES-DC) | School connection (questionnaire about participants' subjective feelings of belongingness and support at school). | Protective | ß -0.09 (p = 0.01) | Very low | Very low | Low | Very low | Moderate | Moderate | |
| Monti & Rudolph33 | 165 (48.4), United States | 12.43 | 4 | Parent with mental health problems (Structured Clinical Interview for the DSM) | MDD (K-SADS epidemiologic version 5) | Responses to stress (RSQ) | Protective | Adaptive responses to stress (high effortful engagement and low involuntary disengagement) buffered the effect of maternal depression on initial levels and trajectories of youth depression | Effortful engagement ß 0.25 (p = 0.0); effortful disengagement NS; involuntary engagement NS; involuntary disengagement ß 0.25 (p = 0.0) | Moderate | Low | Low | Low | Moderate | Moderate |
| Oshri34 | 1,179 (42.1), United States | 12.75 | 3 | Childhood maltreatment (MMCS) | Depressive symptoms (CDI) | Caregiver-child closeness (In-Home Questionnaire); | Protective | ß -0.10 (p = 0.01) | Low | Low | Low | Very low | Low | High | |
| Peer relationships (sum of 6 self-reported items, assessing social competency and satisfaction in peer friendships); | Protective | ß -0.21 (p = 0.01) | |||||||||||||
| School engagement (7 4-item Likert-type questions); | Protective | ß -0.27 (p = 0.01) | |||||||||||||
| Positive community environment (4 3-item Likert-type questions). | Protective | ß -0.04 (p = 0.01) | |||||||||||||
| Pargas35 | 816 (48.0), United States | 15 | 5 | Parent with mental health problems (DSSI) | Internalizing and externalizing behavior problems and Youth Axis I diagnoses (Structured Clinical Interview for the DSM/YASR) | Service provision (caseworkers responded to a single, dichotomous item about service provision); | NS | NS | Moderate | Very low | Low | Low | Moderate | Low | |
| Child IQ estimate (WISC); | Protective | OR = 1.14 (CI 1.04 to 1.26, p = 0.01) | |||||||||||||
| Self-esteem (SPPA) | Protective | OR = 1.39 (CI 1.04 to 1.84, p = 0.02) | |||||||||||||
| Perceived parent-child relationship quality (CRPBI) | Protective | One factor - maternal warmth - was associated with continued high functioning (or resilience) regardless of maternal depression status | OR = 1.01 (CI 1.01 to 1.02, p = 0.02) | ||||||||||||
| Plass-Christl36 | 325 (51.2), Germany | 11-17 | 2 | Parent with mental health problems (SCL-S9) | Internalizing and externalizing problems (SDQ) | Child peer relationships and child social functioning (A semi- structured interview for adolescents was developed from earlier versions of chronic strain and functioning for adults and children of the UCLA LSI); | NS | NS | Low | Moderate | Low | Very low | Moderate | Moderate | |
| Self-efficacy (GSE); | Protective | Internalizing ß -0.12 (p = 0.001); externalizing ß -0.09 (p = 0.001) | |||||||||||||
| Social competence (5 3-item-Likert-style questions developed in the HBSC). | Protective | Internalizing ß -0.39 (p = 0.001); externalizing ß -0.13 (p = 0.01) | |||||||||||||
| Russotti37 | 260 (0.0), United States | 15.29 | 4 | Childhood maltreatment (caseworker reports) | Depressive symptoms (BDI-II) | Parental and peer attachment (the inventory of IPPA) | Protective | Maltreatment did not significantly predict depression for those with the Global High, Global Low, and Low Father profiles, possibly indicating protective effects conferred by diverse constellations of relationship quality | Parental T1 warmth ß -0.17 (p = 0.001); parental T1 control NS | Low | Very low | High | Very low | Low | High |
| Thakur38 | 943 (49.7), United States | 12 | 6 | Childhood maltreatment (retrospective questionnaire) | Depressive and PTSD symptoms (TSCC) | Family climate (German FCS) | Protective | Internalizing ß NS; externalizing ß -0.09 (p = 0.001) | Moderate | Moderate | Very low | Moderate | Low | Moderate | |
| Social cohesion (Quality of Neighborhood, Residential Stability & Organizational and Religious Affiliation Questionnaire). | NS | NS | |||||||||||||
| Wang39 | 3,426 (52.5), United States | 0 | 15 | Childhood maltreatment (CTSPC) | Depressive and anxious symptoms (CES-DC) | Family routines (Family Routines Questionnaire) ; | Protective | ß -0.02 (p = 0.001) | Low | Low | Low | Low | Moderate | Moderate | |
| Parental warmth (HOME Inventory -parental warmth subscale); | Protective | ß -0.05 (p = 0.05) | |||||||||||||
| Father involvement (mothers answered 4 questions about father's involvement); | Protective | ß -0.07 (p = 0.001) | |||||||||||||
| School connectedness (PSID-CDS-III); | Protective | ß -0.09 (p = 0.001) | |||||||||||||
| Peer relationship (PSID-CDS-III). | Protective | ß -0.13 (p = 0.001) | |||||||||||||
| Zhang40,41 | 2,288 (57.6), China | 8.15 | 6 | Childhood maltreatment (parent questionnaire) | Depressive symptoms (SDQ and MFQ) | Collective efficacy (CE-Scale); | Protective | Compared with those reporting 0 or 1 PCE, adolescents reporting 2 or 3 PCEs had significantly lower depressive symptoms and ODD, while those with 4 or 5 PCEs had more reduced depressive symptoms and ODD. The findings suggest that PCEs may mitigate the negative effect of chronic childhood maltreatment on psychopathology reported at age 14 in a dose-response manner. | ß -0.09 (p = 0.001) | Very low | Very low | Low | Very low | Very low | High |
| High parental education (socioeconomic questionnaire) ; | Protective | ß -1.70 (p = 0.001) | |||||||||||||
| High perceived SES; | NS | NS | |||||||||||||
| High parental warmth (Self-Reported Parenting Attitudes and Behaviors Scale); | Protective | ß -3.10 (p = 0.001) | |||||||||||||
| Two-parent family (socioeconomic questionnaire); | Protective | ß -2.07 (p = 0.003) | |||||||||||||
| Peer support (indicator for high peer support was the number of good friends - three or more were considered high). | Protective | ß -2.89 (p = 0.001) | |||||||||||||
ACE = adverse childhood experience; ASR = Adult Self-Report; ASSIS = Arizona Social Support Interview Schedule; BDI-II = Beck Depression Inventory II; BFQ = Best Friend Questionnaire; CBC = Child Behavior Checklist; CBCL = Child Behavior Checklist; CCQ = California Child Q-Set; CCSC = Children's Coping Strategies Checklist; CDI = Child Depression Inventory; CE-Scale = Collective Efficacy Scale; CESD = Center for Epidemiologic Studies Depression; CES-DC = Center for Epidemiologic Studies Depression for Children; CPIC = Children's Perception of Interparental Conflict; CRPBI = Children's Report of Parental Behavior Inventory; CTSPC = Parent-Child Conflict Tactic Scale; CVD = cardiovascular disease; DAS = Dyadic Adjustment Scale; DASS = Depression, Anxiety, Stress Scale; DIS-IV = Diagnostic Interview Schedule IV; DSSI = Delusions-Symptoms States Inventory of Bedford and Foulds; DUREL = Duke University Religion; EAS = Emotionality Activity Sociability Scale; EPDS = Edinburgh Postnatal Depression Scale; ERC = Emotion Regulation Checklist; FACES-III = Family Adaptability and Cohesion Evaluation Scales III; FAI = Family Adversity Index; FCS = German Family Climate Scale; FHAM = Family History Assessment Module; FHE = Family Psychiatric History Screen for Epidemiologic Studies; GRADE = Grading of Recommendations, Assessment, Development, and Evaluations; GSE = General Self-efficacy Scale; HBSC = Health Behavior in School-Aged Children Study; HOME = Home Observation for Measurement of the Environment; IBQ = Interaction Behavior Questionnaire; IPPA = Parent and Peer Attachment; IQ = intelligence quotient; K-SADS = Schedule for Affective Disorders and Schizophrenia for School-Age Children; KSS = Kinship Support Scale; LSI = Life Stress Interview; LSS = Life Stress Score; MAGIC = Missouri Assessment of Genetics Interview for Children; MCQ = Monitoring and Control Questionnaire; MDD = major depressive disorder; MEIM = Multigroup Ethnic Identity Measure; MMCS = Maltreatment Classification System; MRS-MII = Mannheim-Rating-System for Mother-Infant Interaction; My ETV = Exposure to Violence; N/A = not available; NARA = Neale Analysis of Reading Ability; NCI = Neighborhood Cohesion Index; NS = ; ODD = oppositional defiant disorder; OR = odds ratio; PBC = Parent Behavior Checklist; PBI = Parent Behavior Inventory; PCE = positive childhood experience; PDS = Parental Discipline Practices Scales; PMS = Parental Monitoring Scale; PPNSIE = Preschool-Primary Nowicki-Strickland Internal-External Control Scale; PSI = Parenting Style Index; PSID-CDS-III = Panel Study of Income Dynamics- Child Development Supplement Scale; PSR = Provision of Social Relations Instrument; PTSD = posttraumatic stress disorder; PVT = Picture Vocabulary Test; RDC = Research Diagnostic Criteria; ROS = Religious Orientation Scale; RSES = Rosenberg Self-Esteem Scale; RSQ = Responses to Stress Questionnaire; SCL- S9 = Symptom-Check List 9-item Short-version; SDQ = Strengths and Difficulties Questionnaire; SES = socioeconomic status; SMFQ = Short Mood and Feelings Questionnaire; SOC = Sense of Coherence Form; SPPA = Self-Perception Profile for Adolescents; SPPC = Self Perception Profile for Children; SRF = Schedule for Risk Factors; TSCC = Trauma Symptom Checklist for Children; TSCS = Total Self-Concept Score; WISC = Wechsler Intelligence Scale for Children; YASR = Young Adult Self Report; YSR = Youth Self Report.

| Characteristics | |
|---|---|
| Individual characteristics | |
| Significant protective factors | Non-significant or risk factors |
| [4] Child IQ estimate (internalizing and externalizing behavior problems and Youth Axis I diagnoses)/high cognitive skills (depressive symptoms)/high linguistic ability reading skills and accuracy (depressive symptoms)/verbal intelligence (depressive symptoms) | [1] Higher IQ (depressive symptoms) |
| [3] Self-efficacy (depressive symptoms 2x and internalizing and externalizing problems) | |
| [3] High self-esteem 2x (depressive symptoms and internalizing and externalizing behavior problems and Youth Axis I diagnoses)/positive outlook of self (MDD) | [1] Self-esteem (internalizing and externalizing symptoms) |
| [2] Coping strategies (depressive symptoms)/responses to stress (MDD - adaptive responses to stress, high effortful engagement and low involuntary disengagement, buffered the effect of maternal depression) | [1] Internal locus of control (depressive symptoms) |
| [2] Easy temperament (externalizing problems and depressive symptoms) | [1] Easy temperament (internalizing problems) |
| [2] Good social functioning (internalizing and externalizing problems)/social competence (internalizing and externalizing problems) | [1] Children's social skills and self-esteem (internalizing and externalizing symptoms) |
| [2] Intrinsic religiosity (depressive symptoms)/religious orientation (significantly buffered against externalizing behavior for females only) | [1] Religious importance (MDD) |
| [1] Striving (depressive symptoms) | |
| [1] Ego-resiliency (internalizing and externalizing problems) | [1] Ego-control (risk of externalizing problems) |
| [1] 5-HTTLPR genotype (internalizing and externalizing problems) | |
| [1] Ethnic identity (internalizing and externalizing symptoms) | |
| [1] Future optimism (internalizing and externalizing symptoms) | |
| [1] High mental flexibility (depressive symptoms) | |
| Parenting and family characteristics | |
| Significant protective factors | Non-significant or risk factors |
| [7] Parental involvement (internalizing and externalizing problems)/caregiver-child closeness (depressive symptoms)/parental attachment (depressive symptoms)/parental warmth x2 (depressive symptoms and depressive and anxious symptoms)/family attachments (depressive symptoms)/perceived parent - child relationship quality (internalizing and externalizing behavior problems and Youth Axis I diagnoses) | [1] Attachment to grandparent (depressive symptoms) |
| [3] Family cohesion (MDD)/family climate x2 (depressive symptoms and depressive and PTSD symptoms) | [1] Family characteristics (internalizing and externalizing symptoms) |
| [3] Maternal attachment (depressive symptoms)/healthy mother-infant dyads (internalizing and externalizing problems)/maternal caregiver involvement (time with caregiver had a protective effect for depressive symptoms initially in sample 1, but was related to increased symptoms over time in both samples) | [2] Protective aspects of maternal parenting: nurturing, appropriate developmental expectations (depressive symptoms)/maternal caregiver involvement (time with caregiver had a protective effect against depressive symptoms initially in sample 1, but was related to increased symptoms over time in both samples) |
| [2] Parent support (prevented internalizing symptoms but did not affect externalizing symptoms)/family support (depressive symptoms) | |
| [1] Father involvement (depressive and anxious symptoms) | |
| [1] Positive parenting (depressive symptoms) | |
| [1] Felt acceptance (internalizing and externalizing problems) | |
| [1] Family routines (depressive and anxious symptoms) | |
| [1] Caregiver emotional regulation (internalizing and externalizing problems) | |
| [1] Two-parent family (depressive symptoms) | |
| [1] Low perception of marital discord (internalizing and externalizing symptoms) | |
| [1] High maternal sense of coherence (internalizing and externalizing problems) | |
| [1] High parental education (depressive symptoms) | |
| [1] Sibling relationship (depressive symptoms) | |
| School, community, and relationships outside the family | |
| Significant protective factors | Non-significant or risk factors |
| [11] Interpersonal relations (MDD)/peer relationship quality (depressive symptoms)/peer relationships x2 (depressive symptoms and depressive and anxious symptoms)/child peer relationships (internalizing and externalizing problems)/peer attachment (depressive symptoms)/positive peer influence (depressive symptoms)/peer support (depressive symptoms)/friend support x2 (1 study found it protective against depressive symptoms only for girls and another found it protective for both sexes)/kinship support (internalizing problems and externalizing problems) | [1] Supportive friendships (depressive symptoms) |
| [5] Positive perception of school (depressive symptoms)/school satisfaction (prevented externalizing symptoms for girls but did not affect internalizing symptoms)/school connection (depressive symptoms)/school engagement (depressive symptoms)/school connectedness (depressive and anxious symptoms) | [1] High school engagement and school attendance (depressive symptoms) |
| [3] Other adult support (depressive symptoms)/social support 2x (MDD and depressive symptoms) | [1] Teacher support (internalizing and externalizing symptoms) |
| [3] Neighborhood cohesion (internalizing and externalizing problems)/positive community environment (depressive symptoms)/collective efficacy (depressive symptoms) | [2] Neighborhood social cohesion (depressive symptoms)/social cohesion (depressive and PTSD symptoms) |
| [2] Regular engagement in extracurricular activity (depressive symptoms)/organized activity participation (participation in academic organizations was the only type of activity that was related to lower depressive symptoms) | [1] Time spent in structured activities (depressive symptoms) |
| [1] Religious service attendance (MDD) | [2] Religious attendance (depressive symptoms)/engagement with religion (depressive symptoms) |
| [1] High perceived SES (depressive symptoms) | |
| [1] Service provision (internalizing and externalizing behavior problems and Youth Axis I diagnoses) | |
| [1] Good school achievement (internalizing and externalizing symptoms) | |
IQ = intelligence quotient; MDD = major depressive disorder; PTSD = posttraumatic stress disorder; SES = socioeconomic status.
┼ The factors are arranged according to frequency of appearance (shown in brackets) and are listed using the nomenclature they received in the respective articles. To aid comprehension, the color-coding correlates with the frequency of each protective factor; darker tones signify higher frequencies. The outcomes prevented by each protective factor are indicated in parentheses. Non-significant factors are listed beside corresponding significant factors, facilitating comparison between the frequencies of related significant and non-significant factors. Factors in italic font denote protective elements that, unexpectedly, increased the risk of depression.

Individual characteristics
Eleven studies found significant associations between 11 distinct characteristics and improved depression outcomes.12,14-16,19,27-29,33,35,36 The most prevalent protective factor, which was assessed through various measures, was intelligence and executive function, encompassing high cognitive skills,13 high intelligent quotient (IQ),29,35 verbal intelligence,29 and reading comprehension.14 Self-efficacy27,36,40 and self-esteem14,15,35 were frequently cited protective factors, each reported in three different studies. Nevertheless, one study did not find a significant association between IQ and depressive symptoms.14 Positive correlations were also observed between adaptive stress responses,28,33 easy temperament,12,14 strong social functioning,12,34,36 intrinsic religiosity,18,24 and lower depressive symptoms, while another study found an association between higher striving19 and decreased depressive tendencies. However, other studies did not find a significant association between self-esteem,20 internal locus of control,14 and depressive symptoms. Another study could not determine whether easy temperament was a protective effect against internalizing symptoms.12 One study linked ego-resiliency16 with lower depressive symptoms, while another found that a particular serotonin receptor genotype (5-HTTLPR genotype) was associated with improved mental health outcomes in high-risk children.12 Ethnic identity and an optimistic view of the future were not found to be significant protective factors.18
Parenting and family characteristics
The family environment emerged as the focal point in research on protective factors for depression in children and adolescents, being investigated across various dimensions (n = 22).12-15,17,18,20-23,25,27-29,31,35-40,42 Parental attachment was a key focus, with seven studies highlighting its preventive impact.22,30,34,35,37,39,40 Three studies emphasized the significance of maternal attachment,13,21,23 while another emphasized paternal attachment.39 Curiously, while some studies found caregiver involvement and positive parenting17 to have preventive tendencies, others found them inconclusive14 or even risk factors for depression.23 Additionally, emotional regulation and sense of coherence in caregivers emerged as influential protective factors.12,28 The overall household atmosphere was examined in three studies,15,27,36 with two applying the Family Environment Scale.43 Three studies found that feeling family support18,25 and acceptance28 was a significant protective factor. Some studies also investigated the family structure's impact on depression prevention, highlighting the protective effects of a two-parent household,40 higher parental education levels,40 and lower perceived marital discord.20 Positive sibling relationships14 and having a family routine38-40 also contributed to future mental health.
School, community, and relationships outside the family
The quality of personal relationships was investigated in 12 studies,14,15,17,18,21,25,34,36,37,39,40 with only one14 failing to find that supportive friendships had a significant protective effect for depressive symptoms. Five studies found a significant protective association between positive school experiences and depressive symptoms.14,18,32,34,39 Notably, one study found that a positive perception of school had a significant protective effect, although it did not find the same association for high school engagement or school attendance.14 Two studies found that regular participation in extracurricular activities had a protective effect,14,30 while another found it had no effect.25
Experiencing support,15,27 particularly from individuals outside the immediate family,25 was found to be a protective factor. However, one study found that supportive friendships had no significant protective effect,14 and another found no significant impact from teacher support.18 Neighborhood social cohesion was found to be a protective factor in three studies,28,40,42 but not in two others.25,38 Similarly, there were mixed results for attending religious services, with a significant protective effect found in one study26 but not in two others.14,24 In addition, service provision,35 perceived high socioeconomic level,40 and strong academic performance20 were not found to be significant factors.
DISCUSSION
This comprehensive review of longitudinal studies on protective factors for depression in children and adolescents found a wealth of positive influences that can improve depression outcomes among high-risk children and adolescents. By understanding and addressing these factors, we could pave the way for more effective mental health promotion for vulnerable youth.
While certain protective factors, such as IQ, temperament, intrinsic religiosity, or genotype, may be inherently non-modifiable, the majority of our findings suggest that targeted programs could influence various protective factors. Interventions emphasizing the development of self-efficacy and healthy coping strategies have demonstrated positive effects on overall well-being in children and adolescents.44,45 Notably, increased self-efficacy, reflecting a belief in personal competence and stress management abilities,46 has proven to be a protective factor for mental health,47 particularly in the context of major depression.48 Of note, a number of individual characteristics were not found to significantly protect against depression in our review. This might be attributable to a deficiency in positive intrinsic characteristics among high-risk individuals, leading to dependency on the environment for support. For instance, maltreated children may have lower self-esteem, self-efficacy, and IQ scores.49-51
Low IQ has been recognized as a risk factor for depressive symptoms across various clinical and population samples.52,53 Consequently, it is reasonable to expect that individual traits linked to higher cognitive capacity, such as higher IQ, advanced cognitive skills, and superior reading comprehension, would be protective factors against the onset of depressive symptoms in our study.14,19,29,35 While one study found no significant relationship between overall IQ scores and resilience, it did find that other measures of cognitive abilities, such as high cognitive skills and advanced linguistic abilities were protective factors, which could suggest bias in its testing methodology.14 Nevertheless, intelligence has been associated with emotional and behavioral regulation, greater inhibitory control, better problem-solving skills, and effective communication abilities, enabling individuals to cope with stressors in ways that may reduce depressive symptoms in adulthood.29,54,55
Cross-sectional studies have consistently shown positive health outcomes for children raised in functional families, characterized by close emotional relationships between parents and children, mutual support, and quality time together.56-59 Our review further corroborated these findings, despite the heterogeneous measurement of family environments. A more structured and cohesive family environment clearly appears more protective, including a lower incidence of depression in the children of actively involved parents with greater emotional regulation. Interestingly, one study indicated that spending more time with a mother who has mental health issues increased the likelihood of depression during follow-up. This shows the significance of interventions that attempt to lower the risk of depression in children by preventing and treating mental disorders in their parents. Such interventions should focus on increasing parental attachment, promoting positive parenting techniques, and developing parental emotional regulation skills, as well as effectively treating those in need of mental health support.
Several studies in our review found quality peer relationships to be especially protective for depressive symptoms, in addition to a positive perception of school. These findings align with the results of cross-sectional studies on the significance of positive friendships, particularly during adolescence.60 Interventions in school settings that nurture peer relationships could yield additional benefits, simultaneously enhancing both the school environment and peer support. These dual benefits could have an additional preventive effect against depression. A systematic review investigated positive school experiences within a broader concept of school connection,32,39 finding that a higher level of school connectedness in children and adolescents predicted lower depressive and/or anxiety symptom levels in both population-based and intervention studies during adulthood.61
The results for participation in structured activities were inconsistent, with equal numbers of studies finding it protective or not. This may have been because other related aspects, rather than the extracurricular activities themselves, helped prevent depressive symptoms. A parallel observation was made by Cahill et al.,14 i.e., a positive perception of school had a protective effect in a population of maltreated children and adolescents, although high school engagement and attendance did not have a significant effect. Also of note, a large study of children at psychosocial risk did not find teacher support to be significantly protective, while other types of support were.18 It is possible that teachers in socioeconomically deprived areas are less available to provide emotional support, leading students to seek help from other sources.
Although another review found that positive neighborhood factors have a protective effect on mental health,62 our findings were inconsistent. This may stem from two studies which found that in participants at risk of maltreatment, neighborhood connection was a protective factor.40,42 Nevertheless, individuals at psychosocial risk may not experience as much benefit from their community regarding depressive symptoms, as indicated by other studies.25,38 Given the ample evidence that a child's neighborhood can be a protective63 or a risk factor64 for mental health outcomes, more studies with high-risk children should be conducted to determine how positive neighborhood traits influence risk factors like maltreatment and psychosocial risk.
Religiosity contributed to resilience against depression, reflecting the findings of studies on maltreated children, i.e., that religiosity has a protective effect for internalizing and externalizing symptomatology.65 Notably, higher rates of spiritual/religious well-being seem to reduce the likelihood of depressive symptoms and risk-taking behaviors in children and adolescents.66 However, the effect of attending religious services was inconclusive in our review, with two papers finding non-significant results. Interestingly, one study found that attending religious services had a protective effect, while religious importance did not.26 This discrepancy may stem from context; the study that found service attendance to be a protective factor focused on the children of parents with mental health issues, while the studies that did not find it effective targeted populations with psychosocial and maltreatment risk. This suggests that children with mentally ill parents may find solace in a structured religious environment, potentially experiencing greater protection against depression than populations in disadvantaged communities or victims of maltreatment.
Given the significance of various protective factors in preventing depression, it may be worthwhile to explore an approach that considers the cumulative effect of these preventive factors, as in Zhang et al.41 Their study, which involved a sample of 2,288 high-risk individuals, found that children with two or three positive childhood experiences had better outcomes than those with zero or one, regardless of the specific nature of the positive experiences. Previous research highlights this quantitative balance, indicating that cumulative positive childhood experiences can counteract risk factors, regardless of the specific quality or type of positive experience, contributing to improved outcomes.67 Consequently, it may be advantageous to shift the focus from providing singular, advantageous experiences to promoting a diverse array of positive experiences that align with individual, family, and cultural contexts.56
To our knowledge, this is the first review of longitudinal studies in high-risk children and adolescents with a preventive perspective. However, we encountered limitations due to the prevailing focus on illness in the literature, resulting in a predominance of pathology-oriented research and a scarcity of studies on protective factors and resilience. The diverse methods used to assess depressive symptoms, along with innovative statistical approaches, impeded meta-analysis, preventing a reliable quantitative comparison of effect sizes for distinct protective factors. Moreover, the heterogeneity arising from diverse methodologies, populations, and evidence quality levels complicated synthesis of the results and restricted our ability to draw definitive conclusions. It should be pointed out that manual searches were not included in our search methodology, thus relevant manuscripts may have been overlooked. Additionally, publication bias, favoring studies with positive or significant results, could have influenced overall interpretation of the evidence. Furthermore, although our study was not registered in PROSPERO, our comprehensive study protocol is available in the Supplementary Material to ensure methodological transparency.
In conclusion, the prevalence of depression and its impact on individual lives and functioning make it a significant public health concern. Early identification of potential protective factors is crucial, since effective interventions in high-risk children and adolescents can prevent adverse mental outcomes in adulthood. By promoting protective factors and providing appropriate support, we can improve lifelong mental well-being and overall quality of life. Shifting our perspective to protective factors and embracing a mental health-oriented approach could prove pivotal for high-risk individuals, fostering a more comprehensive, proactive, and effective approach to mental health care.
ACKNOWLEDGEMENTS
This study was financed in part by the Coordenação de Aperfeiçoamento de Pessoal de Nível Superior - Brasil (CAPES) - Finance Code 001. ICP is a Conselho Nacional de Desenvolvimento Científico e Tecnológico (CNPq) research fellow.
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



