



ABSTRACT:
OBJECTIVE: To investigate, using functional magnetic resonance imaging (fMRI) techniques, the
immediate and sustained effects of acupuncture on functional connectivity (FC) within
the default mode network (DMN) and external FC.
METHODS: Thirty healthy participants received acupuncture needle stimulation at Baihui (GV20)
and Yintang (GV29) and underwent resting-state fMRI scans in three phases: pre-needle
insertion, during needle retention, and post-needle removal. Each phase lasted 20
minutes.
RESULTS: In terms of within-network connectivity of the DMN, post-needle removal scans showed
a decrease in FC between the medial prefrontal cortex (mPFC) and the angular gyrus
(ANG) compared to pre-needle insertion scans. The FC analysis from seed points to
whole-brain voxels showed the following changes: compared to pre-needle insertion
scans, acupuncture needle insertion increased the FC between the posterior cingulate
cortex/precuneus (PCC/PCU) and Cerebellum_8_L; acupuncture needle withdrawal increased
the FC between the PCC/PCU and Cerebellum_8_L; acupuncture needle insertion decreased
the FC between ANG and Frontal_Sup_Medial_L; and acupuncture needle withdrawal decreased
the FC between ANG and Frontal_Sup_Medial_L.
CONCLUSION: These results suggested that acupuncture has an impact on the DMN and that these effects
are sustained, not just immediate.
Keywords: Acupuncture; default mode network; functional connectivity; immediate effect.
FIGURES
| Note: How to cite this article: Wang X, Huang T, Lei H, Cui Q, Wei W, Lin H. Immediate and sustained effects of acupuncture on the default mode network. Braz J Psychiatry. 2025;47:e20254202. Epub 2025 Sep 29. http://doi.org/10.47626/1516-4446-2025-4202 |
| Received: March 2 2025; Accepted: July 28 2025 |
INTRODUCTION
Originating from China, acupuncture has been clinically employed for two millennia in managing neurological and psychosomatic disorders.1,2 Despite its historical prevalence, its effects on brain regions remain poorly characterized. The emergence of functional magnetic resonance imaging (fMRI) technology has provided a non-invasive method for studying brain networks.3 It has also provided new research methods for the study of acupuncture theory. fMRI based on the blood oxygen level dependent (BOLD) technique has been widely used in research concerning vision, hearing, and higher cognitive functions, such as thinking and emotions. It has become an important tool for studying the functional activities of the human brain's higher cortical areas.4 -6 Notably, a fMRI study demonstrated that 6-week electroacupuncture regimens modulate default mode network (DMN) activity in treatment-naive depressive patients.7 Nevertheless, critical methodological challenges persist regarding fMRI-acupuncture integration, particularly the safety of fMRI scans during acupuncture and the immediate and sustained effects of acupuncture.
Acupuncture has been found to have significant effects on brain regions, as supported by research utilizing various neuroimaging techniques, including fMRI.8,9 Previous studies consistently demonstrate that acupuncture interventions lead to alterations in brain activity in regions involved in pain processing, emotional regulation, and cognition,8 such as the insula, anterior cingulate cortex, prefrontal cortex, and limbic system structures.10,11 The observed changes suggest that acupuncture engages a complex network of brain regions that contribute to the therapeutic effects of this ancient healing practice.
The DMN is a collection of brain regions that are active when an individual is not engaged in any specific task or is at rest.12 The three core brain regions of the DMN that are widely acknowledged are the posterior cingulate cortex/precuneus (PCC/PCU), the medial prefrontal cortex (mPFC), and the angular gyrus (ANG).13,14 DMN is known to play a crucial role in various cognitive and emotional processes.15,16 Its primary functions include self-reflection and introspection.17 The DMN is involved in self-referential thinking, allowing individuals to evaluate their own thoughts, desires, and emotions; it enables spontaneous thoughts and mind-wandering, which contribute to creativity, problem-solving, and personal insight18; plays a role in processing social information, such as understanding the perspectives of others, empathy, and theory of mind19; is involved in consolidating and integrating information from past experiences, contributing to long-term memory formation and retrieval20; and interacts with other brain networks, such as the limbic system, to regulate emotional responses and self-referential emotional processing.21
Several studies have observed that acupuncture can modulate the DMN in various ways. For example, acupuncture has been found to bring about changes in DMN activity and connectivity, leading to improved cognitive functions and decreased symptoms in conditions such as depression, anxiety, and chronic pain.22-24 These findings suggest that acupuncture may exert its therapeutic effects partly through modulating the DMN. By influencing the DMN, acupuncture may help restore balance in brain activity and promote overall well-being.
It has been reported that a combination of acupoints can activate a wider range of brain areas compared to using a single acupoint.25 Acupoints GV20 (Baihui; located at the intersection of the midline of the top of the head and a line connecting the apices of the two ears) and GV29 (Yintang; located at the midpoint of the line connecting the two eyebrows), both belonging to the governing vessel, are frequently used in combination to enhance brain function,26 for example, in depression-like behavior27 and posttraumatic stress disorder.28 Therefore, GV20 and GV29 were selected as the acupoints to investigate the effects of acupuncture on brain areas in this study. Additionally, we explored whether acupuncture has a lasting effect. Specifically, does the brain continue to respond to acupuncture stimulation after it ends, or does the brain immediately cease responding to acupuncture stimulation after it ends?
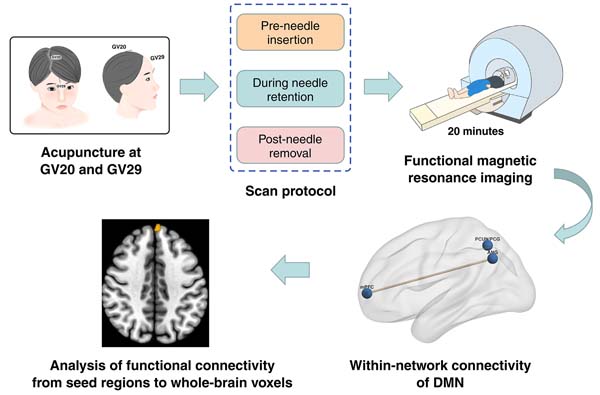
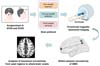
In summary, this study addressed safety and patient care concerns during the acupuncture process by utilizing fMRI to examine the immediate and sustained effects of acupuncture and its impact on the brain's DMN (Figure 1, Supplementary Table S1).
METHODS
Participants
A total of 30 healthy participants were recruited for this study. The recruitment process took place in the community of Guangzhou from January 2022 to June 2023. Two experienced psychiatrists conducted clinical interviews to confirm the mental health status of the participants. The results of the structural MRI scan were normal for all participants, and all signed informed consent forms. All participants received a comprehensive explanation of the research protocol, and their personal information was kept confidential.
Inclusion and exclusion criteria
Inclusion criteria
Participants were in good physical health, without any acute or chronic illnesses, and right-handed. Furthermore, they were required to have a sound mental state. Participants were required to meet the following criteria: i) Self-rating Depression Scale (SDS) score < 53; ii) Self-rating Anxiety Scale (SAS) score < 50; iii) Pittsburgh Sleep Quality Index (PSQI) score < 6; iv) Beck Depression Inventory (BDI) score < 14; v) age between 18 and 35 years; both genders were eligible; and vi) be able to complete the questionnaires and sign the informed consent form independently.
Exclusion criteria
Prospective participants who meet any of the following criteria were excluded from the trial: i) clinical diagnosis of depression, previous psychiatric disorders, or organic mental disorders; ii) any serious illness affecting the brain, liver, heart, kidneys, hematopoietic system, etc.; iii) pregnant or lactating women; iv) taking any medication during the trial; v) known alcohol or substance dependence; vi) current participation in other clinical trials; vii) history of adverse reactions to acupuncture or known allergies to needle puncture; and viii) presence of surgical scars, skin infections, skull defects, or any condition which would affect treatment at the acupuncture sites.
Participants with absolute contraindications for MRI (cardiac pacemakers or metal prosthetic heart valves, coronary artery bypass grafts, or vascular metal hemostatic clips; implanted or wearable ferromagnetic or electronic devices, such as cochlear implants, dynamic electrocardiograms, cardiac monitors, insulin pumps) and relative contraindications for MRI (internal metallic implants, such as artificial joints, fixed steel plates, metal dentures, intrauterine devices) were also excluded.
Furthermore, participation in the study was discontinued if participants developed claustrophobia during the scanning process or exhibited excessive movement during the scanning process, leading to the presence of image artifacts.
Acupuncture manipulation
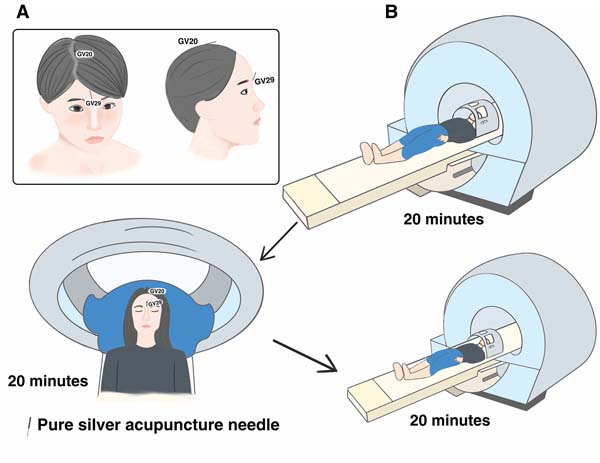
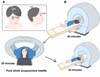
Pure silver acupuncture needles (dimensions: 0.40 mm × 25 mm) produced by Suzhou Medical Supplies Co., Ltd (Suzhou, China), were used for the study. The participants were placed in a supine position with the acupuncture site fully exposed. After local disinfection of the acupoint, the GV20 point was needled directly upward at the midpoint of the anterior hairline, 5 cun in length (a "cun" is a unit of measurement for acupuncture. According to the method of measuring based on the bones, the length between the hairline at the two frontal angles is 9 cun), and then inserted 0.5-0.8 cun posteriorly. The GV29 point was needled by pinching and inserting the needle 0.5-0.8 cun from top to bottom in the middle of the forehead, between the eyebrows (Figure 2A).
Resting-state functional magnetic resonance imaging scanning
Healthy volunteers underwent a 20-minute resting-state fMRI scan prior to acupuncture needle insertion as a baseline control. Then, a custom-made pure silver acupuncture needle was used for the acupuncture intervention, and the volunteers underwent a second 20-minute fMRI scan with the acupuncture needle in place. Following the scan, the acupuncture needle was removed and a third 20-minute fMRI scan was performed (Figure 2B). Details can be found in the Supplementary Material.
Image preprocessing
Within-network connectivity
The preprocessing steps included discarding the first 10 time points, head motion correction, spatial normalization (using echo planar imaging [EPI] registration),29 detrending, filtering (0.01-0.08 Hz), and regression of covariates (white matter, cerebrospinal fluid signals, and 24 head motion parameters [Friston 24]).
Seed-to-whole-brain functional connectivity (FC) analysis
The preprocessing steps included discarding the first 10 time points, head motion correction, spatial normalization (using EPI registration), smoothing (using a 6mm full width at half maximum kernel), detrending, filtering (0.01-0.08 Hz), and regression of covariates (white matter, cerebrospinal fluid signals, and 24 head motion parameters [Friston 24]).
Statistical analysis
Within-network connectivity was analyzed using MATLAB to perform statistical analysis on the FC of three regions of interest (ROI). A repeated measures analysis of variance was conducted to examine whether there were significant differences in FC values across the three time points, followed by false discovery rate (FDR) correction (cluster level, voxel p < 0.001, cluster p < 0.05). Seed-to-whole-brain FC analysis was conducted using Statistical Parametric Mapping (SPM) version 12 to perform statistical analysis on three groups of FC. A repeated measures analysis of variance was utilized to examine whether there were significant differences in FC values across the three time points, followed by familywise error rate (FWE) correction (cluster level, voxel p < 0.001, cluster p < 0.05). The brain segmentation template used was Anatomical Automatic Labeling 116 (AAL116).
Ethics statement
This study was reviewed and approved by the ethics committee of the Affiliated Brain Hospital of Guangzhou Medical University (approval number AF/SC-08/02.3). All participants provided informed consent to participate in the study.
RESULTS
Demographic and clinical data
All 30 participants included in the study completed the three scanning sessions, with no withdrawals due to excessive head motion or claustrophobia (Table 1).
| Characteristics | Frequency/mean ± SD |
|---|---|
| Gender (male/female) | 15/15 |
| Age (years) | 23.13±2.67 |
| Education (bachelor's degree/master's degree/doctoral degree) | 18/11/1 |
| Body mass index (BMI) | 21.94±3.71 |
| Beck Depression Inventory II (BDI-II) | 1.90±2.06 |
| Self-Rating Depression Scale (SDS) | 31.83±5.07 |
| Self-Rating Anxiety Scale (SAS) | 32.57±4.47 |
| Pittsburgh Sleep Quality Index (PSQI) | 4.07±1.48 |
Gender and education shown as absolute frequencies. Other data expressed as mean ± SD.

Within-network connectivity of default mode network
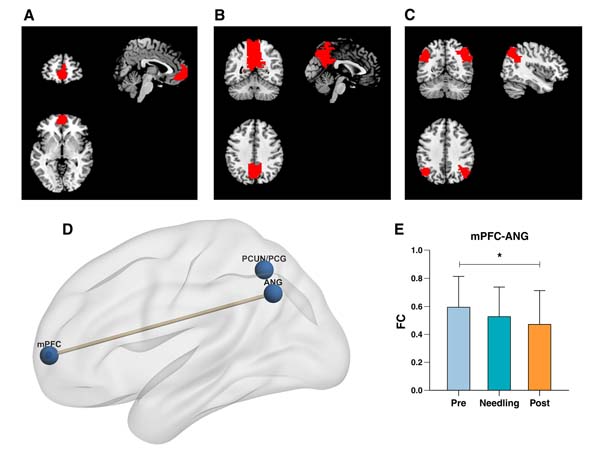
Three core regions of the DMN were selected: the mPFC, the PCC/PCU, and the ANG. ROI1 was set as the mPFC (Figure 3A), ROI2 as the PCC/PCU (Figure 3B), and ROI3 as the ANG (Figure 3C). After extracting the average time series of three ROIs from the preprocessed functional data, pairwise Pearson correlation coefficients were computed between each pair of ROIs. These correlation coefficients were then transformed using Fisher's Z transformation to obtain FC values. The higher the FC value, the stronger the functional connection between the two brain regions. The analysis revealed significant differences in FC values between ROI1 and ROI3 across the three repeated measurements (Supplementary Table S2). The significance of these differences remained even after the FDR correction, as shown in Figure 3D (ROI1-ROI3, p = 0.01). There were no significant differences observed in the three groups for FC values between ROI1 and ROI2 (p = 0.08). Similarly, there were no significant differences observed in the three groups for the FC values between ROI2 and ROI3 (p = 0.50).
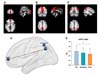
Based on the significant differences observed in the FC values between ROI1 and ROI3, further post-hoc analysis was conducted. The results of the pairwise t-tests are presented below: FC between the mPFC and ANG showed a decrease during the scan with the acupuncture needle in place compared to before acupuncture needle insertion, but the difference was not statistically significant (p = 0.12). After acupuncture needle removal, there was a statistically significant decrease in FC between the mPFC and ANG compared to before acupuncture needle insertion (p < 0.01). When comparing the post-needle removal scans with the scans with the acupuncture needle in place, there was a decrease in FC between the mPFC and ANG, but the difference was not statistically significant (p = 0.15). These findings indicate that the FC between the mPFC and ANG decreases after needle insertion and continues for some time (Figure 3E and Supplementary Table S2).
Analysis of functional connectivity from seed regions to whole-brain voxels
The FC values between the seed points and whole-brain voxels were computed and transformed using Fisher's Z transformation. The seed points selected were mPFC, PCC/PCU, and ANG. For mPFC, a repeated measures analysis of variance was conducted on the three groups of data, and the results were subjected to cluster-level FWE correction (voxel p < 0.001, FWE cluster p < 0.05). However, no significant results survived the correction.
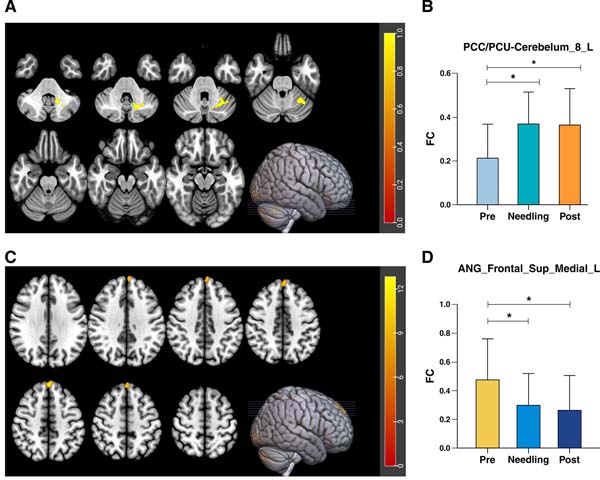
For PCC/PCU, a repeated measures analysis of variance was performed on the three groups of data, resulting in significant differences in cluster-level results. These survived FWE correction (voxel p < 0.001, FWE cluster p < 0.05), revealing a significant difference in FC between PCC/PCU and Cerebellum_8_L (AAL) (Peak Montreal Neurological Institute [MNI] coordinate: X = -15, Y = -57, Z = -39; T value: 14.322; cluster size: 87) (Figure 4A). Post-hoc analysis involved extracting the FC values from the differing cluster regions and conducting paired t-tests among the three groups. On comparing the acupuncture needle-in-place scan with the pre-needle insertion scan, there was a statistically significant increase in FC between PCC/PCU and Cerebellum_8_L (p = 1.60 × 10⁻⁶). On comparing the acupuncture needle removal scan with the pre-needle insertion scan, there was a statistically significant increase in FC between PCC/PCU and Cerebellum_8_L (p < 0.001). On comparing the acupuncture needle removal scan with the acupuncture needle-in-place scan, there was no statistically significant difference in FC between PCC/PCU and Cerebellum_8_L (p = 0.91) (Figure 4B and Supplementary Table S3).
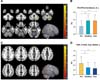
For ANG, a repeated measures variance analysis was conducted on the three groups of data, resulting in significant differences in cluster-level results. The cluster-level results passed the FWE correction (voxel p < 0.001, FWE cluster p < 0.05), revealing a significant difference in FC between ANG and Frontal_Sup_Medial_L (AAL) (Peak MNI coordinate: X = 0, Y = 45, Z = 8; T value: 13.343; cluster size: 54) (Figure 4C). Post-hoc analysis involved extracting the FC values from the differing cluster regions and conducting paired t-tests among the three groups. On comparing the acupuncture needle-in-place scan with the pre-needle insertion scan, there was a statistically significant decrease in FC between ANG and Frontal_Sup_Medial_L (p = 2.48 × 10⁻⁴). On comparing the acupuncture needle removal scan with the pre-needle insertion scan, there was a statistically significant decrease in FC between ANG and Frontal_Sup_Medial_L (p = 8.35 × 10⁻⁵). On comparing the acupuncture needle removal scan with the acupuncture needle-in-place scan, there was no statistically significant difference in FC between ANG and Frontal_Sup_Medial_L (p = 0.31) (Figure 4D and Supplementary Table S3).
DISCUSSION
Safety studies of MRI scans performed during acupuncture are rare and have attracted considerable attention. In addition, the applicability of different types of acupuncture needles to MRI has received significant attention.30 For example, Zhao Yirong et al.31 found through MRI imaging that stainless steel acupuncture needles produced significant artifacts and severe image distortion. Pure silver needles do not affect MRI imaging, but are relatively soft and require skilled acupuncture experts for manipulation, and have been previously applied in studying brain functional changes in swallowing disorders during acupuncture treatment.32 In this study, pure silver needles, which have low impact on MRI imaging and pose no hidden danger to the participants, were used, providing a solid foundation for clinical research on acupuncture. When recruiting participants, we provided comprehensive explanations, and during the clinical procedures, we ensured safety by employing a professional medical team. Upon reevaluating the participants after the acupuncture procedures, no health issues were detected, thereby providing robust evidence for the safety of similar acupuncture-fMRI trials in the future.
Regarding sustained effects after acupuncture, short-term continuous effect observation can save time for the subjects and avoid causing emotional distress while still allowing detection of sustained effects after the needle is removed. Therefore, scanning was performed immediately after needle withdrawal. These designs and findings not only emphasize the need for careful consideration of fundamental scientific questions, such as the effects and safety of acupuncture, but also highlight the importance of placing human care at the forefront in clinical research.
This was the first study to use fMRI to investigate the immediate and sustained effects of acupuncture on the DMN in the brain. Acupuncture is a traditional Chinese medical practice that involves the insertion of thin needles into specific points on the body, and fMRI has been employed to investigate its potential cerebral mechanisms of action. Previous studies suggested that acupuncture significantly modulates the cortical/subcortical brain regions involved in pain processing, cognition, and emotion regulation.33 GV20 and GV29 are the two most commonly used acupoints for brain areas. GV20 is closely associated with the brain; the name "Baihui-One Hundred Meetings" refers to the convergence of all the Yang meridians in the body. Acupuncture on the GV20 acupoint is believed to have a nourishing and tonifying effect on the brain.34 GV29, in turn, is believed to have the effects of nourishing the brain, replenishing the Yuan Qi (primordial energy), and regulating emotional well-being.35 The acupoints GV20 and GV29 are often used in combination and have proven effective in regulating brain function.36,37 Therefore, these two acupoints were chosen for our investigation of the effects of acupuncture on the DMN.
Our study concludes that, during acupuncture needle insertion, there is a decrease in FC between the mPFC and ANG compared to pre-acupuncture levels. Similarly, post-needle removal scans also showed decreased FC between the mPFC and ANG compared to pre-acupuncture levels. After acupuncture, the FC between the mPFC and ANG decreases and remains so for some time. The mPFC is a region in the frontal lobe of the brain that plays a crucial role in various cognitive and emotional processes.38,39 It is involved in self-referential processing, decision-making, social cognition, emotional regulation, and the integration of internal and external information.40 The mPFC is also associated with aspects of self-awareness, empathy, moral reasoning, and the evaluation of rewards and punishments.41 On the other hand, the ANG, located in the posterior part of the inferior parietal lobule,42 is involved in several functions related to language, attention, and multimodal sensory integration.43,44 It has been implicated in processes such as reading, semantic processing, numerical cognition, spatial awareness, and memory retrieval.45 FC between the mPFC and the ANG is important for information integration and communication between these two brain regions. This connectivity probably allows for the exchange of information and coordination of cognitive processes related to self-referential thinking, attentional control, language processing, and memory retrieval. Acupuncture may alleviate subjective discomfort by attenuating FC between the mPFC and ANG, thereby reducing maladaptive attentional bias toward negative emotional states. Besides, in healthy individuals at rest, the DMN (including the mPFC and ANG) is usually in an active state and participates in self-referential thinking, mind-wandering, or introspection.46 Acupuncture may attenuate hyperactivation of the DMN through modulation of the autonomic nervous system and neurotransmitter regulation,47-49 thereby reducing FC between the mPFC and ANG. This suppression could potentially decrease maladaptive rumination or intrusive thoughts while facilitating attentional focus or psychosomatic relaxation.
The PCC/PCU in the DMN were used as seed points for whole-brain seed-to-voxel FC analysis. We found enhanced FC between PCC/PCU and Cerebellum_8_L during the acupuncture needle-in-place scan compared with pre-needle insertion scans. Similarly, there was increased FC between PCC/PCU and Cerebellum_8_L after acupuncture needle removal compared to before acupuncture needle insertion. The PCC/PCU is involved in various cognitive processes, including attention, memory, emotion, and self-referential thinking.50,51 The PCC/PCU is part of the DMN, which, as noted above, is active during restful and internally focused states and typically deactivates during goal-directed tasks.52 Traditionally known for its role in motor coordination and balance, the cerebellum is also involved in non-motor functions, such as cognitive processing, language, and emotion53; it contributes to motor planning, error correction, sensory integration, and timing of movements.54 The functional connection between the PCC/PCU and the cerebellum facilitates communication and coordination between these regions, enabling the integration of cognitive and motor processes.
When using the ANG as a seed point for whole-brain seed-to-voxel FC analysis, we found a decrease in FC between ANG and Frontal_Sup_Medial_L during scans obtained with the acupuncture needle in place compared to pre-needle insertion scans. Similarly, compared to the scans obtained before acupuncture needle insertion, there was a decrease in FC between ANG and Frontal_Sup_Medial_L on post-needle removal scans. Frontal_Sup-Medial_L refers to the left superior medial frontal gyrus, which is located in the frontal lobe of the brain. This region is part of the prefrontal cortex and is involved in various cognitive processes and executive functions.55 The functionality of Frontal_Sup-Medial_L includes cognitive control (it plays a crucial role in cognitive control processes, such as attentional control, response inhibition, and working memory56); self-monitoring and self-awareness (allowing individuals to reflect on their own thoughts, emotions, and behaviors); metacognitive processes and introspection56,57; and has been implicated in social cognition, including understanding others' mental states (theory of mind), empathy, and moral reasoning.58,59 FC between ANG and Frontal_Sup_Medial_L plays a crucial role in information integration and communication between these two brain regions, potentially involving the aforementioned functions.
These results suggested that acupuncture at the GV20 and GV29 acupoints exhibits sustained impact, not just immediate effects. Previous studies have also found evidence of a sustained effect following electrical acupuncture stimulation at GV20.60-62 The immediate effects produced by electrical acupuncture first induce changes in somatosensory and visual areas. Subsequently, the sustained effects are characterized by greater intensity and a broader scope compared to the immediate effects.60 Our study results provide further evidence supporting the sustained effects of acupuncture. A previous study found that the sustained effect of acupuncture could alleviate and improve synaptic plasticity in chronic unpredictable mild stress rats.61 Nie JX et al.62 found that the sustained effects of acupuncture suppressed the activity of pyramidal neurons in the prelimbic cortex, normalizing the function of GABAergic and parvalbumin interneurons.
Our study also has certain limitations. First, the duration of the sustained effect remains unknown. Future studies could extend fMRI assessments to 72 hours or 1 week post-needle removal to systematically quantify the duration of sustained effects. Further scans and analyses at additional time points could be conducted to explore this problem. Second, further research is needed to investigate the effects of needling GV20 and GV29 on other brain networks.
In conclusion, this study confirmed the safety of fMRI scanning during acupuncture performed with pure silver needles; that acupuncture has an effect on the DMN; and that this effect is sustained, rather than just immediate. This study provides a safety and efficacy reference for future clinical studies on acupuncture-related brain function.
SUPPLEMENTARY MATERIALS
ACKNOWLEDGEMENTS
National Natural Science Foundation (82305420); Beijing University of Chinese Medicine New Faculty Startup Fund Project (2023-JYB-XJSJJ011); "Acupuncture Youth Elite Talent Program 2023" at Beijing University of Chinese Medicine's School of Acupuncture-Moxibustion and Tuina.
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



