



ABSTRACT:
OBJECTIVE: To develop national, evidence-based treatment guidelines for panic disorder (PD) in
Brazil through an overview of systematic reviews.
METHODS: We searched PubMed, SciELO, and Cochrane for systematic reviews (with or without meta-analyses)
of randomized controlled trials on PD (with or without agoraphobia) from 2004 to 2024.
We assessed review quality with A MeaSurement Tool to Assess Systematic Reviews, version
2 (AMSTAR 2), and graded the certainty of evidence for each outcome with the Grading
of Recommendations, Assessment, Development and Evaluation (GRADE) approach. Using
the PICO framework, we extracted response, remission, and dropout rates.
RESULTS: We identified 202 records; 84 met eligibility criteria, and nine were included (AMSTAR
2: high). Response, remission, and dropout risk were classified with GRADE. Selective
serotonin reuptake inhibitors (SSRIs), serotonin-norepinephrine reuptake inhibitors
(SNRIs), tricyclic antidepressants (TCAs), monoamine oxidase inhibitors, cognitive-behavioral
therapy (CBT), and behavior therapy showed the most favorable profiles for efficacy
and tolerability. Combining psychotherapy with antidepressants was also effective.
Benzodiazepines demonstrated short-term efficacy and tolerability but are not recommended
as first-line treatment due to dependency and long-term risk concerns.
CONCLUSION: SSRIs, SNRIs, TCAs, and CBT can be recommended as first-line interventions for PD.
Concomitant therapy may offer additional benefits. Future studies should prioritize
long-term outcomes and strategies to minimize bias.
SYSTEMATIC REVIEW REGISTRATION: PROSPERO CRD420251002430
Keywords: Panic disorder; panic attacks; anxiety disorders; treatment; guidelines.
FIGURES
| Note: How to cite this article: Baldaçara L, Veiga DL, Gaiotto LAV, Paschoal AB, Pinto AF, Almeida TM, et al. Brazilian Psychiatric Association guidelines for the treatment of panic disorder: an overview of systematic reviews. Braz J Psychiatry. 2026;48:e20254349.http://doi.org/10.47626/1516-4446-2025-4349 |
| Received: May 27 2025; Accepted: August 27 2025 |
INTRODUCTION
Panic disorder (PD) is a disabling anxiety disorder marked by recurrent, unexpected panic attacks (PA) - brief surges of intense fear that peak within minutes and involve physiological and cognitive symptoms such as palpitations, chest pain, dizziness, shortness of breath, and fears of losing control or dying.1 Persistent worry about additional attacks and avoidance of certain situations may lead to agoraphobia.1-3 PD commonly co-occurs with depression, generalized anxiety disorder, and substance use disorders, contributing to higher healthcare utilization, functional impairment, and elevated suicide risk, underscoring its public-health significance.1-3
The global prevalence of anxiety disorders - after adjusting for methodological differences - is 7.3%, ranging from 5.3% in African regions to 10.4% in Euro/Anglo regions.4 In a survey of 142,949 adults from 25 high-, middle-, and lower-middle-income countries, 13.2% reported lifetime PA, while the cross-national lifetime prevalence of PD was 1.7%; among individuals with lifetime PD, 80.4% had at least one comorbid mental disorder.5 Across countries, PD affects approximately 1.7-4.7% of adults,6 with estimates up to 4.7% in the United States.7 In Brazil, the prevalence of anxiety disorders is 19.9-27.4%,8 and the prevalence of PD is estimated at 1.1-3.6%.9,10
PD was introduced in DSM-III in 1980 after evidence showed imipramine reduced PAs.11 Early pharmacotherapies included monoamine oxidase inhibitors (MAOIs) and tricyclic antidepressants (TCAs), but adverse effects - dietary restrictions with MAOIs and tolerability issues with TCAs - limited their use. High-potency benzodiazepines offered short-term safety but poorer long-term outcomes. Current guidelines generally recommend selective serotonin reuptake inhibitors (SSRIs) as first-line treatment due to their tolerability. Contemporary care employs psychological and pharmacological approaches, alone or in combination.11-19
Although several international guidelines address the treatment of PD,14-19 Brazil has lacked an official, evidence-based national guideline. Existing national recommendations cover PD diagnosis,20 generalized anxiety disorder,21 and social anxiety disorder,22 but no formal treatment guideline for PD had been established. This manuscript presents Brazil's first national guideline, commissioned by the Brazilian Psychiatric Association, based on an overview of systematic reviews to inform evidence-based clinical decision-making for PD.
METHODS
Study design
This study is an overview of systematic reviews and follows the Preferred Reporting Items for Systematic reviews and Meta-Analyses (PRISMA) statement.
Eligibility criteria
We included systematic reviews, with or without meta-analyses, of randomized controlled trials comparing treatments for PD with or without agoraphobia, published from 2004 to 2024. Only reviews appraised as High quality on A MeaSurement Tool to Assess Systematic Reviews, version 2 (AMSTAR 2)23 were eligible. This restriction to recent, high-quality evidence was intended to reflect current methodological standards and to enable comparison of newer and older pharmacological and non-pharmacological interventions. We considered studies of adults (= 18 years) of any sex. Diagnoses followed DSM-III-R, DSM-IV, DSM-5, or ICD-10. We excluded non-systematic reviews, umbrella reviews, correctional studies, cohort studies, case reports, editorials, and any article with an AMSTAR 2 rating below high.23
Information sources
We searched PubMed (Medline), SciELO, and Cochrane using relevant subject headings ("panic disorder" AND "treatment").
Search strategy
Medical Subject Headings and free terms included: "panic disorder" OR "panic attacks" AND "treat*" OR "therapy*," "panic disorder" AND "treatment" NOT "case report," "panic disorder" AND "pharmacotherapy" OR "panic disorder" AND "psychotherapy," "panic disorder" AND "treat*," "panic disorder" AND "treat*" AND "systematic review" OR "meta-analysis." Searches covered January 1, 2004, through December 31, 2024, with no language restrictions. The last search was performed on January 3, 2025, by DLV and LAVG. Full details are provided in the Supplementary Material.
Selection and data collection process
Two review authors (DLV, LAVG) independently screened titles/abstracts and full texts. Disagreements were resolved by discussion or consultation with a third review author (LB).
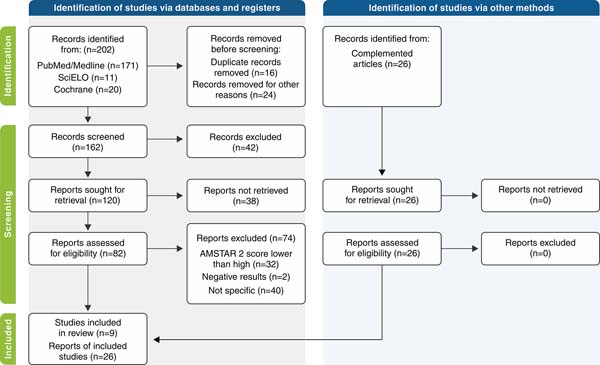
We identified 202 records. After removing duplicates (n=16) and other ineligible records (n=24), 162 records were screened. We excluded 42 at title/abstract screening and sought 120 full-text reports; 38 were excluded at this stage. We assessed 82 items for eligibility, of which 74 were excluded. Following AMSTAR 2 appraisal,23 nine articles met inclusion criteria (high). Reasons for exclusion are listed in Supplementary Table S1. Data were extracted from included reviews, and the flow of study selection is shown in Figure 1. The introduction, methods, and discussion were supplemented with 26 additional citations drawn from the bibliographies of included publications.

Data items (outcomes) and effect measures
Data were organized according to the PICO (Patient/Population, Intervention, Comparator, Outcome) framework. Primary outcomes were response, remission, and all-cause dropout, while secondary outcomes varied by review. Effectiveness was summarized using odds ratio, risk ratio, standardized mean difference, rankings from network meta-analysis, and the surface under the cumulative ranking curve.
Assessment of methodological quality and certainty of evidence
We appraised the methodological quality of the included systematic reviews and meta-analyses with AMSTAR 2,23 including only those rated high. Recommended treatments and the certainty of evidence were summarized using the Grading of Recommendations, Assessment, Development and Evaluation (GRADE) approach.
Synthesis methods
Supplementary Table S1 lists excluded articles. Domain-level AMSTAR 2 judgments are shown in Supplementary Table S2. For the included articles, Supplementary Tables S3, S4, and S5 compile key data: references, PICO items, AMSTAR 2 ratings, and pertinent notes. For evidence selection, we included only reviews rated high on AMSTAR 2.23 Strength of recommendations and certainty of evidence were assessed with GRADE.
Study registry
This study was registered with the International Prospective Register of Systematic Reviews (PROSPERO) under registry code CRD420251002430.
RESULTS
Figure 1 shows the study selection flowchart. Treatment recommendations and certainty of evidence appear in Tables 1 and 2. Study characteristics are provided in Supplementary Tables S3, S4, and S5.
| Treatment | Better chance of response | Better chance of remission | Reduced chance of dropout |
|---|---|---|---|
| SSRIs | High | High | Moderate |
| SNRIs | High | High | Moderate |
| TCAs | Moderate | Moderate | Moderate |
| CBT | Moderate | Moderate | Moderate |
| BDZ | Moderate | Moderate | Moderate |
| MAOIs | Moderate | Moderate | Moderate |
| TCAs + CBT | Moderate | Moderate | Low |
| BT | Moderate | Low | Low |
| TCAs + BT | Low | Moderate | Very low |
| 3W CBT | Low | Moderate | Moderate |
| PDT | Low | Low | Moderate |
| SP | Low | Low | Very low |
| PT | Moderate | Low | - |
| SSRIs + CBT | Moderate | Low | - |
| CT | Low | Low | - |
| TCAs + PDT | Very low | Low | - |
| BDZ + BT | Low | - | Low |
| PE | Very low | - | Moderate |
| IPT | Very low | - | Low |
| BDZ + CBT | Low | - | - |
| TCAs + SP | Very low | - | - |
| SSRIs + PDT | Very low | - | - |
- = no data; 3W CBT = third-wave cognitive-behavior therapy; BDZ = benzodiazepines; BT = behavior therapy; CT = cognitive therapy; GRADE = Grading of Recommendations, Assessment, Development and Evaluation; IPT = interpersonal therapy; MAOIs = monoamine oxidase inhibitors; PD = panic disorder; PDT = psychodynamic therapies; PE = psychoeducation; PT = physiological therapies; SNRIs = serotonin-norepinephrine reuptake inhibitors; SP = supportive psychotherapy; SSRIs = selective serotonin reuptake inhibitors; TCAs = tricyclic antidepressants.

| Class/medication | Dose (mg) |
|---|---|
| Benzodiazepines | |
| Alprazolam | 1-8 |
| Clonazepam | 0.5-6 |
| Diazepam | 5-30 |
| Monoamine oxidase inhibitors | |
| Moclobemide | 150-300 |
| Tranylcypromine | 5-30 |
| Serotonin-norepinephrine reuptake inhibitors | |
| Venlafaxine extended-release | 75-225 |
| Selective serotonin reuptake inhibitors | |
| Citalopram | 10-60 |
| Escitalopram | 5-20 |
| Fluoxetine | 10-60 |
| Fluvoxamine | 50-300 |
| Paroxetine | 10-60 |
| Sertraline | 25-150 |
| Tricyclic antidepressants | |
| Clomipramine | 10-200 |
| Imipramine | 25-250 |

Response
Antidepressants with demonstrated efficacy for PD include SSRIs (escitalopram, citalopram, fluoxetine, fluvoxamine, paroxetine, and sertraline), the serotonin-norepinephrine reuptake inhibitor (SNRI) venlafaxine, TCAs (clomipramine and imipramine), and MAOIs (moclobemide and tranylcypromine).2,11,13,24
Bighelli et al.11 reported an antidepressant number needed to treat for benefit of 7, meaning seven patients must be treated for one additional responder. Based on GRADE across response, remission, and dropout, the recommended hierarchy for response is SSRIs and SNRIs (high), TCAs (moderate), and MAOIs (moderate).2,11,13,24
Benzodiazepines - alprazolam, clonazepam, and diazepam - showed moderate certainty of evidence for response, but trials evaluated only short-term use. Because of dependence and long-term risk, use should be limited to the short term.24-26
Psychotherapies assessed for PD included cognitive-behavioral therapy (CBT), behavior therapy (BT), third-wave (3W) CBT, psychodynamic therapies (PDT), supportive psychotherapy (SP), physiological therapies (PT), cognitive therapy (CT), psychoeducation (PE), and interpersonal therapy (IPT). Evidence for a better chance of response was: CBT (moderate), BT (moderate), 3W CBT (low), PDT (low), SP (low), PT (moderate), CT (low), PE (very low), and IPT (very low).1,13,26-30
For combined therapy, evidence supported TCA + CBT (moderate), TCA + BT (low), SSRI + CBT (moderate), TCA + PDT (very low), BDZ + BT (low), BDZ + CBT (low), and SSRI + PDT (very low).13,26,27
Remission
For remission, medications with hierarchical evidence were SSRIs (high), SNRIs (high), TCAs (moderate), BDZ (moderate), and MAOIs (moderate).2,11,13,24,25 Among psychotherapies, evidence was observed for CBT (moderate), BT (low), 3W CBT (moderate), PDT (low), SP (low), PT (low), and CT (low); there were no data for PE or IPT.1,13,27,30
For medication-psychotherapy combinations, evidence supported TCA + CBT (moderate), TCA + BT (moderate), SSRI + CBT (low), and TCA + PDT (low). There were no data for BDZ + BT, BDZ + CBT, TCA + SP, or SSRI + PDT.13,27
Dropouts for any reason
For this outcome, we considered all-cause dropout as a proxy for tolerability/acceptability. Treatments associated with a reduced chance of dropout were SSRIs (moderate), SNRIs (moderate), TCAs (moderate), MAOIs (moderate), BDZ (moderate), CBT (moderate), BT (low), 3W CBT (moderate), PDT (moderate), SP (very low), PE (moderate), and IPT (low).1,2,11,24,25,27-30 For combinations, TCAs + CBT (low), TCAs + BT (very low), and BDZ + BT (low) showed benefit.13,26 There were no data for PT, CT, SSRI + CBT, TCA + PDT, BDZ + CBT, TCA + SP, or SSRI + PDT.
Time of treatment
Because the evidence is derived from clinical trials, follow-up was limited. Outcomes were assessed at 3-28 weeks,11,13,24 with the acute phase typically occurring at 8-12 weeks.13 We recommend a treatment period of 12-24 months.
Not recommended treatments
We found no supporting evidence for buspirone,2,31 repetitive transcranial magnetic stimulation,32 valerian,33 passiflora,34 and CBT with virtual reality exposure therapy.35
DISCUSSION
The evidence base for PD is heterogeneous, largely because many studies assessed multiple anxiety disorders concurrently, applied varying diagnostic criteria, or did not exclude comorbid conditions. Different instruments and analytic approaches further complicate comparisons. In this overview, we focused exclusively on PD and did not pool overlapping results given discrepancies in assessments, statistical methods, and sample sizes. When multiple independent studies supported an intervention, we treated the aggregate as evidence of efficacy.
In order to ensure methodological rigor, we used AMSTAR 2, which led to the exclusion of most identified reviews. Even among the included reviews, few outcomes were graded as high or moderate certainty; many were low or very low. We therefore emphasized the strongest available evidence across the three primary outcomes: response, remission, and all-cause dropout. We also summarized commonly recommended treatments lacking evidence and provided dosing ranges for medications.
AMSTAR 2 helped verify review quality; we then evaluated the findings reported in those reviews. Recommendations are presented to guide clinical decision-making, while acknowledging clinician discretion. We organized options by evidence tier: first line (best evidence across response, remission, and retention), second line (intermediate evidence), and third line (lowest evidence). The included reviews generally accounted for heterogeneity and risk of bias in drawing conclusions about efficacy, in accordance with AMSTAR 2 criteria. Reviews that did not adequately address these issues did not achieve a high rating.
The best evidence - by GRADE, considering all previously described variables - supports these options. The efficacy of combined therapy pairing antidepressants with CBT or BT was also demonstrated. Importantly, several assessments include overlapping clinical trials, which yield comparable outcomes.
We did not assess costs because the underlying studies are international and may not reflect the Brazilian context. Expenses vary by patients' socioeconomic circumstances, care setting (public system, health insurance, or private), and local availability of services. Accordingly, we provide multiple options to support individualized treatment.
This study has limitations: a restricted time window (2004-2024); reliance on secondary data from prior reviews; absence of cost-effectiveness evidence; limited long-term outcome data; and the exclusion of many studies due to low AMSTAR 2 ratings. Strengths include a comprehensive search strategy, a national treatment focus, and the use of a rigorous tool to appraise review quality.
In conclusion, the most supported alternatives at present are CBT, BT, SSRIs, SNRIs, TCAs, and MAOIs. Combined therapy is a viable, evidence-based option. BDZs showed efficacy and acceptable safety only in the short term. Future research should evaluate long-term outcomes of maintenance or continuation strategies and report the risk of bias, particularly selection and reporting biases.
<>SUPPLEMENTARY MATERIALS
ACKNOWLEDGEMENTS
This work was supported by the Brazilian Psychiatric Association. We thank Andrea de Abreu Feijó de Mello (ORCID 0000-0001-8498-7751, aafeijomello@icloud.com) and Marcello Feijó de Mello (ORCID 0000-0002-0475-4729, mf-mello@uol.com.br) for reviewing the final version.
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



