



ABSTRACT:
OBJECTIVE: Brain default mode network (DMN) function is altered in schizophrenia (SZ). Considering
the roles of nitrergic and glutamatergic transmission in SZ neurobiology, supplementation
with nitric oxide (NO) donors such as sodium nitroprusside (SNP) has been proposed
as a means of reducing symptoms, but results have been mixed and potential mechanisms
remain unclear. In this context, we sought to investigate the effects of SNP on DMN
functional connectivity (FC) assessed by functional magnetic resonance imaging (fMRI)
in SZ patients and healthy controls.
METHODS: In an open-label trial, participants were divided into three treatment groups to receive
intravenous SNP (0.25 µg/kg/min over 12 minutes): SZ patients on clozapine (CLZ) (n=13),
SZ patients on non-CLZ antipsychotics (n=13), and controls (n=14). fMRI data was collected
continuously before, during, and after SNP infusion. Symptom changes were evaluated
with the Brief Psychiatric Rating Scale (BPRS).
RESULTS: Considering only patient groups at baseline, there was no difference in connectivity.
When comparing all patient groups to controls, patients exhibited increased activity
in DMN subregions and increased FC in the left supramarginal gyrus. During SNP infusion,
FC was increased in the left angular gyrus; immediately following infusion, FC increased
in the bilateral medial temporal gyri and left supramarginal gyrus of patients compared
to controls. There were no significant differences between patient groups at any time
point, nor changes in symptoms.
CONCLUSION: Although our results are preliminary, this work demonstrated for the first time that
SNP modulates brain connectivity in healthy controls and patients with SZ. Future
research is warranted to confirm these findings.
Keywords: Schizophrenia; fMRI; default mode network; social cognition; sodium nitroprusside.
FIGURES
| Note: How to cite this article: Garcia GJ, Rossi GN, Dias ICS, Arcoverde E, Palhano-Fontes F, Onias H, et al. Effects of sodium nitroprusside on the default mode network of patients with schizophrenia and healthy controls. Braz J Psychiatry. Epub 2025 June 02. 2025;47:e20254187. http://doi.org/10.47626/1516-4446-2025-4187 |
| Received: February 20 2025; Accepted: May 23 2025 |
INTRODUCTION
Schizophrenia (SZ) is characterized by debilitating and incapacitating symptoms. Presenting a chronic course, the disorder usually emerges in adolescence or youth.1 The currently available antipsychotic treatments are considered unsatisfactory considering they do not address all symptoms and often produce extrapyramidal or metabolic adverse effects.2 Besides efforts being developed from a pharmacological perspective in the search for better treatments,2,3 functional magnetic resonance imaging (fMRI) reports also point out the relevance of the default mode network (DMN) in SZ.4,5
The DMN is a set of brain regions active when individuals are not performing externally guided tasks (e.g., at resting state).4 Current evidence indicates that DMN activity increases when having self-related thoughts, accessing autobiographical memories, or planning for the future. Most often, the DMN comprises the medial prefrontal cortex (mPFC), the posterior cingulate cortex (PCC), the precuneus, and parts of the parietal lobe.4,6 Interestingly, the subregions and communications of the DMN often overlap with brain areas involved in social cognition, which is the ability to interpret the emotions and mental states of others. In this context, the importance of social cognition to wellbeing cannot be disregarded, and it has been shown to be impaired in SZ.7
Studies have demonstrated an overactivated DMN and disordered brain connections both in patients with SZ and in their first-degree relatives.5,8 Researchers have hypothesized that these neural derangements are closely related to positive symptoms.4 It is also believed that such derangements in brain activity result from dysregulation of chemical neurotransmission.9,10 The dopaminergic hypothesis was long considered the main pathophysiological basis for the emergence of SZ. Specifically, in the 1960s and 1970s, studies investigated the mechanism of action of drugs with an antipsychotic effect and concluded that they were dopamine D2 receptor antagonists.2,11 Further research confirmed the relevance of this neurotransmitter in the neurobiology of SZ, although it was concluded that dopaminergic dysfunction was more likely a consequence than a cause of the disorder: "a piece of the puzzle" and not "the whole picture."2,11
Kim et al. published a pioneering study suggesting that patients with SZ had decreased levels of glutamate in their cerebrospinal fluid (CSF).12,13 Concurrent research revealed that substances such as phencyclidine and ketamine exerted their psychotomimetic effect by antagonizing glutamate N-methyl-D-aspartate (NMDA) receptors; accordingly, these NMDA antagonists were considered to produce the most reliable SZ models, able to mimic both positive and negative symptoms as well cognitive deficits.11,13 In this scenario, it seems plausible that dysfunction in glutamatergic transmission - specifically, hypofunction of NMDA receptors - precedes dysfunction of dopaminergic neurotransmission.2,3 On the other hand, later reports that did not find low glutamate levels in the CSF of SZ patients (e.g., Perry14 and Gattaz et al.15). Nevertheless, a recent and comprehensive meta-analysis reported greater variability in glutamatergic metabolites in diverse brain regions of SZ patients compared to controls, which corroborates a role of the glutamatergic system in the etiology of SZ.16 Studying the biochemistry of the NMDA receptor and its intracellular activation cascade has resulted in the emergence of new possible pharmacological targets for the treatment of SZ, such as nitric oxide (NO).3 Several studies have pointed out the relevance of nitrergic transmission in SZ neurobiology, and preclinical, biochemical, genetic, and pharmacological findings seem to support a relationship between NO underproduction and SZ and the effectiveness of the NO donor sodium nitroprusside (SNP) in reducing the behavioral alterations showcased in models of SZ.17-20 Some researchers have concluded that NMDA receptor hypofunction results in decreased NO production, which would cause the symptoms of SZ.3,20 With these findings in view, NO supplementation has been investigated clinically to evaluate this hypothesis in patients with SZ, albeit with mixed results.20-24
Considering the above, we proposed an investigation of the effect of SNP on DMN connectivity in SZ patients and healthy volunteers. We used a lower dose of SNP given over a shorter time window than in previous works: 0.25 µg/kg/min for 12 minutes of infusion. In so doing, we intended to evaluate if a faster and simpler infusion protocol would also be beneficial to patients, while also taking into consideration time constraints for use of the fMRI scanner. The chosen dosage is lower than that used in other studies with SZ patients but has still been shown to significantly reduce the psychotomimetic effects of ketamine in healthy participants.25 Considering that clozapine (CLZ) is usually administered to patients with treatment-resistant SZ, the experimental groups were divided into patients taking CLZ, patients taking antipsychotics other than CLZ (non-CLZ), and a control group of healthy volunteers. As there is evidence that dysregulation of glutamate levels may be specifically involved in treatment resistance,26 we intended to ascertain whether SNP would have differential effects on the two groups of patients (treatment-resistant and not). Through fMRI acquisition, we measured brain activity at three different time points: before, during, and after SNP infusion. We also used the Brief Psychiatric Rating Scale (BPRS) to assess possible symptom amelioration, although we did not expect changes in this variable, given that the dose and administration regime were chosen primarily for neuroimaging investigation purposes.
METHODS
Participants
Patients were recruited from an outpatient psychiatry clinic of Hospital das Clínicas da Faculdade de Medicina de Ribeirão Preto, Universidade de São Paulo (HCFMRP-USP), a university-affiliated tertiary care center in Southeast Brazil. A control group of healthy volunteers was selected from the university population (students and staff). Thirty-five patients diagnosed with SZ according to DSM-5 criteria and 15 healthy volunteers aged 18 to 50 years participated in the study. Only clinically stable patients without a history of symptom exacerbation or changes in antipsychotic doses in the preceding 4 weeks were included. Exclusion criteria included: 1) hypersensitivity to SNP; 2) comorbidities such as cardiovascular, neurological, or renal diseases; 3) diagnosis of drug dependence or abuse using DSM-5 criteria; and 4) presence of an implantable pacemaker or any metal prosthetics. All subjects were thoroughly informed of the characteristics and implications of the experiment before signing the consent form.
As noted above, patients were further divided into two groups by current antipsychotic medication: 19 patients were on CLZ and 16 patients were on other (non-CLZ) antipsychotics. To evaluate the symptoms of SZ, we used the BPRS27 translated and adapted into Portuguese,28 administered at baseline (minutes before) and after SNP infusion.
Study procedure
The study consisted of a single, continuous 24-minute resting-state fMRI (rs-fMRI) acquisition session encompassing three periods: 1) before infusion (baseline); 2) during SNP infusion; and 3) post-SNP infusion. Throughout the procedure, participants were asked to stay at rest with their eyes closed. The baseline period consisted of a 6-minute infusion of a 5% glucose solution. This was immediately followed by 12 minutes of SNP infusion (0.25 µg/kg/min), and then by 6 minutes of 5% glucose infusion to return to baseline. The procedure was identical for all experimental groups.
Image acquisition
All images were acquired using a 3.0-Tesla MRI scanner (Achieva, Philips, Eindhoven, The Netherlands) with an eight-channel SENSE head coil. T1-weighted echo gradient images were acquired for co-registration: TR = 6.7 ms, TE = 3.1 ms, flip angle = 8, acquisition matrix 7 = 256 × 256, FOV = 256 mm; volumes = 180; volume thickness = 1 mm, voxel size = 1 × 1 × 1 mm3, SENSE = 1. Echo planar imaging (EPI) was used for rs-fMRI: TR = 2,000 ms, TE = 30 ms, flip angle = 90°, acquisition matrix = 128 × 128, FOV = 230 mm, volumes = 32, volume thickness 10 = 2 mm, SENSE = 2, volumes = 180 (baseline and post-infusion), 360 (during infusion). The number of volumes per subject did not vary and no volumes were discarded for magnetic stabilization.
Data analysis
Clinical, demographic, and Brief Psychiatric Rating Scale (BPRS) data
Clinical, demographic, and BPRS data were analyzed using SPSS version 22.0. Differences were considered statistically significant when p = 0.05. For clinical and demographic data, the chi-square test was used for categorical data, and independent two-tailed t-tests were used for continuous data. A t-test for independent samples was used for between-group comparisons of BPRS scores, and a paired t-test for the within-group effects of SNP on BPRS. Levene's test was used to determine the homogeneity of variances.
Functional magnetic resonance imaging data
fMRI data preprocessing was performed in FSL 5.0 (Analysis Group FRMIB, Oxford, United Kingdom) optimized for seed voxel correlation analysis (SCA). Preprocessing steps included motion correction and slice timing correction using the mcflirt e-slice timer and smoothing with a 5-mm full width at half maximum (FWHM) Gaussian filter. Subjects with head artifacts greater than 2 mm translation or 1° rotation were excluded from analyses. All images were transformed into Montreal Neurological Institute (MNI)-152 space. We used SPM5 (Statistical Parametric Mapping, London, UK) to control spurious correlations by adding to the model 18 regressors of non-interest: six head motion parameters, CSF, white matter, and global signals and their derivatives. The residual images were then used for FC analyses.
FC was estimated using REST 1.7 (Resting-state fMRI Data Analysis Toolkit).29 Images were filtered using a temporal bandpass filter between 0.01 and 0.1 Hz. We selected two spherical seeds (10 mm radius each), one positioned in the PCC and another in the mPFC, the two hubs of the DMN. Seeds were chosen based on MNI coordinates30: left hemisphere for the PCC (-4, -47, 45) and cortex midline for the mPFC (0, 51, -14), as depicted in Supplementary Figure S1. Pearson's correlation coefficients were estimated between the mean time series of each seed and the time series of every other voxel in the brain. Results were expressed in terms of voxel-wise Pearson coefficients, z-Fisher transformed. Analyses were performed by concatenating the z-maps of both seeds. Statistical analyses used a small-volume correction approach, and differences were evaluated only within the DMN's region of interest (ROI): the anterior cingulate cortex (ACC), the PCC/precuneus, mPFC, left medial frontal gyrus (MFGL), bilateral medial temporal gyri (MTGR, MTGL), bilateral inferior parietal lobes (IPLR, IPLL), and bilateral hippocampal formation (hippocampus + parahippocampal gyrus) (Supplementary Figure S2).
The statistical analyses were conducted as follows. First, we investigated overall changes between patients and controls. This analysis was performed by combining the patient group (CLZ + non-CLZ) and comparing them to the controls at each time point using unpaired t-tests. Next, we used the regions that were significant in this comparison to investigate whether they differed only within the patient group, now comparing the CLZ and non-CLZ groups (between groups) at each time point using unpaired t-tests. Finally, we conducted an exploratory analysis within each patient group (within-group) separately to assess the differences between the three time points (baseline, during, and post-intervention) using paired t-tests. All findings are reported at p < 0.001 (voxel level) and p < 0.05 (cluster level). Correlation maps were normalized to z scores using Fisher transformation.
Ethics statement
This study was approved by the research ethics committee of HCFMRP-USP under registration number 14278/2011.
RESULTS
Six patients from the CLZ group, three patients from the non-CLZ group, and one healthy volunteer were excluded due to excessive head movement artifacts. Supplementary Table S1 details the mean head motion for each group and condition. We did not find any significant changes in symptoms as measured by BPRS scores.
Clinical and demographic features
Table 1 shows the clinical and demographic features of all patients (including antipsychotic medications) and healthy controls. The mean age of the non-CLZ group was significantly older than that of the control group (F2.39 = 6.46; p < 0.01), while educational attainment was significantly higher in the control group than in the patient groups (?2 = 23.38; df = 4; p<0.01).
| SZ (n=26) | |||
|---|---|---|---|
| Characteristics | non-CLZ (n=13) | CLZ (n=13) | CTL (n=14) |
| Age (years), mean (SD) | 36.0±5.8 | 32.8±6.0 | 29.1±2.3* |
| Education (years), n | |||
| < 4 | 3 | 1 | 0 |
| 4-11 | 8 | 8 | 0 |
| > 11 | 2 | 4 | 14* |
| Duration of illness (years), mean (SD) | 15.3±8.8 | 15.7±7.7 | - |
| Time from first episode to initiation of AP (months) | 4.8±9.3 | 9.9±25.0 | - |
| Duration of current AP use (months) | 61.6±55.8 | 50.0±41.8 | - |
| Time since last change in AP dose (months) | 32.3±43.2 | 18.1±13.5 | - |
| BPRS, baseline | 6.3±4.5 | 10.8±6.6* | - |
| BPRS, post-SNP | 6.5±4.2 | 10.9±6.5* | - |
AP = antipsychotic; BPRS = Brief Psychiatric Rating Scale; CLZ = clozapine; CTL = control; SNP = sodium nitroprusside.
* p < 0.01.

When comparing the two groups of patients (CLZ vs non-CLZ), there were no significant differences with respect to length of illness (t = -0.11; degrees of freedom [df] = 1; p = 0.91), time from first episode to initiation of antipsychotic therapy (t = -0.59; df = 1; p = 0.56), time on current medication (t = 0.59; df = 1; p = 0.56), or time since medication dose was last changed (t = 1.13; df = 1; p = 0.28). Significant differences were found for BPRS scores before (t = 2.04, df = 24, p = 0.05) and after SNP infusion (t = 2.04; df = 24, p = 0.05), with increased BPRS scores found in the CLZ group (in both cases). There were no significant changes within groups when comparing BPRS scores before SNP vs. after SNP (non-CLZ = t = -1.00, df = 12, p = 0.34; CLZ = t = -0.56; 9 df = 12; p = 0.58).
Functional connectivity
Between-group comparisons
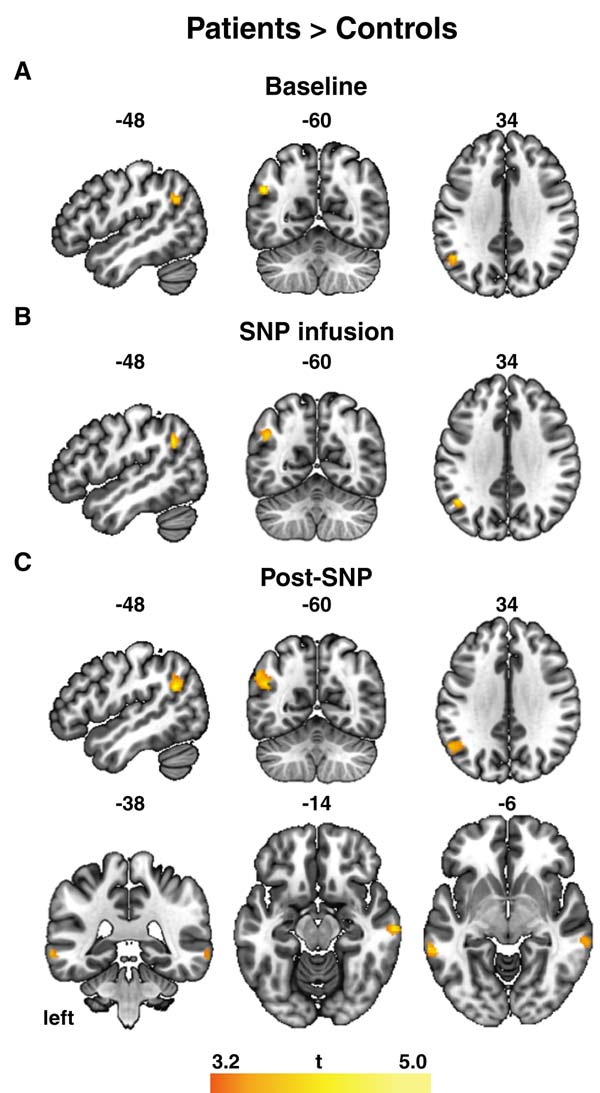
Figure 1 and Table 2 show the FC differences observed in the between-groups comparison (patients vs. controls), estimated for each condition (baseline, during SNP infusion, and post-SNP) separately. At baseline, we observed increased FC in the left supramarginal gyrus in patients compared to controls (Figure 1A). During SNP infusion, there was a significant increase in FC in the left angular gyrus (Figure 1B). After infusion, we observed increased FC in patients vs. controls in the bilateral medial temporal gyri and the left supramarginal gyrus (Figure 1C).
| Condition | Cluster size (voxels) | MNI coordinates (x, y, z) | Anatomical label |
|---|---|---|---|
| Baseline | |||
| patients > controls | 81 | -50, -60, 30 | Left supramarginal gyrus |
| During SNP infusion | |||
| patients > controls | 139 | -48, -56, 36 | Left angular gyrus |
| Post-SNP | |||
| patients > controls | 263 | -48, -58, 28 | Left supramarginal gyrus |
| 113 | 66, -20, -12 | Right medial temporal gyrus | |
| 78 | -62, -42, -6 | Left medial temporal gyrus |
FC = functional connectivity; MNI = Montreal Neurological Institute; SNP = sodium nitroprusside.

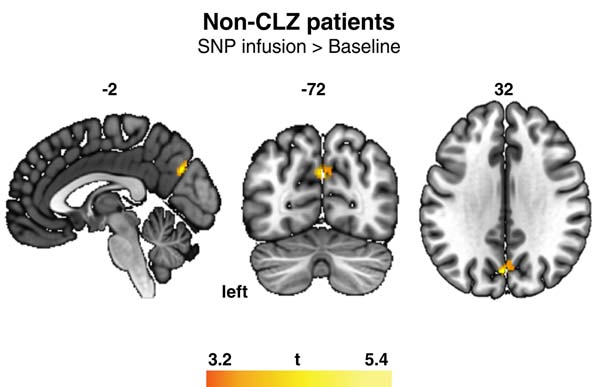
To further understand the differential effects of SNP in patients under different antipsychotic drugs, between-group comparisons were analyzed considering each group of patients separately (CLZ vs. non-CLZ) for each of the three conditions. There were no statistically significant differences between groups (CLZ vs. non-CLZ) at baseline, during, or after SNP infusion. Within-group comparisons were then analyzed in the groups of patients separately (CLZ and non-CLZ), and we observed increased FC in the precuneus of non-CLZ patients during SNP infusion compared to baseline (Figure 2).
DISCUSSION
The present study investigated the effects of SNP infusion on FC in the DMN of patients with SZ and healthy controls. When comparing patients vs. controls at baseline, we found increased FC in the left supramarginal gyrus. During SNP infusion, there was increased FC in the left angular gyrus, while after the infusion, we found increased FC in the MTGR, MTGL, and left supramarginal gyrus. Between patient groups, there were no differences at baseline, during, or after SNP infusion. Considering the effects of time, FC was higher in the precuneus during the infusion compared to baseline in the non-CLZ group. There were no significant changes in SZ symptoms as measured by the BPRS.
A previous study reported decreased symptoms in patients taking antipsychotics who underwent a single infusion of SNP (0.5 µg/kg/min) for 4 hours.22 SNP administration has also been found to improve attention and working memory for patients with SZ, as measured by the Stroop Color Word Test (SCWT) and N-Back test.23 However, more recent studies were unable to replicate these results. As an example, a multicenter, randomized, double-blind trial with similar treatment protocols did not report significant results.31 The same follows for the present study and other reports.20,24
Although the absence of an antipsychotic effect is probably attributable to the lower dose administered here (0.25 µg/kg/min for 12 minutes) in comparison with previous works (0.5 µg/kg/min for 4 hours),22,23 other methodological factors are also important when considering SNP as a treatment for SZ. For example, patients in the Hallak et al.22 study were younger than those in the more robust study.31 Also, when used for hypertension management, SNP differs in potency depending on patient age.32 Corroborating this, a study of patients with treatment-resistant SZ concluded that SNP may be more effective in the early stages of the disease.20 One possible explanation could be that adolescence and early adulthood correspond to the period when NMDA receptors are undergoing synapse stabilization and pruning, and are thus more susceptible to modulation.33 Furthermore, disease duration is a predictor of treatment prognosis for different psychopathologies.34
DMN activity has been increasingly investigated in neuropsychiatric disorders, including SZ.35 However, the exact way in which this network is changed in SZ patients is still not well known. In our sample, we observed an increase in FC in the left supramarginal gyrus of patients compared to the control group at baseline. This subregion is located in the inferior parietal lobe, one of the areas of the DMN.4 Some studies indicate hyperactivity in these regions and dysregulation in their communication in SZ.5,8 Others claim that the opposite occurs, i.e., there is hypoactivation,36,37 or even a pattern of mixed activity, with both hyperactivation and hypoactivation occurring depending on the subregion and connection pattern considered.38,39 In a study evaluating DMN activity during working memory tasks in patients with SZ and patients with depression, researchers observed that both groups showed increased activity in the right mPFC and bilateral ACC, and that the effect was stronger in the SZ group than in the depressed group.40 Another study found that the control group exhibited decreased DMN activation, specifically in the mPFC and PCC/precuneus, during working memory tasks.5 In comparison, patients and their relatives exhibited decreased activity in these areas. During rest and task moments, patients and relatives exhibited significantly greater FC in the DMN areas.4,5 These examples show there are still gaps in our knowledge regarding how exactly FC in the DMN is changed in SZ patients.
Reports show that at least part of the effects of antipsychotics are exerted through correction of DMN dysfunction. For example, in SZ patients with hyperactivated DMN regions, antipsychotic drugs reduce this activation; otherwise, they increase it.41 Here we found that patients had increased FC in the left angular gyrus during SNP infusion and more significant FC in the MTGR, MTGL, and left supramarginal gyrus after infusion. To our knowledge, this is the first time brain activity has been evaluated under SNP treatment. From a pharmacological standpoint, exactly how SNP provides these effects is unclear. Given that endogenous NO plays important roles in the central nervous system, such as facilitating synaptic functions through maintenance of long-term potentiation, protein translation at dendritic spines, and guaranteeing blood supply to neurons,42 the acute changes in FC reported herein are probably attributable to the acute normalization of NO levels provided by the administration of SNP. As previously mentioned, SNP seems to beneficially modulate the NMDA-NO-cGMP pathway by augmenting levels of NO, which would be underproduced secondary to NMDA hypofunction in SZ patients.3,22 Nevertheless, it is also important to bear in mind that this was a preliminary investigation with lower dose and shorter infusion duration compared to previous studies, so it is possible that these results could change when reproducing other trials.
The pattern of activation in certain DMN areas can predict outcomes. Doucet et al.43 found that greater functional integration in DMN subnets, particularly connectivity between medial temporal regions and the dorsal precuneus, emerged as the main positive predictor of response to antipsychotic treatment in SZ patients. Recent evidence also supports this predictive ability.44 In their review evaluating cases of first-episode psychosis, Mehta et al.44 note that most studies using fMRI as a biomarker have concluded that it is possible to predict not only treatment response but also the course of the disorder. Regarding CLZ, Ravan et al.45 used machine learning to discriminate EEG findings and concluded that the DMN regions were hyperactive and hyperconnected in SZ patients. This discrimination power decreased as patients were treated with CLZ, which is consistent with CLZ normalizing activity in those regions.45 Here, there was no difference between the CLZ and non-CLZ groups at any of the three time points of assessment. However, only the non-CLZ group showed increased FC in the precuneus during infusion compared to baseline.
Another important aspect of studying the relationship between DMN and SZ is social cognition. In their 2008 work, Schilbach et al.46 investigated the overlap of the DMN network with subregions active during social cognition tasks in healthy volunteers. Specifically, they reported greater activity in the precuneus during social interaction, in the left angular gyrus during differentiation of self, and in the ACC in action monitoring of self and others.7,46 These findings were consistent with those of other research groups.47,48 Interestingly, we found higher FC in those specific brain subareas in patients compared to healthy volunteers at all three time points of assessment. Given the roles these regions of the DMN have on monitoring of self and others, this may entail that some of the benefits of SNP infusion in SZ patients could be directly correlated with amelioration of social cognition problems, although this hypothesis went beyond the scope of this work and was not tested.
This was the first investigation to show changes in FC of the DMN of SZ patients under the influence of SNP. The small sample size, university community sample, and unique dosage compared to other clinical trials need to considered as limitations of this trial. Although previous studies show mixed findings, it is possible that SNP may help ameliorate SZ symptoms. Future studies of SNP or other NO donors in SZ should also consider relevant methodological aspects such as different doses, duration of administration, frequency of administration, patient age, and illness duration. Further investigations can also shed light on possible uses of SNP in other specific clinical populations, such as volunteers at high risk of SZ development or in prodromal phases.
SUPPLEMENTARY MATERIALS
Supplementary MaterialACKNOWLEDGEMENTS
This research was funded by Fundação de Amparo à Pesquisa do Estado de São Paulo (FAPESP), Conselho Nacional de Desenvolvimento Científico e Tecnológico (CNPq), and Instituto Nacional de Ciência e Tecnologia Translacional em Medicina (INCT-TM; 2014/50891-1).
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



