



ABSTRACT:
OBJECTIVE: To investigate the effects of the flourishing intervention (FI) vs. usual care (UC)
on craving symptoms, mental health, and quality of life among hospitalized crack/cocaine
users.
METHODS: A quasi-experimental mixed-methods study was conducted in a Brazilian psychiatric
hospital. Participants were inpatients (n=119) undergoing detoxification and met ICD-10
criteria for crack/cocaine use disorders. The FI included 12 meetings (10 group sessions)
on virtues and human values. Outcomes included crack/cocaine craving (primary), personal
flourishing, depression, anxiety, impulsivity, quality of life, readiness to change,
religiosity, and spirituality. Qualitative data were collected via semi-structured
interviews.
RESULTS: Post-treatment, the FI group (n=79) had slightly lower scores on the Cocaine Craving
Questionnaire-Brief (CCQ) measure (d = -0.21) compared to the UC group (n=40); the difference between the two groups on
a Visual Analog Scale (VAS) of crack/cocaine craving (d = -0.03) was negligible. Within-group analyses for the FI group supported post-intervention
improvements in craving (CCQ: d = -0.51; VAS: d = -0.61) and several secondary outcomes. Qualitative findings (n=30) highlighted
the value of group therapy, motivation to quit drugs and to reach personal goals,
positive emotions, and strengthening protective factors.
CONCLUSION: This study provided preliminary evidence suggesting that the FI may be beneficial
in reducing craving symptoms and promoting personal flourishing.
Keywords: Crack; cocaine; flourishing; addiction treatment; mental health; quality of life.
FIGURES
| Note: How to cite this article: Gonçalves JPB, Alvarenga WA, Cowden RG, Gorenstein C, Lucchetti G, Vallada H. Promoting holistic well-being in addiction treatment: effects of the flourishing intervention in hospitalized patients. Braz J Psychiatry. 2026;48:e20254380. Epub 2025 Oct 5. http://doi.org/10.47626/1516-4446-2025-4380 |
| Received: June 16 2025; Accepted: September 9 2025 |
INTRODUCTION
Crack/cocaine abuse remains a significant global public health issue, affecting millions.1 In 2020, 1.9 million Americans reported using crack/cocaine, burdening healthcare and social services,2 while European urban marginalized populations are experiencing an increase in crack/cocaine-related health issues.3
In developing countries like Brazil, where public health resources tend to be more limited, open drug scenes in major cities (e.g., São Paulo) have become emergent problems. Ribeiro et al.4 describe Brazil's open drug scene (cracolândias) as areas with a high prevalence of crack users and serious public health challenges, including infectious disease transmission and violence. Moreover, social stigma and marginalization of cracolândias hinder implementation of effective drug policies and interventions.5,6
Cracolândias demand comprehensive strategies to address addiction and socio-economic factors.7 Solutions to foster recovery and reintegration must bring together healthcare, social support, and law enforcement.8,9 Despite past efforts, cracolândias remain characterized by high drug use and social issues.5
Although medications are available for cocaine use disorder, none is yet approved by regulatory agencies for this purpose, leaving psychosocial interventions as the primary treatment.10 A systematic review of 64 clinical trials (n=8,241 participants) found that psychosocial interventions (e.g., cognitive-behavioral therapy, contingency management, motivational interviewing, psychodynamic therapy) reduced dropout rates and improved abstinence, but therapeutic gains were often not sustained at follow-up.11 Most of these interventions require licensed mental health professionals, which can be financially burdensome and challenging for people to access.
In recent decades, psychosocial and positive psychology interventions for substance abuse have risen in popularity, with some evidence supporting meaningful reductions in depressive and anxiety symptoms,12,13 suicide rates,14,15 and improved well-being.16,17 One randomized trial investigated a multicomponent positive psychology intervention, as compared to a waiting-list control group, and found significant reductions in tobacco, alcohol, and cannabis use over a 12-month period.18 Another trial compared two different types of positive psychology interventions (the "savoring intervention" and the "three good things intervention") against a control group.19 The study found no significant differences between the experimental conditions when comparing alcohol use, but participants in the savoring intervention experienced a reduction in alcohol-related consequences.
The concept of flourishing has gained attention for its potential to offer a holistic view of the individual that extends beyond the narrower emphasis of traditional positive psychology interventions.20 This concept, which can be traced to Aristotle, has been defined as the "relative attainment of a state in which all aspects of a person's life are good, including the contexts in which that person lives."21 This suggests considering that there are different pillars to complete well-being, which encompass physical, mental, social, and spiritual dimensions of human existence.21
Drawing on this multidimensional conception, we developed an intervention to promote individual flourishing.22 The flourishing intervention (FI) is a 12- meeting approach (10 group sessions) discussing topics such as gratitude, kindness, happiness, meaning in life, resilience, and spirituality (among others), supported by existing literature.12,18,19 Preliminary evidence suggests the FI has the potential to be an effective approach for adults with depressive symptoms.23 This holistic and multicomponent approach may also benefit substance users by focusing more on virtues and values than substance-related behaviors. To our knowledge, interventions based on this expanded model have not yet been examined among individuals who have been hospitalized for severe substance abuse. This study aims to evaluate the effects of the FI combined with usual care (UC), as compared with UC alone, on craving symptoms among patients undergoing inpatient detoxification for crack/cocaine. Secondary outcomes, such as mental health, quality of life, social support, and religiosity/spirituality, were also assessed.
METHODS
Study design
This quasi-experimental (non-randomized pre-post) study was pre-registered in the Registro Brasileiro de Ensaios Clínicos (ReBEC) with accession number U1111-1285-5624 (https://ensaiosclinicos.gov.br/rg/RBR-7437tk4).
Quantitative study
Participant eligibility
The PICO strategy, a widely adopted framework for formulating research questions,24 was used to define eligibility, inclusion, and exclusion criteria (Supplementary Box S1). Patients were eligible if they were aged 18 years or older, hospitalized for substance use recovery, diagnosed with crack/cocaine abuse disorders (ICD-10 criteria: F14 - Behavioral disorders due to use of cocaine or F19 - Behavioral disorders due to use of multiple drugs), identified crack/cocaine as their primary drug of choice on the Alcohol, Smoking and Substance Involvement Screening Test (ASSIST),25 and were clinically stable within 5 days of admission to complete the baseline interview.
Patients were excluded if they: i) were discharged before completing the baseline or the post-intervention assessment; ii) were discharged before completing at least 70% of sessions; or iii) scored below 40 on the Global Assessment of Functioning (GAF) scale, routinely conducted by hospital staff. Scores under 40 (0-100) indicate severe cognitive impairment, inability to discern reality, or an impaired capacity for self-care.26
Setting and recruitment
The study was conducted in 2023 at a psychiatric hospital specializing in addiction in São Paulo, Brazil. Data collection for the two groups occurred at separate times. During the period in which the intervention was being offered, the research team invited eligible patients to participate in the study. Patients who were clinically unstable (GAF < 40) or refused contact were reapproached daily for up to 5 days after admission, which was the cutoff point for inclusion in the study. Consenting patients completed the ASSIST scale and, if eligible, completed the baseline interview containing all instruments described below.
Research groups
- Usual care (control group). Individuals in the control group received the UC provided by the psychiatric hospital, including medical appointments, nursing support, prescribed medications, and social worker consultations. Participants could also engage in daily activities, such as physical exercise, occupational therapy, and individual or group psychotherapy. Patients could receive weekly family visits and had access to voluntary religious activities led by religious leaders. Patients were encouraged to participate in all hospital-provided activities.
- Flourishing intervention group. The intervention group received the UC described above, along with the FI at the hospital. The FI included 12 meetings: i) an initial individual session with a research team member for the baseline interview (quantitative data) and explanation of the intervention; ii) 10 group sessions with other patients and the FI healthcare provider; and iii) a final individual session for the post-intervention questionnaire (quantitative data) and intervention closure (Supplementary Box S2).
Each group session covered a different topic: i) physical and mental health, virtues, and strength of character; ii) love and gratitude; iii) acts of kindness and volunteering; iv) happiness; v) family, friends, and community; vi) compassion and forgiveness; vii) resilience; viii) spirituality and connection; ix) purpose and meaning in life; and x) flourishing. Sessions used diverse methods, including videos, reflective questions, individual writing, music, guided meditation, and discussions. More details on session development and scope are documented elsewhere.22 Groups consisted of six to 13 individuals, with each session lasting approximately 60 minutes.
The FI sessions were facilitated by healthcare professionals with experience providing mental health services, including three psychologists, two social workers, and one occupational therapist. They received 10 hours of training covering three pillars: i) the conceptual framework of flourishing and positive psychology; ii) addiction-related issues, including comorbidities and treatment; and iii) group dynamics. The research team supervised role-play FI sessions for each professional.
Procedures
Outcomes were assessed at baseline and post-intervention through individual 60-minute structured interviews conducted on-site. All items were read aloud, and responses were noted on an electronic tablet for both pre- and post-intervention interviews. Participants started FI on the same day or the day immediately following completion of the baseline interview. Given the continual admission and discharge of patients at the hospital, participants were permitted to enter the FI at varying points in sequence. For example, a patient who was admitted to the hospital after a group had completed session 3 of the FI could begin at session 4, proceed through to session 10, and then subsequently complete sessions 1 to 3 with a different group.
Seven interviewers participated in data collection: five psychologists, one social worker, one physical therapist, and one biologist. They were recruited specifically for this study and were not involved in hospital care or intervention delivery. They received 6 hours of training, which covered a theoretical section on flourishing, positive psychology, and substance use treatment followed by supervised role-play interviews.
Instruments
The variables assessed in this study are listed below. Further details about the instruments that were used are presented in Supplementary Material S1.
Primary outcome
a) The Cocaine Craving Questionnaire-Brief (CCQ) was used to measure craving; the Portuguese version has demonstrated reliability and validity in the Brazilian population.27 The CCQ contains 10 items assessing the frequency, urgency, and desire to consume crack or cocaine, each of which is rated using a 7-point response scale ranging from totally disagree (1) to totally agree (7). b) Craving was also measured with a Visual Analog Scale (VAS) item: "From 0 to 10, what is your craving for cocaine/crack at the moment?" Responses were scored on a rating scale ranging from no desire (0) to extreme desire (10).28
Secondary outcomes
The secondary outcomes evaluated were: a) personal flourishing (Secure Flourishing Index [SFI]); b) depression (Patient Health Questionnaire [PHQ-9]); c) anxiety (Generalized Anxiety Disorder [GAD-7]); d) impulsivity (Barratt Impulsiveness Scale [BIS-11]); e) quality of life (12-Item Health Survey [SF-12]); f) readiness to change (University of Rhode Island Change Assessment [URICA]); g) religiosity (Duke University Religion Index [Durel]); h) religious coping (Brief Religious and Spiritual Coping Scale [Brief RCOPE]); i) spirituality (Attitudes Related to Spirituality [ARES]); and j) social support (Multidimensional Scale of Perceived Social Support [MSPSS]).
Other variables
Severity of addiction (ASSIST) and sociodemographic characteristics (age, gender, education, religion, race, marital status, family income) were also evaluated.
Sample size
Most prior studies have evaluated pharmacological therapies vs. placebo/UC for cocaine craving, with limited evidence for non-pharmacological therapies. To calculate our sample size, we used a previous study comparing integrative meditation and UC for cocaine craving in outpatients addicted to cocaine/multiple drugs.29 According to Chen et al.,29 after 4 weeks, integrative meditation patients had a CCQ (full version) score of 18.5 (SD = 8.8) while the UC group scored 25.9 points (SD = 13.2), yielding an effect size of d = 0.65. Assuming a 1-beta of 0.90, alpha of 0.05, two-tailed test, allocation ratio of 2:1, and an effect size of d = 0.65, the minimum required sample size was 76 participants for the intervention group and 38 for the control group, totaling a minimum sample of 114 participants.
Statistical analyses
All statistical analyses were conducted using STATA 13.0. Descriptive statistics were reported as absolute numbers and percentages for categorical variables, and as means and SDs for continuous variables. Inferential analyses involved chi-square tests for categorical variables and t-tests and Pearson correlation coefficients for continuous variables.
Independent-samples t-tests were used for the between-groups analyses, and effect sizes (Cohen's d) were calculated. Assuming significant differences in the groups at baseline, linear regression models for the post-pre differences were constructed, adjusting for those variables with a p < 0.10. Within-subjects analyses (pre-to-post-intervention differences for each group) were conducted using paired samples t-tests, with corresponding effect sizes (Cohen's d) calculated. P-values < 0.05 were considered significant.
Qualitative analysis
Design
Thematic analysis was used to explore patients' experiences, including the intervention's strengths and weaknesses and the outcomes associated with the sessions. These analyses were conducted immediately after the collection of measures from the quasi-experimental study.
Participant recruitment and final sample
Purposive sampling from those in the FI condition ensured the inclusion of participants with a range of ages. Recruitment for participation in the interviews stopped once data saturation was reached, indicating a clear understanding of the phenomenon and the stability of the compiled codes.30
Data collection
After completing the post-intervention questionnaire, some inpatients were invited to participate in the qualitative study. Semi-structured individual interviews (Supplementary Box S3), lasting 20-85 minutes, were conducted in a private room in the hospital. These interviews were audio-recorded and transcribed verbatim. The trained interviewer members of the research team, who were not part of the hospital staff and who did not deliver the intervention during the study, conducted the interviews.
Data analyses
Qualitative interview data were analyzed using inductive thematic analysis to identify and report patterns.31 Three researchers thoroughly reviewed transcripts to determine key emerging concepts. They collaboratively developed a codebook and grouped similar codes into themes. This continued until no new themes emerged. Themes were assessed for coherence to illustrate the impact of the FI and refine the intervention for broader future study, with exemplary quotations presented for each theme.
Trustworthiness and credibility were ensured through independent and team analysis, systematic research documentation using field notes, and a comprehensive presentation of participants' diverse perspectives. A commitment to reflectivity addressed how the researchers' professional backgrounds (psychologist, physiotherapist, and nurse) could influence findings, particularly during coding and data interpretation.32
The Standards for Reporting Qualitative Research (SRQR) guided this qualitative research report.33
Ethics statement
The protocol received approval from the Research Ethics Committee of the Faculdade de Medicina, Universidade de São Paulo, Brazil (Certificate of Submission for Ethical Approval [CAAE]: 59928422.1.0000.0068/CAPPesq). All participants provided written informed consent.
RESULTS
Quantitative analysis
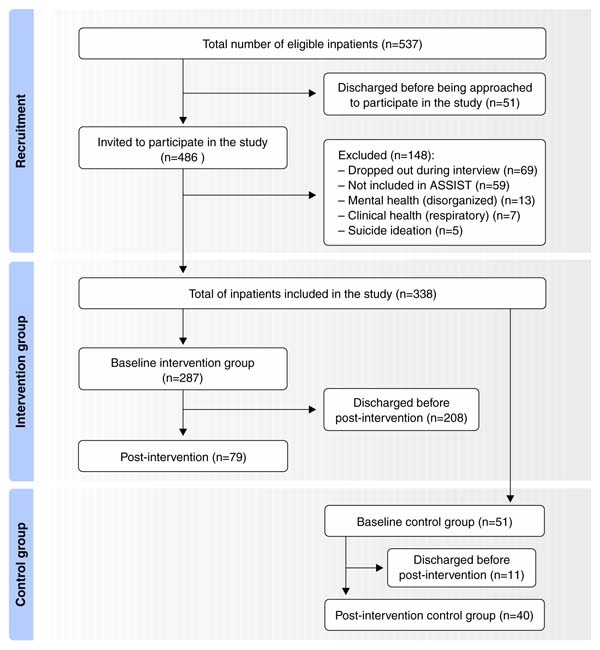
Figure 1 presents a flowchart of participation in the study and reasons for exclusion. The total number of patients hospitalized for crack/cocaine detoxification during the study period was 537. The final sample comprised 79 participants in the intervention group and 40 in the control group.

Most participants were males (91.6%), single or separated (89.9%), non-White (73.1%), had low income (72.3%), and were middle-aged (mean = 39.7 years, SD = 9.2). No significant sociodemographic differences were noted, except for a higher proportion of White individuals (p = 0.037) and more highly educated individuals (p = 0.017) in the intervention group (Supplementary Table S1). No significant between-group differences were found regarding the primary and secondary outcomes (Supplementary Table S2).
Table 1 compares the primary and secondary outcomes between the groups at post-intervention. There were no significant differences for the primary outcome of craving assessed using the VAS (d = -0.03) and CCQ (d = -0.21). Although secondary outcomes were also nonsignificant (d = -0.01 to d = 0.33), moderate effect sizes favoring the FI group appeared for family social support (d = 0.30), personal flourishing (d = 0.28), and mental quality of life (d = 0.33). Results were similar after adjusting for relevant covariates (Table 2).
| FI group (n=79) | UC group (n=40) | |||||
|---|---|---|---|---|---|---|
| Variable | Mean | SD | Mean | SD | p-value | Cohen's d |
| Craving (VAS) | 1.82 | 3.0 | 1.92 | 3.1 | 0.864 | -0.03 |
| Craving (CCQ) | 23.56 | 7.9 | 25.25 | 8.4 | 0.285 | -0.21 |
| Depression | 8.60 | 5.3 | 9.82 | 6.1 | 0.268 | -0.21 |
| Anxiety | 6.81 | 5.1 | 7.77 | 5.2 | 0.338 | -0.19 |
| Impulsivity (total) | 70.07 | 13.5 | 69.37 | 15.3 | 0.798 | -0.05 |
| Impulsivity (motor) | 25.67 | 5.9 | 24.57 | 7.2 | 0.380 | -0.17 |
| Impulsivity (attentional) | 18.01 | 4.8 | 17.47 | 4.3 | 0.555 | -0.11 |
| Impulsivity (non-planning) | 26.15 | 4.6 | 26.67 | 5.11 | 0.574 | -0.11 |
| Quality of life (physical) | 77.86 | 22.7 | 74.24 | 21.2 | 0.401 | 0.16 |
| Quality of life (mental) | 63.89 | 25.9 | 55.31 | 26.0 | 0.090 | 0.33 |
| Changes in drug use behavior | 35.87 | 4.5 | 36.52 | 4.8 | 0.464 | -0.14 |
| Personal flourishing | 80.12 | 16.0 | 75.75 | 15.2 | 0.155 | 0.28 |
| Spirituality | 50.78 | 6.4 | 49.6 | 8.2 | 0.389 | 0.17 |
| Organizational religiosity | 3.72 | 1.8 | 3.95 | 1.9 | 0.524 | -0.12 |
| Non-organizational religiosity | 5.47 | 1.3 | 5.37 | 1.5 | 0.723 | 0.07 |
| Intrinsic religiosity | 12.87 | 2.9 | 12.87 | 2.7 | 0.997 | -0.01 |
| Positive religious coping | 29.37 | 6.4 | 28.02 | 6.3 | 0.274 | 0.21 |
| Negative religious coping | 24.69 | 6.9 | 25.85 | 6.3 | 0.377 | -0.17 |
| Social support (family) | 16.96 | 7.9 | 14.65 | 6.7 | 0.120 | 0.30 |
| Social support (friends) | 17.96 | 8.7 | 17.40 | 7.9 | 0.732 | 0.07 |
| Social support (others) | 21.90 | 5.6 | 20.67 | 5.3 | 0.254 | 0.22 |
CCQ = Cocaine Craving Questionnaire; FI = flourishing intervention; UC = usual care; VAS = Visual Analog Scale.

| FI group (n=79) | UC group (n=40) | |||||||
|---|---|---|---|---|---|---|---|---|
| Variable | Mean┼ | SD | Mean | SD | Unadjusted estimate | p-value | Adjusted estimate╬ | p-value |
| Craving (VAS) | -2.16 | 4.10 | -2.27 | 3.41 | 0.013 | 0.884 | 0.068 | 0.479 |
| Craving (CCQ) | -5.30 | 12.80 | -3.82 | 11.20 | -0.057 | 0.537 | -0.043 | 0.642 |
| Depression | -9.28 | 6.39 | -8.17 | 7.53 | -0.077 | 0.404 | -0.030 | 0.756 |
| Anxiety | -6.75 | 6.74 | -5.72 | 7.60 | -0.069 | 0.456 | -0.047 | 0.633 |
| Impulsivity (total) | -6.34 | 11.60 | -5.3 | 12.80 | -0.042 | 0.657 | -0.012 | 0.899 |
| Impulsivity (motor) | -2.57 | 5.69 | -1.87 | 5.72 | -0.058 | 0.531 | -0.068 | 0.490 |
| Impulsivity (attentional) | -1.24 | 4.60 | -1.17 | 4.40 | -0.007 | 0.941 | 0.041 | 0.678 |
| Impulsivity (non-planning) | -2.13 | 4.60 | -2.10 | 4.28 | -0.003 | 0.976 | 0.013 | 0.893 |
| Quality of life (physical) | 8.70 | 23.00 | 7.81 | 16.50 | 0.020 | 0.829 | 0.009 | 0.140 |
| Quality of life (mental) | 27.43 | 29.50 | 17.10 | 31.80 | 0.161 | 0.080 | 0.091 | 0.344 |
| Drugs change behavior | 1.26 | 5.00 | 1.95 | 6.00 | -0.060 | 0.514 | -0.049 | 0.625 |
| Personal flourishing | 19.88 | 21.40 | 16.27 | 20.60 | 0.081 | 0.381 | 0.028 | 0.770 |
| Spirituality | 2.53 | 7.40 | 0.65 | 7.40 | 0.120 | 0.194 | 0.098 | 0.327 |
| Organizational religiosity | 0.88 | 1.90 | 0.92 | 1.80 | -0.010 | 0.916 | 0.029 | 0.771 |
| Non-organizational religiosity | 0.76 | 1.80 | 0.70 | 2.10 | 0.015 | 0.973 | 0.049 | 0.620 |
| Intrinsic religiosity | 1.40 | 3.40 | 0.32 | 2.50 | 0.160 | 0.082 | 0.157 | 0.111 |
| Positive religious coping | 2.47 | 6.20 | 1.27 | 7.90 | 0.083 | 0.369 | 0.108 | 0.281 |
| Negative religious coping§ | 2.25 | 7.40 | 0.92 | 7.40 | 0.085 | 0.358 | 0.017 | 0.589 |
| Social support (family) | 3.37 | 8.00 | 1.90 | 6.20 | -0.094 | 0.305 | -0.069 | 0.491 |
| Social support (friends) | 0.56 | 6.80 | 2.02 | 8.20 | 0.093 | 0.312 | 0.111 | 0.268 |
| Social support (others) | 1.50 | 6.20 | 1.97 | 7.10 | -0.034 | 0.713 | -0.029 | 0.775 |

The within-subjects post-pre comparisons for each group are presented in Table 3. In the FI group, craving scores on the VAS (p < 0.001, d = -0.61) and CCQ (p < 0.001, d = -0.51) were significantly lower after the intervention. Secondary outcomes also improved, except for social support from friends, which showed a negligible difference. The most improved secondary outcomes in the intervention group were depression (d = -1.66) and anxiety (d = -1.22). Post-intervention changes in primary outcomes in the control group (craving VAS: p < 0.001, d = -0.64; CCQ: p = 0.030, d = -0.35) were similar to those seen in the FI group. Compared to the intervention group, the control group showed fewer improvements in secondary outcomes, with no evidence of pre-post differences in spirituality, intrinsic religiosity, religious coping, or social support variables. The most improved secondary outcomes in the control group were depression (d = -1.31) and anxiety (d = -1.01).
| Pre (FI group) (n=79) | Post (FI group) (n=79) | |||||
|---|---|---|---|---|---|---|
| Variable | Mean | SD | Mean | SD | p-value | Cohen's d |
| Craving (VAS) | 3.99 | 3.90 | 1.82 | 3.00 | < 0.001 | -0.61 |
| Craving (CCQ) | 28.86 | 12.20 | 23.56 | 7.90 | < 0.001 | -0.51 |
| Depression | 17.90 | 5.90 | 8.62 | 5.30 | < 0.001 | -1.66 |
| Anxiety | 13.56 | 5.90 | 6.81 | 5.10 | < 0.001 | -1.22 |
| Impulsivity (total) | 76.41 | 13.60 | 70.07 | 13.50 | < 0.001 | -0.47 |
| Impulsivity (motor) | 28.24 | 5.80 | 25.67 | 5.90 | < 0.001 | -0.43 |
| Impulsivity (attentional) | 19.25 | 4.30 | 18.01 | 4.80 | 0.019 | -0.27 |
| Impulsivity (non-planning) | 28.28 | 5.10 | 26.15 | 4.60 | < 0.001 | -0.43 |
| Quality of life (physical) | 69.10 | 23.60 | 77.86 | 22.70 | 0.001 | 0.37 |
| Quality of life (mental) | 36.45 | 23.50 | 63.89 | 25.80 | < 0.001 | 1.11 |
| Drugs change behavior | 34.61 | 3.20 | 35.87 | 4.50 | 0.027 | 0.33 |
| Personal flourishing | 60.24 | 23.9 | 80.12 | 16.00 | < 0.001 | 0.97 |
| Spirituality | 48.25 | 9.30 | 50.78 | 6.40 | 0.003 | 0.32 |
| Organizational religiosity | 2.83 | 1.80 | 3.72 | 1.80 | < 0.001 | 0.49 |
| Non-organizational religiosity | 4.71 | 1.80 | 5.47 | 1.30 | < 0.001 | 0.49 |
| Intrinsic religiosity | 11.47 | 3.70 | 12.87 | 2.90 | < 0.001 | -0.42 |
| Positive religious coping | 26.91 | 7.50 | 29.38 | 6.40 | < 0.001 | 0.35 |
| Negative religious coping | 22.44 | 7.90 | 24.70 | 6.90 | 0.008 | 0.30 |
| Social support (family) | 13.57 | 8.00 | 16.93 | 7.90 | < 0.001 | 0.42 |
| Social support (friends) | 17.40 | 7.90 | 17.96 | 8.70 | 0.472 | 0.07 |
| Social support (others) | 20.39 | 6.80 | 21.90 | 5.60 | 0.035 | 0.24 |
| Pre (UC group) (n=40) | Post (UC group) (n=40) | |||||
| Mean┼ | SD | Mean┼ | SD | |||
| Craving (VAS) | 4.20 | 3.90 | 1.92 | 3.10 | < 0.001 | -0.64 |
| Craving (CCQ) | 29.07 | 12.70 | 25.25 | 8.40 | 0.030 | -0.35 |
| Depression | 18.00 | 6.20 | 9.82 | 6.10 | < 0.001 | -1.31 |
| Anxiety | 13.50 | 6.00 | 7.80 | 5.20 | < 0.001 | -1.01 |
| Impulsivity (total) | 74.67 | 14.70 | 69.37 | 15.30 | 0.012 | -0.35 |
| Impulsivity (motor) | 26.40 | 6.60 | 24.50 | 7.20 | 0.045 | -0.27 |
| Impulsivity (attentional) | 18.65 | 4.60 | 17.47 | 4.30 | 0.096 | -0.26 |
| Impulsivity (non-planning) | 28.77 | 4.80 | 26.67 | 5.10 | 0.003 | -0.42 |
| Quality of life (physical) | 66.42 | 23.80 | 74.24 | 21.20 | 0.004 | 0.35 |
| Quality of life (mental) | 38.25 | 27.50 | 55.31 | 26.00 | 0.001 | 0.64 |
| Drugs change behavior | 34.57 | 4.30 | 36.52 | 4.80 | 0.048 | 0.43 |
| Flourishing | 59.47 | 21.00 | 75.75 | 15.20 | < 0.001 | 0.89 |
| Spirituality | 48.95 | 9.40 | 49.60 | 8.10 | 0.579 | 0.07 |
| Organizational religiosity | 3.02 | 4.00 | 3.95 | 1.90 | 0.002 | 0.47 |
| Non-organizational religiosity | 4.67 | 2.10 | 5.37 | 1.50 | 0.040 | 0.38 |
| Intrinsic religiosity | 12.55 | 3.00 | 12.87 | 2.70 | 0.415 | 0.11 |
| Positive religious coping | 26.75 | 7.00 | 28.02 | 6.30 | 0.313 | 0.19 |
| Negative religious coping | 24.92 | 5.70 | 25.85 | 6.30 | 0.433 | 0.15 |
| Social support (family) | 12.75 | 7.60 | 14.65 | 6.70 | 0.060 | 0.26 |
| Social support (friends) | 15.37 | 7.80 | 17.40 | 7.90 | 0.128 | 0.26 |
| Social support (others) | 18.70 | 6.80 | 20.67 | 5.30 | 0.088 | 0.32 |
Bold type denotes statistically significant difference.
CCQ = Cocaine Craving Questionnaire; FI = flourishing intervention; UC = usual care; VAS = Visual Analog Scale.
┼ Post-pre values for each group.

Qualitative analysis
A total of 30 participants (29 men, 1 other), with a mean age of 39.4 (SD = 8.6) years, participated in post-intervention semi-structured interviews. Five themes were identified as reflecting their experience of the FI: valuing group therapy, feeling motivated to quit drugs, feeling supported in meeting their goals, experiencing positive emotions, and enhancing protective factors. Sample quotes appear in Table 4.
| Valuing group therapy | "I stayed in the Flourishing program because the debates got interesting, sharing feelings, hearing everyone's stories. (...) I got more into it, not just because of what the professionals were teaching, but because of the stories from each person." (P25)"It met my expectations. The meetings are kind of like Narcotics Anonymous, where you get to speak, share both the bad and good experiences, and that helps set an example for others." (P13)"The family topic helped me a lot - forgiveness, resilience, and other topics that are all delicate for me. Also, topics about the past, future, and present, which are still tough for me, but I'm trying to understand them better." (P24) |
| Feeling motivated to quit drugs | "I have cravings almost every day, but they've gone down a lot. In the group, you see it's not just me with this craving. Everyone still has them, but it's lighter now, not that intense urge anymore." (P10)"Here, you're offering me support, helping me to work on patience and impulse control. You're motivating me to think about good things." (P4) |
| Feeling supported in meeting their goals | "I'm more patient now and have more hope. I believe I can make it. I'll get out, get my ID, sign up for Bolsa Família. I used to doubt it, but now I believe I'll make it." (P17)"The way we see life totally affects our treatment. What changes is how you look at life and handle situations. We learn to deal with things better, and that's something we reflect on in the group. I've come out stronger, learning to handle each situation, and I've learned that from the group." (P3)"It's been helping me a lot, really a lot. I want to get out of here a new man, with a clean, pure heart like I used to have, full of love, not just for my wife and daughter but for others too. The group here is helping me a lot with that - to become a new man and go back to being a family again. (...) It's giving me the strength to go look for the CAPS [Psychosocial Care Center]." (P8) |
| Experiencing positive emotions | "I've already made plans here, and my anxiety has gone down a lot. Before, I didn't have plans, I had nothing, so my anxiety just kept growing. I used to think, 'Why should I do this treatment if I'll just leave and use again?' Now, I know I won't use again, and my anxiety has changed a lot." (P9)"Every time I came to the group, sometimes I'd come feeling heavy, not even wanting to be here, and I'd leave feeling relieved, lighter, like I was walking on clouds. The group helped me a lot, it really opened my mind, not just about my problem with alcohol and drugs, but about my life outside too." (P19)"It's the little things, small gestures that we stop doing on the streets that we were reminded of here. It felt great to be part of Flourishing. Resilience, love, compassion, forgiveness... There were lots of good things that we had stopped practicing in everyday life, but here, we got back in touch with them, and it added a lot to our lives. It felt good, and I felt great." (P6) |
| Enhancing protective factors | "It strengthened my spirituality a lot. I realized that God wanted just one thing from me - to quit crack first. It wouldn't make sense to know Him and still use crack. So, I think it really boosted my spirituality." (P9)"I was just feeling angry, depressed, hurt. I hurt my family a lot. I took my sister's phone and I'm going to ask her for forgiveness. Let her know I'm okay, that I'm in treatment. Flourishing helped me ask for forgiveness from my family." (P29)"You can't do anything alone. People say, 'I don't need anyone, and when I want to quit, I will.' It's a lie! You won't quit on your own, so you need help. The ninth session of Flourishing really got me thinking (...). I related a lot to it. I had no life, but now I'm thinking of moving, starting a better life somewhere else. That's what I want, and session nine inspired me." (P1)"Recovery is painful. If I really want to stay clean, find sobriety, get back into the workforce, reach a point where I'm a normal citizen, pay my bills, have a roof over my head... I'll have to go through treatment. It's going to be painful, and sometimes it'll take longer than I expected." (P24) |

Valuing group therapy
The primary reason participants gave for joining the FI was seeking additional support to manage cravings (n=18). The opportunity to share experiences and feelings among peers in a healthcare-led group motivated their participation and engagement. Using idle time during hospitalization to distract from cravings and deriving satisfaction from peer interactions were additional factors influencing their decision to remain in the FI.
Most participants (n=19) had their expectations met or exceeded. They found the FI format distinctive, noting similarities to Alcoholics Anonymous (AA) and Narcotics Anonymous (NA) groups. Participants highlighted empathy, respect, freedom, equality, privacy, and clear communication as significant characteristics within the group and among the healthcare providers.
Participants expressed satisfaction with session duration, dynamism, and audiovisual resources, with particular interest in Family, Friends, and Community (n=6); Spirituality (n=5); Physical and Mental Health, Character Strengths, and Virtues (n=4); Flourishing (n=4); Acts of Kindness and Volunteering (n=3); Meaning and Purpose in Life (n=3); Forgiveness (n=3); Happiness (n=2); Resilience (n=2); and Love and Compassion (n=1) sessions. They felt connected to the group and comfortable from the start. However, four participants felt the continuous influx of new participants hindered connection.
Feeling motivated to quit drugs
Participants reported strengthened motivation to cease drug use through group participation. The FI was perceived as a supportive element in their treatment. Fifteen participants noted alleviated cravings despite experiencing withdrawal symptoms. The FI facilitated the adoption of alternative behaviors to counter addiction and mitigate cravings, including changing environments, building new social networks, adopting healthy habits, and engaging in distracting activities.
Feeling supported in meeting their goals
Participants observed changes in their outlook on life and coping mechanisms. Sixteen reported improved thought patterns, increased self-esteem, and a greater willingness to engage in future projects. They also indicated becoming more patient, supportive, and compassionate. The FI motivated them to contemplate the future and plan pathways to achieve their goals. New personal goals to maintain abstinence included reconciling with family, reintegrating into society, securing housing, obtaining employment, resuming studies, and continuing health treatment post-discharge. They felt more hopeful about achieving life goals, as the FI "taught that life without drugs is possible" (P25).
Experiencing positive emotions
Participants (n=17) reported that sessions helped them express and manage their feelings. Outcomes of the FI included forgiving oneself, resilience, patience, perseverance, and feelings of peace, joy, and happiness. Participants also mentioned reduced impulsivity and anxiety, as well as an increased sense of well-being and satisfaction after the FI.
Enhancing protective factors
Many participants acknowledged difficulties in coping with life's realities before the FI, often using drugs as an escape. Post-intervention, participants reported strengthened protective factors against drug use. Emphasis on religious/spiritual factors (n=13) and encouragement of religious practices (n=7) were highlighted as emotional supports to prevent relapse. Participants became more aware of how they relate to themselves, including self-care and self-compassion (n=10), relationships with others (n=15), and family (n=15).
The FI facilitated improved communication and development of social skills (n=17), such as dialogue, listening, emotional self-control, and forgiveness. Participants also reported taking responsibility for their recovery (n=10). Reflections prompted by the FI included distancing from former social circles, adhering to medication and therapies, focusing on new life projects, and avoiding drugs when facing challenges.
DISCUSSION
This study furthers our understanding of the potential role that a holistic well-being intervention can play in inpatient detoxification treatment. Although previous literature showed that interventions such as cognitive-behavioral therapy,34 motivational interviewing,35 and the 12-step AA or NA36 could effectively treat substance users, most studies focused on outpatients with milder conditions and symptoms.35,37 Our study advances research by proposing an FI that stimulates an individual's virtues and values during acute detoxification stages. In addition, unlike psychosocial interventions that focus more directly on substance use, the FI emphasizes self-awareness, health promotion, and reinforcement of protective factors.
The positive mental health outcomes observed in an earlier mixed-methods quasi-experimental investigation of the FI among individuals with moderate to moderately severe depressive symptoms are comparable to those observed here.23 Braghetta et al.23 reported pre-post intervention improvements in depressive and anxiety symptoms, with effect sizes of d = -1.14 and d = -1.22; in the present study, the corresponding effect sizes were d = -1.66 and d = -0.60. Although there were some differences between the two sets of findings, evidence of similar improvements in personal flourishing across both studies points to the potential value of enhancing a global multidimensional outcome to impact different areas of a person's life. These parallel findings suggest that the FI may offer a transdiagnostic benefit by promoting well-being across distinct clinical populations, including those with complex psychiatric and psychosocial needs.
Likewise, although other positive psychology interventions for substance abusers exist,38-40 none - to our knowledge - have explicitly included religious/spiritual components. There is growing evidence supporting religious/spiritual aspects in substance use treatment, including the well-known AA model that fosters a sense of community through group meetings, spiritual principles, and shared experiences.41 One of the key elements of the 12-step AA program is spirituality, a significant dimension of human life42 that is often considered an essential ingredient in the process of recovering from addiction.37 Frequent attendance at meetings can enhance long-term abstinence,43 reduce symptom severity, and improve quality of life.44 The FI draws on the values and virtues addressed in positive psychology interventions but also includes existential and spiritual aspects to promote health and well-being.
Although we did not observe significant differences between the two groups at post-treatment, there were moderate effect sizes favoring the FI group for social support, personal flourishing, and mental quality of life. When comparing pre- to post-intervention changes in each group, changes were somewhat larger for the FI group on the mental quality of life, spirituality, intrinsic religiosity, and social support outcomes, a pattern that was supported by the qualitative findings. One possible explanation for the aforementioned improvements in outcomes in the FI group is the multifaceted benefit illustrated in the qualitative data. For instance, "feeling motivated to quit drugs" has been identified as a mediating pathway between post-discharge efficacy and abstinence, in which its role can overcome reports of low confidence.45 "Feeling supported" from healthcare professionals has been associated with boosting self-esteem,46 and "feeling supported" by relatives has also been described as a crucial catalyst for maintaining participation in treatment.47 Higher levels of well-being and "experiencing positive emotions" have been shown to be associated with better mental health outcomes,48,49 greater engagement in community activities, and stronger social networks.50 Finally, "enhancing protective factors," such as spirituality,43 resilience,51 forgiveness,52 and character strengths,53,54 are linked to better emotional regulation and personal growth among substance abusers. The combination of benefits to which the qualitative data alludes may reflect overlapping and reinforcing mechanisms supporting positive changes.
There may be several potential reasons for the nonsignificant between-group differences in the primary outcome variables. First, cracolândias are characterized by a unique scenario involving marginalized individuals who live in an area usually controlled by drug dealers, and where illegal drug trade and prostitution are common.4 Individuals who live there are typically unemployed and struggle with their basic needs. Maslow's theory outlines human motivation in a hierarchy of five levels of needs, with physiological and safety needs considered foundational.55 Substance-dependent individuals often worry about achieving basic needs such as food, safety, and avoiding harm. Thus, interventions with a more ambitious target of flourishing may seem less relevant to those struggling with substance dependence around the time they are hospitalized.
Second, usual treatment, particularly for acute detoxification, involves quality care that focuses on alleviating cravings, improving mental health outcomes, and can enhance well-being, which also corroborates the clinical improvements experienced by both groups in our study. Substance abusers usually lack addiction education and self-awareness about the consequences of their condition.56 In this vulnerable population, addressing these areas can be especially beneficial, even without delving into the deeper topics represented in the FI. Within this hospital treatment setting, the benefits of the FI may not produce changes beyond those ordinarily achieved through UC. However, it is worth noting that the FI group showed evidence of improvements in a number of outcomes not observed in the control group (e.g., impulsivity, spirituality, intrinsic religiosity, and social support), and the impact of certain aspects of the FI on certain outcomes (e.g., religion/spirituality, social connectedness) might develop over time after discharge.
Third, our instruments and scales may not have captured the nuanced experiences of participants.57 For example, Tiffany & Wray57 argued that craving is a subjective experience and complex to measure. Our findings seem to support this, as notable differences between craving assessments emerged, with a negligible between-group difference found using the VAS and a medium-sized between-group difference observed using the CCQ scale. Self-report instruments rely on individuals' introspective abilities, which can be influenced by cognitive and emotional factors. Future studies could combine objective professional assessments with subjective self-reports for more comprehensive evaluation.
Although these caveats are important to consider, the effect sizes observed in this study suggest that using a holistic approach such as the FI may be promising for treating individuals with substance use disorders. A key advantage is that the intervention can be delivered by different healthcare professionals, including doctors, nurses, physical educators, and occupational therapists. Particularly for hospitals specializing in substance abuse and mental disorders, which are usually fewer in number compared to general clinical hospitals and often have higher per-patient treatment costs, interventions that can be implemented by a range of providers following low-cost training represent a feasible clinical option.58,59
This study has limitations. The use of a non-randomized design limits the ability to draw causal conclusions and increases the risk of selection bias. Although we attempted to minimize these potential drawbacks by adjusting for sociodemographic variables in some of our main analyses and incorporating qualitative data to provide an in-depth perspective on experiences of participants with the FI intervention,60 future studies might improve the evidence on the effectiveness of the FI in substance-abusing populations by adopting randomized designs. The sample included in the present study was overwhelmingly male. While this may limit the generalizability of the findings, the gender composition of our sample aligns with prior research suggesting that severe substance abuse tends to be more prevalent in males.61 The severity of crack/cocaine use and the specific sociodemographic profile of our sample may not be representative of other substance-abusing populations, warranting caution in transposing these findings to such populations. We sought to standardize the delivery of the intervention by providing healthcare professionals who facilitated the FI with a 10-hour training that combined theoretical instruction with role-play exercises. However, we did not formally assess facilitator competencies or account for the potential effect of variation in facilitators on the outcomes. Finally, post-intervention assessments were conducted immediately after the FI session had concluded, limiting insights into the long-term effects on outcomes. Notably, the unique characteristics of individuals who have ties to cracolândias (e.g., difficulties recontacting them if they return to those locations after discharge) pose a key challenge for conducting follow-ups.4
This study provided preliminary evidence on the effects of the FI combined with UC on individuals with crack/cocaine abuse disorders during detoxification. Although both the FI and UC groups showed improvements in cravings, mental health symptoms, and quality of life, post-treatment differences generally favored the FI group. Several outcomes that improved in the FI group showed little evidence of improvement in the control group (e.g., spirituality, religious coping, and social support). Although rigorous follow-up studies are needed to replicate and build on this study's findings, the holistic framework of the FI may support long-term recovery among substance-abusing populations.
ACKNOWLEDGEMENTS
This work was sponsored by Instituto Homero Pinto Vallada. JPBG has received a scholarship from Fundação de Amparo à Pesquisa do Estado de São Paulo (FAPESP) (2023/11234-4). GL and HV are research productivity grantees of the Conselho Nacional de Desenvolvimento Científico e Tecnológico (CNPq).
We are grateful to Gustavo Machado Barros for his insightful contributions to the methodological framework of this study. We are also grateful to all the hospital staff for their assistance during the intervention period.
DISCLOSURE
The authors report no conflict of interest.
DATA AVAILABILITY STATEMENT
The data that support this study are available from the authors upon request.
AUTHOR CONTRIBUTIONS
JPBG: Writing - original draft, Methodology, Investigation, Formal analysis, Data curation, Conceptualization.
WAA: Writing - review & editing, Methodology, Investigation, Formal analysis.
RGC: Writing - review & editing, Supervision, Methodology.
CG: Writing - review & editing, Supervision, Methodology.
GL: Writing - review & editing, Supervision, Methodology, Investigation, Conceptualization.
HV: Writing - review & editing, Supervision, Project administration, Methodology, Funding acquisition, Data curation, Conceptualization.
All authors have read and approved of the final version to be published.
Handling Editor: João Castaldelli-Maia
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



