



ABSTRACT:
OBJECTIVE: This study aimed to determine the temperament and personality profile of children
and adolescents with attention-deficit/hyperactivity disorder (ADHD) through a systematic
review and meta-analyses of published data.
METHODS: We searched PubMed, PsycINFO, and Web of Science in October 2021 (the PubMed search
was updated in September 2024) to identify case-control studies of children and adolescents
(= 18 years of age) with and without ADHD that reported on temperament or personality.
The association between temperament or personality domains and ADHD status was measured
with standardized mean differences (SMD). Data across studies were pooled with inverse
variance random-effects meta-analyses. Risk of bias was assessed with the Newcastle-Ottawa
Scale.
RESULTS: A total of 31 studies including 2,525 children and adolescents with ADHD and 3,039
controls were included. The meta-analyses demonstrated that children and adolescents
with ADHD had higher negative affectivity (SMD = 0.79, 95%CI 0.56 to 1.03) and lower
effortful control (Rothbart's construct) (SMD = -1.43, 95%CI -2.14 to -0.72), higher
emotionality (SMD = 1.01, 95%CI 0.64 to 1.38) and higher activity (Buss & Plomin's
construct)(SMD = 0.96, 95%CI 0.74 to 1.17), lower distractibility (SMD = -0.74, 95%CI
-1.22 to -0.26) and lower adaptability (Thomas & Chess's construct)(SMD = -1.01, 95%CI
-1.93 to -0.10), higher novelty seeking (SMD = 1.19, 95%CI 0.87 to 1.51) and lower
persistence (Cloninger's construct)(SMD = -1.07, 95%CI -1.33 to -0.81), and higher
neuroticism (SMD = 0.92, 95%CI 0.37 to 1.48), higher extraversion (SMD = 0.27, 95%CI
-0.13 to 0.67), and lower conscientiousness (five-factor model)(SMD = -0.95, 95%CI
-1.85 to -0.04). As limitations, few studies reported all temperament or personality
subscales, raising concerns about selective reporting and bias, while the heterogeneity
of instruments and case/control definitions further challenged data pooling and interpretation.
Consequently, the meta-analyses yielded limited evidence.
CONCLUSION: Children and adolescents with ADHD have greater negative affectivity/emotionality
and lower effortful control/persistence/conscientiousness. However, these findings
were based on relatively few studies, and there was considerable between-study variability.
Future research should investigate whether temperament or personality have clinical
implications for those with ADHD.
Keywords: Attention deficit hyperactivity disorder; child; temperament; personality; case-control.
FIGURES
| Note: How to cite this article: de Medeiros Filho MV, Blumrich L, Farhat LC, Polanczyk GV. Temperament and personality profile of children and adolescents with attention-deficit/hyperactivity disorder: a meta-analysis. Braz J Psychiatry. 2026;48:e20254330. Epub 2025 Oct 12. http://doi.org/10.47626/1516-4446-2025-4330 |
| Received: May 14 2025; Accepted: September 29 2025 |
INTRODUCTION
Attention-deficit/hyperactivity disorder (ADHD) is a neurodevelopmental disorder characterized by inattention and/or hyperactivity/impulsivity.1 Its prevalence is estimated at approximately five percent in childhood and adolescence.2 ADHD-related burden is distributed across individuals who live with this condition and their families, as well as their communities.3 For instance, epidemiological studies have demonstrated that individuals with ADHD are at increased risk of lower educational achievement, interpersonal conflicts, occupational obstacles, traffic accidents, and suicide attempts.4 Although several pharmacological and non-pharmacological interventions have been demonstrated efficacious for ADHD, a deeper understanding is needed of the etiological factors driving ADHD, since knowledge about its underlying mechanisms could lead to improved treatment.5
Temperament describes individual differences in reactivity and self-regulation that are determined by genetic factors and social experience6 Personality traits are viewed as an extension of temperament, which includes values, concept of self, and long-term motivations.7 There is no consensus on whether human behavior patterns are best described as temperament or personality traits, especially because temperament and personality are related, although not identical.8 Because there are multiple temperament and personality conceptualizations with many described constructs, researchers have proposed that at least three major dimensions (negative affectivity/emotionality/neuroticism, surgency/extraversion, and effortful control/persistence/conscientiousness) would capture the content of the most prominent models used in scientific investigations.6
These three main dimensions combine temperament and personality-related constructs. First, while the theoretical background can differ, negative affectivity and neuroticism both describe a tendency toward negative emotional experience. Negative affectivity is typically seen as the early-emerging, biologically-based precursor to neuroticism.6 Second, surgency and extraversion describe levels of activity, sociability, positive emotions, and reward sensitivity.6 Third, effortful control and conscientiousness are closely linked constructs with a shared foundation in self-regulation, goal-directed behavior, and executive function.6 Importantly, temperament and personality traits may help characterize (and partially explain) the heterogeneity of different psychiatric disorders,9 including ADHD.10 For example, increased negative affectivity/emotionality has been linked to emotional dysregulation (i.e., the inability to control negative emotions associated with impulsive reactions) and disruptive symptoms.11 In children with ADHD, high surgency/extraversion has also been associated with hyperactivity-impulsivity symptoms, as well as disruptive symptoms, such as oppositional aggressive and antisocial behavior.12 Furthermore, effortful control/self-regulation has been directly associated with executive function and inversely associated with inattention and impairment in organization or planning.13
However, few systematic reviews or meta-analyses have studied the relationship between temperament or personality and ADHD in children and adolescents to confirm these associations, considering all the available data. In a meta-analysis, Solmi et al. investigated the relationship between the Temperament Evaluation Memphis, Pisa, Paris, and San Diego Auto-questionnaire (TEMPS-A) domains and mood disorders through comparisons against control groups, including ADHD.14 No significant differences in TEMPS-A domains emerged between mood disorders and ADHD, but only three studies were included in this analysis, since the TEMPS-A is not routinely used in studies of temperament or personality in ADHD. Additionally, Joseph et al. examined longitudinal studies on the association between temperament at birth to 3 years of age and subsequent ADHD.15 The authors found that activity level, sustained attention, and negative emotionality in infancy were associated with childhood ADHD. However, this does not indicate how the temperament profile of children/adolescents with ADHD compares to their typically developing peers. Finally, Gomez et al.16 investigated the relationship between personality dimensions of the five-factor model and ADHD inattention and hyperactivity/impulsivity symptom domains in children/adolescents and adults, finding that ADHD was associated with higher negative emotionality as well as lower agreeableness and conscientiousness. However, their study was conducted more than a decade ago, and a more recent examination of all the available evidence is necessary.
Therefore, our study aimed to address this meta-analytical gap on the associations between temperament/personality domains and ADHD status. Focusing on children and adolescents, we conducted a comprehensive evaluation of different temperament and personality models. We predicted that the following domains would be associated with ADHD status: higher negative affectivity/emotionality, lower effortful control/self-regulation, and higher surgency/extraversion.
METHODS
The present review was not prospectively registered, and no previous protocol was written. This study was reported according to Preferred Reporting Items for Systematic Reviews and Meta-Analysis (PRISMA) guidelines.17
Study identification and selection
Literature searches were conducted in PubMed, PsycINFO, and Web of Science in October 2021, and the PubMed search was updated in September 2024 with no language restrictions. For full search terms, see Supplementary Box S1. Review articles and meta-analyses on temperament/personality and ADHD were carefully read to find other potentially eligible articles, as were the reference lists of the included articles.
We included cross-sectional or longitudinal case-control studies in which all participants were children and adolescents (= 18 years of age). The cases had been diagnosed with ADHD (study-defined, without restrictions), and the controls had not (study-defined, without restrictions). We also required studies to report the use of an instrument to assess temperament or personality in their data collection efforts. However, we did not set any restrictions on the specific instrument.
We excluded studies that only evaluated ADHD symptoms in a general population sample without clearly determining groups of individuals with and without ADHD. We also excluded studies that selected children from special populations, e.g., incarcerated youth or victims of acute/chronic maltreatment, since we were concerned that the findings would not be generalizable to the larger pool of individuals with ADHD.
All study titles and abstracts were examined by two independent authors for eligibility (MVMF, LB). The full texts of articles apparently meeting inclusion criteria were then evaluated in detail by two independent authors (MVMF, LB) to determine eligibility. Any disagreements were resolved through discussion with a third independent reviewer (LCF, GVP).
Data extraction
Data extraction was initially performed by one of the authors, and the extracted data were then reviewed by another author to ensure accuracy and completeness. Any discrepancies, uncertainties, or missing information identified during this process were discussed and resolved through consensus between the two reviewers. The data were extracted using a specially designed Excel spreadsheet. The extracted data included information on the study (author name; country of sample recruitment; publication year; study design [cross-sectional, nested in cohort study]), the participants (sample size, mean age (SD), the percentage of boys, diagnostic criteria, proportion of ADHD subtypes, ADHD symptom severity, the percentage of participants with comorbid psychiatric conditions), and outcomes. We also assessed risk of bias with the Newcastle-Ottawa Scale.
The outcome data included the number of cases (that is, participants with ADHD) and controls (that is, participants without ADHD) as well as their corresponding means (SD) in different domains of temperament/personality scales.
Statistical analysis
We used the standardized mean difference (SMD) as the effect size index. We calculated the SMD to determine the magnitude of the shift in the distribution curve of each temperament domain (as measured by different instruments) in units of SD in cases vs controls. When a domain was investigated by at least three studies, we pooled the data using generic (inverse of the variance) random-effects meta-analyses. Heterogeneity was assessed using the I2 statistic. All meta-analyses were graphically represented in forest plots. If a meta-analysis included > 10 studies, we investigated publication bias through a funnel plot and the Egger regression test. All analyses were performed in R using the meta package. As requested during the peer review process, we also conducted outlier detection with the dmetar package. We re-estimated the meta-analyses without outliers in sensitivity analyses to test the robustness of the findings.
RESULTS
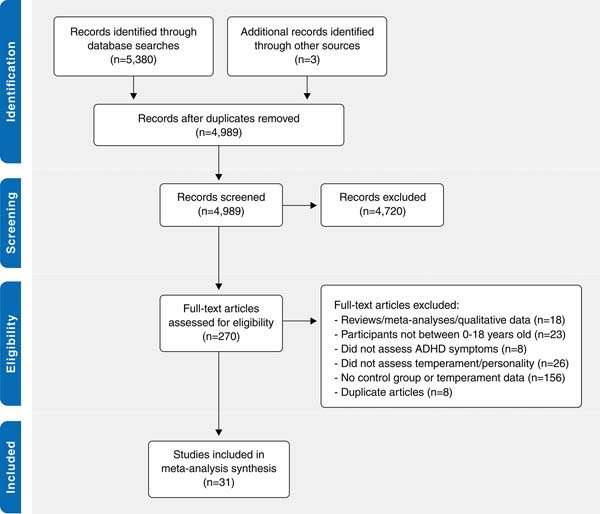
The selection process for eligible studies was illustrated in a PRISMA flow diagram (Figure 1). Thirty-one articles were included in the meta-analyses, and their characteristics are described in Table 1. All studies compared individuals with ADHD against typically developing controls. In the following sections, we present the results for each temperament or personality domain. The results from individual studies (i.e., effect sizes) are shown in the Supplementary Results. The risk of bias assessments for each study are present in Supplementary Table S1.

| Study | Country | Sample size | Age, range (mean [SD]) | Male, % | Diagnostic reference criteria | ADHD scale for diagnosis/severity | Temperament scales | Temperament construct |
|---|---|---|---|---|---|---|---|---|
| Alperin et al.18 | USA | 109 | (13.8 [1.2])┼ | 73 | DSM-5 | Conners | EATQ | Rothbart |
| Bauer et al.19 | USA | 623 | 7-12 (9.2 [1.5]) | 62 | DSM-5 | Conners | TMCQ | Rothbart |
| Bouvard et al.20 | FR | 70 | (12.7 [2.6])┼ | 84 | ┼ | ┼ | EAS; BFQ-C | Buss & Plomin; FFM |
| Bussing et al.21 | USA | 196 | (10.3 [1.4])┼ | 48 | DSM-IV | DISC-IV | DOTS-R | Thomas & Chess |
| De Pauw22 | BE | 509 | 6-14 (┼ [┼]) | 85 | DSM-IV TR | DBDRS | EATQ-R; EAS; HiPIC | Rothbart; Buss & Plomin; FFM |
| Donfrancesco et al.23 | IT | 339 | (9.5 [2.4])┼ | 89 | DSM-IV | KSADS | JTCI | Cloninger |
| Drechsler et al.24 | CH | 111 | 7-11 (8.8 [1.2]) | 74 | ICD-10 | ┼ | JTCI | Cloninger |
| Foley et al.25 | USA | 55 | 6-11 (8.7 [1.7]) | 65 | DSM-IV | Conners | CBQ; SATI | Rothbart; Thomas & Chess |
| Healey & Rucklidge.26 | NZ | 59 | 10-12 (11.3 [0.9]) | 57 | DSM-IV | Conners | JTCI | Cloninger |
| Jallow et al.27 | FI | 378 | 16-18 (┼ [┼]) | 63 | DSM-IV | KSADS | TCI | Cloninger |
| Kang & Kwack28 | KR | 80 | 6-12 (8.6 [1.7]) | 85 | DSM-IV | CBCL | JTCI | Cloninger |
| Karalunas et al.29 | USA | 437 | 7-11 (8.8 [1.3]) | 61 | DSM-5 | KSADS | EATQ | Rothbart |
| Kim et al.30 | KR | 167 | (10.4 [3.0])┼ | ┼ | DSM-IV | CBCL | JTCI | Cloninger |
| Krieger et al.31 | ES | 118 | 12-16 (13.5 [1.3]) | 64 | DSM-5 | CRS | BFQ-C | FFM |
| Love32 | USA | 70 | 5-8 (7.0 [0.8]) | ┼ | DSM-3R | ┼ | TABC-P | Thomas & Chess |
| Martel et al.33 | USA | 179 | 6-12 (9.5 [1.2]) | 63 | DSM-IV | CRS | EATQ; CCQ | Rothbart; FFM |
| Martel et al.34 | USA | 184 | 13-18 (5.4 [1.1]) | 58 | DSM-IV | CRS | CCQ | FFM |
| Martel et al.35 | USA | 548 | 6-18 (11.7 [3.0]) | 58 | DSM-IV | ADHD-RS | EATQ-R; CCQ | Rothbart |
| Martel et al.36 | USA | 109 | 3-6 (4.8 [1.1]) | 59 | DSM-IV | K-DBDS | CBQ | Rothbart |
| McNamara et al.37 | CA | 414 | 13-18 (15.8 [1.4]) | ┼ | ┼ | ┼ | DOTS-R | Thomas & Chess |
| Melegari et al.38 | IT | 60 | (4.6 [0.8])┼ | 85 | DSM-IV TR | PAPA | PsTCI | Cloninger |
| Melegari et al.39 | IT | 47 | 4-6 (5.2 [1.1]) | 75 | DSM-IV | PAPA | PsTCI | Cloninger |
| Moon et al.40 | KR | 48 | (12 [┼])┼ | 85 | ┼ | ┼ | JTCI | Cloninger |
| Polier et al.41 | DE | 66 | 7-16 (11.6 [2.3]) | 100 | DSM-IV TR | ADHD-RS | JTCI | Cloninger |
| Prior et al.42 | AU | 40 | 2-5 (4 [0.6]) | 85 | DSM-3 | ADHD-RS | PTQ | Thomaz & Chess |
| Purper-Ouakil et al.43 | FR | 192 | 10-18 (13.2 [1.5]) | ┼ | DSM-IV | ADHD-RS | JTCI | Cloninger |
| Rettew et al.44 | USA | 83 | 6-18 (10.6 [3.0]) | 49 | DSM-IV | ADHD-RS | JTCI | Cloninger |
| Taskiran et al.45 | TR | 50 | 6-12 (8.5 [1.6]) | 79 | DSM-IV | CRS | SATI | Thomas & Chess |
| Ucuz et al.46 | TR | 76 | 9-14 (10.5 [┼]) | ┼ | DSM-IV | KSADS | JTCI | Cloninger |
| Volckaert & Noël.47 | BE | 98 | 3-6 (5.0 [0.6]) | 51 | DSM-IV | CRS | CCTI | Buss & Plomin |
| Yoo et al.48 | KR | 104 | 9-14 (11 [1]) | 49 | DSM-IV | ADHD-RS | JTCI | Cloninger |
ADHD-RS = Attention-Deficit/Hyperactivity Disorder Rating Scale; AU = Australia; BE = Belgium; BFQ-C = Big Five Questionnaire for Children; BSQ = Behavioral Style Questionnaire; CA = Canada; CADS = Child and Adolescent Dispositions Scale; CBCL = Child Behavior Checklist for ages 6-18; CBQ = Children's Behavior Questionnaire; CCQ = California Q-Sort; CCTI = Colorado Childhood Temperament Inventory; CH = Switzerland; CHTQ = Cyclothymic-Hypersensitive Temperament Questionnaire; CRS = Conners' Rating Scale; DE = Germany; DOTS-R = Revised Dimensions of Temperament Scale-Child; EAS = Emotionality Activity Sociability Temperament Survey; EATQ-R = Early Adolescent Temperament Questionnaire - Revised; ES = Spain; FFM = five-factor model; FI = Finland; FR = France; HiPIC = Hierarchical Personality Inventory for Children; JTCI = Junior Temperament and Character Inventory; K-DBDS = Disruptive Behavior Disorder Rating Scale; KR = South Korea; KSADS = Schedule for Affective Disorders and Schizophrenia for School-Age Children; NTTS = Nine Types Temperament Scale; NZ = New Zealand; PAPA = Preschool Age Psychiatric Assessment; PsTCI = Preschool Temperament and Character Inventory; PTQ = Parent Temperament Questionnaire of Thomas and Chess; SATI = School-Age Temperament Inventory; TABC-R = Temperament Assessment Battery for Children - Revised; TCI = Temperament and Character Inventory; TMCQ = Temperament in Middle Childhood Questionnaire; TR = Türkiye; USA = United States of America.
┼ = missing information.

Rothbart's construct
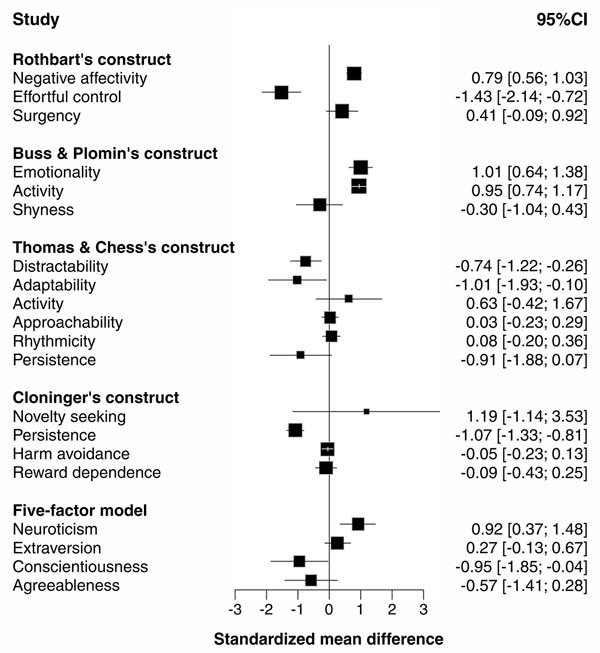
There was evidence of higher negative affectivity (k = 5; n=1,806; SMD = 0.79; 95%CI 0.56 to 1.03) and lower effortful control (k = 5; n=1,426; SMD = -1.43; 95%CI -2.14 to -0.72) in individuals with ADHD than in typically developing controls (Figure 2). There was no evidence of an association with surgency (k = 5; n=1,238; SMD = 0.41; 95%CI -0.09 to 0.92) (Figure 2). However, all three meta-analyses had substantial heterogeneity (negative affectivity: I2 = 67%; effortful control: I2 = 95.8%; I2 = 82.3%).

Buss & Plomin's construct
There was evidence of higher emotionality (k = 3; n=687; SMD = 1.01; 95%CI 0.64 to 1.38) and activity (k = 3; n=687; SMD = 0.96; 95%CI 0.74 to 1.17) in individuals with ADHD than in typically developing controls (Figure 2). There was no evidence of an association with shyness (k = 3; n=687; SMD = -0.30; 95%CI -1.04 to 0.43) (Figure 2). Heterogeneity was moderate (I2 = 61%) and high (I2 = 91.3%) for the meta-analyses of emotionality and shyness, respectively. There was no evidence of heterogeneity (I2 = 0%) for activity.
Thomas & Chess's construct
There was evidence of lower distractibility (k = 4; n=720; SMD = -0.74; 95%CI -1.22 to -0.26) and lower adaptability (k = 3; n=306; SMD = -1.01; 95%CI -1.93 to -0.10) in individuals with ADHD than in typically developing controls (Figure 2). There was no evidence of an association with activity (k = 5; n=770; SMD = 0.63; 95%CI -0.42 to 1.67), approachability (k = 5; n=770; SMD = 0.03; 95%CI -0.23 to 0.29), rhythmicity (k = 3; n=650; SMD = 0.08; 95%CI -0.20 to 0.36), or persistence (k = 4; n=574; SMD = -0.91; 95%CI -1.88 to 0.07) (Figure 2). There was evidence of moderate (approachability: I2 = 55%; rhythmicity: I2 = 51%) or high (distractibility: I2 = 77%; adaptability: I2 = 90%; activity: I2 = 98%; persistence: I2 = 90%) heterogeneity for all meta-analyses. After removing outliers, the interpretation of the findings did not substantially change (activity: k = 3, n=504, SMD = 0.57, 95%CI -1.29 to 2.43).
Cloninger's construct
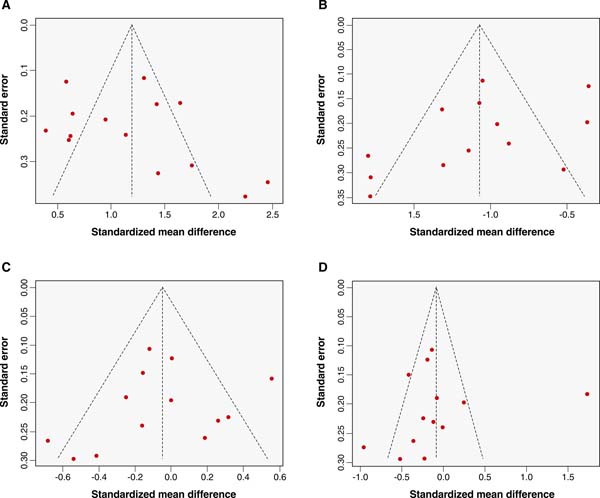
There was evidence of higher novelty seeking (k = 14; n=1,829; SMD = 1.19; 95%CI 0.87 to 1.51) and lower persistence (k = 13; n=1,763; SMD = -1.07; 95%CI -1.33 to -0.81) in individuals with ADHD than in typically developing controls (Figure 2). There was no evidence of an association with harm avoidance (k = 13; n=1,763; SMD = -0.05; 95%CI -0.22 to 0.13) or reward dependence (k = 13; n=1,763; SMD = -0.09; 95%CI -0.43 to 0.25) (Figure 2). There was evidence of moderate or high heterogeneity for all meta-analyses (novelty seeking: I2 = 85%; persistence: I2 = 81%; avoidance: I2 = 62%; reward dependence: I2 = 90%). Although visual inspection of funnel plots indicated slight asymmetries, they were not statistically significant in Egger regression tests (Figure 3). After removing outliers, the interpretation of the findings did not substantially change (harm avoidance: k = 12, n=1,704, SMD = -0.06, 95%CI -0.25 to 0.12; novelty seeking: k = 9, n=1,173, SMD = 1.07, 95%CI 0.76 to 1.39; persistence: k = 10, n=1,144, SMD = -1.05, 95%CI -1.4 to -0.7; reward dependence: k = 12, n=1,704, SMD = -0.07, 95%CI -0.44 to 0.30).
Five-factor model construct
There was evidence of higher neuroticism (k = 5; n=1,043; SMD = 0.92; 95%CI 0.37 to 1.48), higher extraversion (k = 6; n=1,562; SMD = 0.27; 95%CI -0.13 to 0.67), and lower conscientiousness (k = 5; n=1,562; SMD = -0.95; 95%CI -1.85 to -0.04) in individuals with ADHD than in typically developing controls (Figure 2). There was no evidence of an association with agreeableness (k = 6; n=1,562; SMD = -0.57; 95%CI -1.41 to 0.28) (Figure 2). There was evidence of substantial heterogeneity for all meta-analyses (neuroticism: I2 = 89%; extraversion: I2 = 89%; conscientiousness: I2 = 96%; agreeableness: I2 = 96%). After removing outliers, the interpretation of the findings did not substantially change (agreeableness: k = 4, n=952, SMD = -0.4, 95%CI -1.71 to 0.9; conscientiousness: k = 5, n=1,061, SMD = -1.12, 95%CI -2.15 to -0.1; neuroticism: k = 4, n=542, SMD = 1.07, 95%CI 0.43 to 1.71).
DISCUSSION
The present meta-analysis of case-control studies investigated the associations between temperament or personality traits and ADHD in children and adolescents. We included studies that used any questionnaire to measure these constructs. Considering different temperament or personality scales, our results showed that children and adolescents with ADHD had higher emotionality/negative affectivity/neuroticism than their typically developing peers. The results also revealed that children and adolescents with ADHD had decreased effortful control/persistence, although the Thomas & Chess persistence domain did not differ between children with and without ADHD. Additionally, the results showed mixed findings regarding extraversion, with some constructs indicating differences (Buss & Plomin activity and Cloninger novelty seeking), although others did not (Rothbart surgency, Buss & Plomin shyness, Thomas & Chess activity/approachability, Cloninger reward dependence, and five-factor model extraversion). Besides these main findings, Thomas & Chess rhythmicity, Cloninger harm avoidance, and five-factor model agreeableness were not significantly associated with ADHD.
The finding of an association between increased negative affectivity/emotionality/neuroticism and ADHD is not surprising and reinforces a clinical problem for those who treat children and adolescents with ADHD.49 Emotional dysregulation has been historically described among individuals with ADHD,50 and it is a major characteristic in many children with ADHD who reach clinical attention.17 Additionally, emotional dysregulation in the context of ADHD may have long-term consequences, such as an increased risk of depressive disorders during development.51,52
The association between decreased effortful control/persistence/conscientiousness and ADHD was also expected. However, for persistence (Thomas & Chess construct), we found no difference between the groups. It is possible that one divergent study in the meta-analysis contributed to the non-significant findings.42 In that study, ADHD diagnoses were based on a score of = 15 on the Conners 10-item Parent Abbreviated Symptom Questionnaire, whereas the other studies included participants with a DSM diagnosis of ADHD. Impulsivity (i.e., reactive under control) is at the core of ADHD symptomatology, and decreased regulation (i.e., effortful control) may contribute to individuals with ADHD engaging in certain risk-taking behaviors, such as substance use and precocious sexual activity.53
Finally, we found conflicting data regarding the associations between surgency/extraversion and ADHD, and more research is required to clarify these findings. Because our study focused on averages, we cannot rule out that a small group of individuals with ADHD may have increased surgency/extraversion. Some investigators argue that the field should focus on surgency/extraversion to potentially identify subgroups of children with ADHD. Additional research considering individual-level, rather than study-level, data should help clarify whether this point is indeed valid.
These findings should be interpreted considering several study limitations. First, it is striking that so few studies reported all temperament or personality subscales from the instruments they used. While it is possible that this reflects the use of specific subscales only (especially considering the number of items in each of these scales), there is concern that the scales were selectively reported or non-reported, which would introduce bias into the meta-analyses. There was also considerable heterogeneity among the temperament or personality scales, some of which could not be compared to the most used scales. This created difficulties when pooling the data for meta-analysis. For this reason, we only combined studies that used the same instruments. Additionally, a considerable proportion of the total variability was due to between-study heterogeneity across virtually all meta-analyses. Indeed, the studies differed considerably about how cases and controls were defined. We also cannot confidently rule out the possibility that the averages were influenced by individual studies, given the relatively small amount of data available in each meta-analysis. As a result, overall, the meta-analyses provide relatively limited evidence about the temperament and personality profile of children and adolescents with ADHD. Further research involving individuals who are representative of the general population and appropriately matched controls is needed. Additionally, the data were based on cross-sectional case-control studies. A longitudinal design is one of the most important parameters for assessing the validity of psychiatric phenomena, and it would have been interesting to explore associations between these temperament/personality profiles and longitudinal outcomes in children and adolescents with ADHD. Similarly, many studies did not provide relevant information about comorbidities or ADHD presentation or severity. Hence, we could not explore specific associations that might have been clinically informative.
In conclusion, our meta-analysis highlights a possible temperamental/personality pattern in the ADHD phenotype. Specifically, our study showed that children and adolescents with ADHD may have higher negative emotionality and lower effortful control than their typically developing peers.
SUPPLEMENTARY MATERIALS
DISCLOSURE
GVP has been a consultant, advisory board member, and/or speaker for Aché, Abbott, Apsen, Adium, Medice, and Takeda, and receives royalties from Editora Manole. The other authors report no conflicts of interest.
DATA AVAILABILITY STATEMENT
The data that support this study are available from the authors upon request.
AUTHOR CONTRIBUTIONS
MVMF: Conceptualization, Data curation, Methodology, Project administration, Visualization, Writing - original draft, Writing - review & editing.
LB: Data curation
LCF: Conceptualization, Formal analysis, Methodology, Supervision, Writing - review & editing
GVP: Conceptualization, Methodology, Supervision, Writing - review & editing
All authors have read and approved the final version to be published.
Handling Editor: Arthur Caye
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



