



ABSTRACT:
OBJECTIVES: The effects of transcranial direct current stimulation over the prefrontal cortex
on reactive aggressive behavior are unclear. We conducted an updated systematic review
and meta-analysis of randomized controlled trials comparing the effects of anodal
transcranial direct current stimulation vs. sham stimulation on reactive aggressive
behavior in healthy volunteers experimentally induced to aggressive behavior.
METHODS: We systematically searched the PubMed, Cochrane, Embase, and PsycInfo databases for
randomized controlled trials comparing transcranial direct current stimulation to
sham stimulation over the prefrontal cortex on reactive aggressive behavior. We computed
the standardized mean difference (SMD) with 95%CIs for all statistical models. Heterogeneity
was assessed using I 2 statistics. The statistical analyses were performed in R 4.5.1.
RESULTS: We included nine trials with 547 participants, of whom 272 (49.7%) underwent anodal
transcranial direct current stimulation. There was no significant difference between
anodal transcranial direct current stimulation and sham stimulation regarding reactive
aggressive behavior (SMD -0.24; 95%CI [-0.54 to 0.05]; p = 0.09; I 2 = 52.4%). However, subgroup analysis showed that the effects of online (SMD -0.41;
95%CI [-0.61 to -0.20]; I 2 = 0%), and unilateral (SMD -0.44; 95%CI [-63 to -0.25]; I 2 = 0%) transcranial direct current stimulation differed significantly from sham stimulation.
CONCLUSIONS: While anodal transcranial direct current stimulation had no significant effect on
reactive aggressive behavior in healthy volunteers in the overall analysis, the results
suggest that online and unilateral tDCS may have an impact. Given the heterogeneity
of the studies and outcome measures, further research is needed to confirm these findings
and better understand the role of transcranial direct current stimulation in modulating
reactive aggressive behavior.
REGISTRATION NUMBER: PROSPERO CRD420251002415.
Keywords: Reactive aggressive behavior; transcranial direct current stimulation; prefrontal cortex; healthy volunteers; meta-analysis.
FIGURES
| Note: How to cite this article: Sikembi PT, Batista AD, Monteiro WS, Medina PAV, Yu L, de Oliveira AJM, et al. The effects of transcranial direct current stimulation over the prefrontal cortex on reactive aggressive behavior in healthy volunteers: a systematic review and meta-analysis of randomized controlled trials. Braz J Psychiatry. 2026;48:e20254514. Epub 2025 Oct 31. http://doi.org/10.47626/1516-4446-2025-4514 |
| Received: August 18 2025; Accepted: October 08 2025 |
INTRODUCTION
Aggressive behavior represents a significant health problem for victims and society, leading to family conflict, crime, murder, rape, and theft.1 According to distinct motivations, aggressive behavior may be categorized into different subtypes: proactive aggression, which is planned and unprovoked, and reactive aggression, which occurs in reaction to provocation.2-4 Reactive aggressive behavior has been associated with attention deficit hyperactivity disorder, depression, and anxiety.5-7 The prefrontal cortex (PFC) plays a crucial role in regulating aggressive behavior. It achieves this by transmitting inhibitory signals to subcortical brain regions, such as the nucleus accumbens, which is associated with the reward system.8 Research has also shown that the PFC has an asymmetric effect on aggressive behavior.9
Given the serious consequences of aggressive behavior, neuromodulatory techniques such as transcranial direct current stimulation (tDCS) and repetitive transcranial magnetic stimulation have been proposed. Compared to transcranial magnetic stimulation, tDCS is less expensive, safer and easier to perform.10 tDCS typically involves applying either anodal or cathodal currents. Anodal tDCS is known to increase neuronal excitability, while cathodal tDCS generally leads to a decrease in neuronal excitability.11 Although tDCS PFC has shown promise in reducing aggressive behavior, some studies have reported no significant effects.12-16
A previous meta-analysis of randomized controlled trials in healthy volunteers experimentally induced to aggressive behavior demonstrated that a single session of tDCS targeting the PFC significantly decreased risk-taking, bias, and overeating compared to sham stimulation. However, the analysis found no significant effects on aggression, and none of the tDCS parameters exhibited significant interactions. Additionally, neither sub-analysis nor subgroup analysis including reactive aggressive behavior were conducted. This lack of broader effects might be attributed to the limited number of studies included in that meta-analysis.17 Therefore, we conducted an updated systematic review and meta-analysis of randomized controlled trials comparing the efficacy of tDCS to sham stimulation on reactive aggressive behavior.
METHODS
This systematic review and meta-analysis was registered in the international Prospective Register of Systematic Reviews (protocol CRD420251002415) and was designed according to the Preferred Reporting Items for Systematic Reviews and Meta-Analysis reporting guidelines.18
Study eligibility
We included studies that met the following eligibility criteria: 1) randomized controlled trials, 2) comparing a single session of anodal tDCS to sham stimulation, 3) in healthy human subjects experimentally induced to aggressive behavior, 4) reporting aggressive behavior as one of the outcomes of interest, and 5) published in English. We excluded: 1) studies involving patients with mental disorders, 2) drug users, 3) multi-session tDCS, or 4) overlapping populations (using only the study with the larger sample size).
Search strategy and data extraction
The PsycINFO, PubMed, Cochrane, and Embase databases were systematically searched on March 2, 2025. The search strategy was as follows: (aggression OR "aggressive behavior" OR aggressiveness) AND ("prefrontal cortex stimulation" OR "DLPFC Stimulation" OR "VLPFC Stimulation" OR "Ventromedial prefrontal cortex stimulation" OR "VmPFC stimulation" OR "transcranial direct current stimulation" OR tDCS).
We extracted data on: 1) study design, 2) dose, 3) duration, 4) online/offline parameters, 5) PFC subregion, 6) hemisphere, 7) electrode size, 8) tools used for outcome measurement, and (9) aggressive behavior and intent to commit aggression scores. All identified articles were assessed using the inclusion and exclusion criteria. Article selection and data extraction were performed independently by two authors (PTS and ADB). Disagreements were resolved by consensus.
Although we intended to extract standard deviations and means for each outcome, most studies reported the F-statistic and Cohen's d effect size, which led us to estimate standard error according to Statistical Power Analysis for the Behavioral Sciences.19 For reports with two hemispheres stimulated unilaterally, each hemisphere was treated as an independent study. Whenever necessary, we attempted to contact the authors for further information.
Quality assessment
The revised Cochrane risk of bias tool for randomized trials was used by two independent authors (PTS and ADB) to assess the quality of the randomized studies; disagreements were resolved by consensus. Publication bias was assessed through visual analysis of funnel plot asymmetry. We could not perform Egger's test due to the limited number of studies.
Data analysis
Stimulation condition effects were compared using pooled standardized mean differences (SMD) with 95%CI. We used the random-effect model with inverse-variance method. Heterogeneity was examined using the Cochran Q test, I 2 statistic, and tau-square using the restricted maximum-likelihood estimator and random effect model. Heterogeneity was reported as low (I 2 = 0-25%), moderate (I 2 = 26-50%), or high (I 2 > 50%). Due to the small sample size of some studies, we applied the Hartung-Knapp adjustment method to improve the accuracy of CI and control for type I error inflation. Unlike the DerSimonian-Laird method, which constructs CI using a normal (z-value) distribution, the Hartung-Knapp approach uses a t-distribution.20
We performed a prespecified sensitivity analysis for aggressive behavior, excluding studies with a high contribution to heterogeneity according to Baujat plot and leave-one-out analysis to ensure that the results were not dependent on a single study. A further sensitivity analysis was performed using the DerSimonian-Laird method as recommended by current evidence.20 Additionally, we performed a meta-regression for dose and duration, and subgroup analysis according to the stimulated PFC subregion, online/offline stimulation, hemisphere, and unilateral/bilateral montage. All statistical analyses were performed in R 4.5.1, using the meta and metafor extension packages.
RESULTS
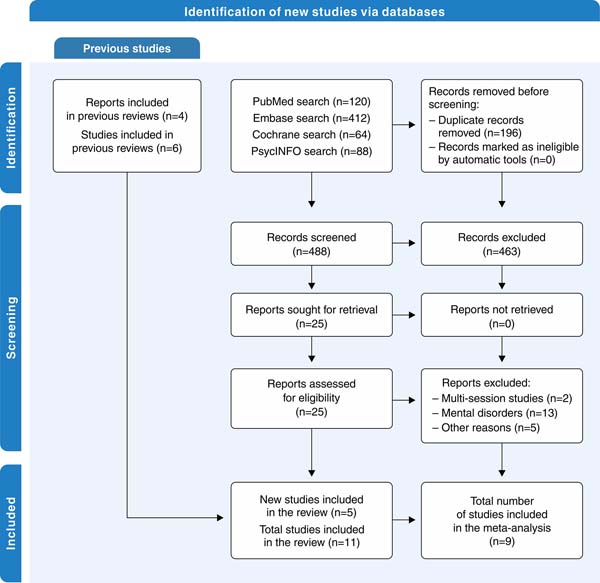
Our systematic search yielded 684 records, as detailed in Figure 1. After removing duplicates and unrelated studies, 25 were fully assessed for eligibility. Of these, 11 met the inclusion criteria and were included in the systematic review, while nine were included in the meta-analysis. Two studies were excluded from the meta-analysis because they did not provide a sample per treatment arm and the authors did not respond to our request. The pooled analysis included 547 healthy volunteers, of whom 272 (49.7%) underwent anodal tDCS. The studies' baseline characteristics and detailed statistical data are shown in Supplementary Table S1 and S2, respectively.

Pooled analysis of all studies
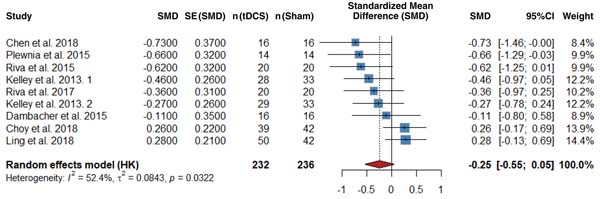
Overall, compared to sham stimulation, anodal tDCS did not significantly affect reactive aggressive behavior (SMD -0.24; 95%CI [-0.54 to 0.05]; p = 0.09; I 2 = 52.4) (Figure 2).

Subgroup analysis
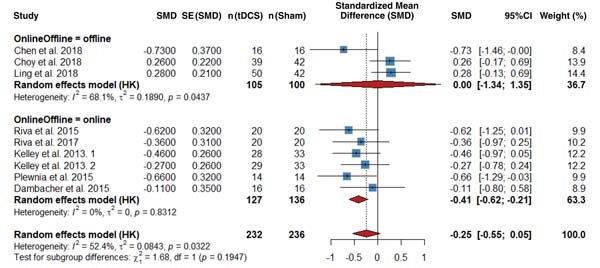
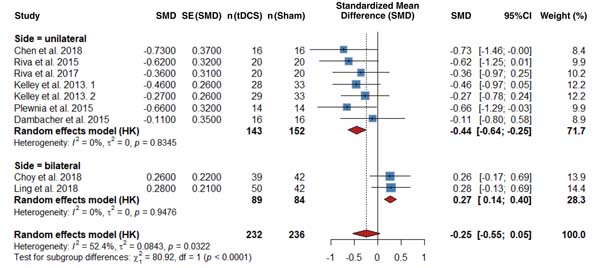
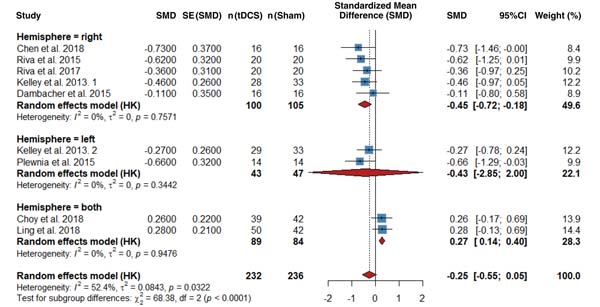
Although anodal tDCS did not significantly affect reactive aggressive behavior, the subgroup analysis showed significant effects of online tDCS vs. sham stimulation (SMD -0.41; 95%CI [-0.61 to -0.20]; I 2 = 0%) (Figure 3), unilateral tDCS vs. sham stimulation (SMD = -0.44 95%CI [-63 to -0.25]; I 2 = 0%) (Figure 4), bilateral tDCS vs. sham stimulation (SMD = 0.27; 95%CI [0.14 to 0.39]; I 2 = 0%) (Figure 4), tDCS vs. sham stimulation over the right hemisphere (SMD = -0.45; 95%Cl [-72 to -0.18]; I 2 = 0%) (Figure 5), and tDCS vs. sham stimulation over the right ventrolateral PFC (VLPFC) (SMD = -0.55 95%Cl [-1.02 to -0.08]; I 2 = 0%) (Supplementary Figure S1).



Subgroup analysis in relation to the outcome measurement tool showed a significant difference (Q = 74.65; degrees of freedom = 4 p-value < 0.0001), with null heterogeneity in all subgroups (Supplementary Figure S2). There were no significant differences in the effects of offline tDCS vs. sham stimulation, tDCS vs. sham stimulation over the left hemisphere, or tDCS vs. sham stimulation over the other PFC subregions (Figures 2- 5 and S1).
Sensitivity analysis and meta-regression
The meta-regression showed no significant interaction between tDCS and dose (degrees of freedom = 0.77, p-value = 0.40) or duration (degrees of freedom = 2.9134, p-value = 0.13). The meta-regression analyses are presented in Supplementary Figures S3 and S4. Sensitivity leave-one-out analysis showed a significant effect after three studies were omitted (Supplementary Figure S5). Significant results were found after outlier studies were excluded (SMD -0.48; 95%CI [-0.67 to -0.30]; p-value = 0.03) (Supplementary Figure S6 and S7). Further sensitivity analysis using the DerSimonian-Laird method did not result in statistically significant results (SMD -0.25; 95%CI [-0.51 to 0.02]; Z = -1.81 p-value = 0.0701; Supplementary Figure S8).
Quality assessment
No studies were classified as high risk of bias. One study was classified as low risk of bias, while the others were classified as moderate risk of bias since most did not report preregistration (Supplementary Table S3). We observed funnel plot asymmetry, suggesting a risk of publication bias (Supplementary Figure S9).
DISCUSSION
In this meta-analysis of nine randomized controlled trials including 547 healthy volunteers induced to aggressive behavior, anodal tDCS was compared to sham stimulation. The main findings from the overall analysis, subgroup analysis, metaregression, and sensitivity analysis are as follows: 1) anodal tDCS applied over the PFC did not significantly affect reactive aggressive behavior, and there was significant heterogeneity in the model; 2) subgroup analysis showed that online anodal tDCS, unilateral anodal tDCS, tDCS over the right hemisphere, and tDCS over the right VLPFC significantly reduced reactive aggressive behavior; 3) bilateral anodal tDCS significantly increased reactive aggressive scores; 4) the meta-regression showed a non-significant interaction effect for tDCS dose and duration; 5) leave-one-out analysis showed a significant effect after three studies were omitted from the analysis.
Over the last decade, three meta-analyses of randomized controlled trials have evaluated tDCS over the PFC on aggressive behavior and none have found significant effects.17,21,22 Our meta-analysis is consistent with the results of previous meta-analyses, including additional suggestions on the factors that could have influenced its results. Our findings suggest that the null effect of tDCS on aggressive behavior may have been influenced by the model's significant statistical heterogeneity. According to guidelines, the methodological diversity of the studies included in a meta-analysis may significantly impact the intervention's effects.18 Additionally, the lack of effect in most subregions may also have contributed to the null effect in the overall analysis. Our meta-analysis differed methodologically from previous ones by using the Hartung-Knapp adjustment method (for more conservative estimates) and by excluding clinical populations. This may have contributed to the significant differences in the subgroup analysis, which were not found in previous studies.
Our results showed that anodal tDCS applied specifically to the right VLPFC significantly reduced reactive aggression scores. This may be due to this subregion's strong anatomical and functional output connections to the amygdala, a component of the limbic system highly involved in aggressive response.23 This significant effect has been previously demonstrated.24 Only two studies reported the proportion of participants who felt pain during tDCS. The percentage of participants who felt pain during stimulation was 67.3% in the first trial and 46.9% in the second.21,25
In a randomized controlled trial, anodal tDCS over the VLPFC was compared to sham stimulation following exposure to frustration in healthy volunteers. Anodal tDCS over the left VLPFC significantly increased aggression scores, but no significant effects were detected for the right VLPFC, which aligns with our findings. Although no significant effects were found regarding the right hemisphere, this could reflect the influence of the tools used to measure aggressive behavior, due to contrasting effects on the left hemisphere. That trial used a tool involving a motivation approach rather than affective valence.26 Research shows that applying anodal tDCS over the left VLPFC and using tools focused on motivation tends to increase aggression scores; a contrary effect has been observed in studies on affective valence.27 Thus, differences in the tools used to measure aggressive scores may explain why combining data from different studies results in non-significant effects.
Additionally, studies targeting the right hemisphere have found similar results,24,28 whereas studies targeting the left hemisphere have found contrasting results.29,30 Bihemispheric stimulation of homologous subregions of the PFC have also found contrasting results.25,31 These divergent results may be due to differences in population and neuromodulatory technique. Our results also suggest that unlike offline stimulation, online stimulation may have an impact, which also aligns with the results of previous studies.24,32 In online stimulation, the electrical current and the measurement tool are applied simultaneously, which could result in stronger suppression of reactive aggressive behavior than offline stimulation, in which the measurement tool is applied after the current.
Our findings address important issues in this field. Future studies should standardize the tasks used to induce participants to aggressive behavior, as well as the tools used to measure aggression. Researchers should also focus on the role of the right VLPFC in reactive aggressive behavior to confirm our results from a small number of studies. To confirm our findings, future studies should also investigate the effects of online tDCS, unilateral tDCS, and tDCS over the right hemisphere on reactive aggressive behavior in patients with mental disorders, such as attention deficit hyperactivity disorder, anxiety, and depression.
Our meta-analysis has several important limitations. First, our analysis focused on healthy volunteers to isolate the neurobehavioral effects of anodal tDCS on reactive aggression, without confounding from comorbidities or medications. While this limits direct generalizability to clinical populations, it offers essential foundational evidence and safety data to guide future studies involving populations in which reactive aggression is more prevalent. Second, the samples of most included studies were small, which could have reduced the statistical power of the results. Third, the overall model showed high heterogeneity, likely due to methodological differences among the studies. Fourth, few studies have investigated the effects of tDCS over the right VLPFC, which weakens our results in this model. Fifth, the lack of a significant effect for offline tDCS may have been influenced by studies that applied bilateral stimulation. Sixth, most of the studies did not report preregistration, which raises concerns about selective reporting and publication bias. Seventh, although only two studies reported the proportion of participants who experienced sensory effects, such as pain, during stimulation, this is consistent with the literature, as clinically significant pain is uncommon in single-session tDCS studies with healthy volunteers. Mild transient sensations (e.g., tingling or itching) are the most frequently reported effects, and there is little evidence that such sensations meaningfully alter aggressive behavior outcomes in this population.33 Consequently, while we could not perform a pooled analysis for this outcome, the likelihood that pain materially influenced the effect sizes of individual studies and thus, the results of this meta-analysis, appears low. Finally, all of the included studies examined the effects of single-session tDCS, limiting generalizations to multi-session treatments, which may be more effective for this psychiatric problem.
In conclusion, in healthy volunteers induced to aggressive behavior, anodal tDCS applied over the PFC did have a significant effect on overall reactive aggressive behavior. Subgroup analysis showed positive significant effects for online anodal tDCS, unilateral anodal tDCS, and anodal tDCS over the right VLPFC.
Future trials in clinical populations should prioritize online, unilateral anodal tDCS to the right VLPFC that is administered concurrently with validated provocation tasks, given our subgroup results for online stimulation, unilateral montages, and right-hemisphere/right VLPFC targeting. These studies should adopt rigorous sham-controlled, preregistered designs with standardized adverse-event monitoring and blinding checks to enhance internal validity and translational relevance.
SUPPLEMENTARY MATERIALS
DISCLOSURE
The authors report no conflict of interest.
DATA AVAILABILITY STATEMENT
The data that support this study are available in the body of the paper and/or supplementary materials.
AUTHOR CONTRIBUTIONS
PTS: Conceptualization, Investigation, Methodology, Formal analysis.
ADB: Data curation, Resources.
WSM: Data curation, Software.
PAVM: Formal analysis, Software.
LY: Writing - review & editing.
AJMO: Validation.
RLOA: Methodology, Supervision, Writing - original draft.
All authors have read and approved of the final version to be published.
Handling Editor: Gustavo Medeiros
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



