



ABSTRACT:
OBJECTIVE: N-acetylcysteine is a medication known for its hepatoprotective properties and potential
to reduce cravings and psychoactive substance use. Vitamin D is metabolized in the
liver, and individuals with alcohol use disorder often have lower levels. This study
assessed the effects of N-acetylcysteine administration on 25-hydroxyvitamin D (25[OH]D)
in adults being treated for alcohol use disorder.
METHODS: This is a secondary analysis of a randomized, double-blind, placebo-controlled study
with 47 male alcohol use disorder patients who received either N-acetylcysteine (600
mg twice daily, n=22) or placebo (n=25) for 8 weeks. Blood samples were analyzed to
assess 25(OH)D levels, liver and renal functions, and glutathione metabolism. The
effects of time, intervention, and their interaction on 25(OH)D level were evaluated
using generalized estimating equations.
RESULTS: Upon hospitalization, 45% and 21.7% of the patients had 25(OH)D deficiency and insufficiency,
respectively. After 8 weeks, 43.3% and 40% of the patients had 25(OH)D deficiency
and insufficiency, respectively. Intervention (N-acetylcysteine vs. placebo) (p =
0.130), study time (p = 0.429), and their interaction (p = 0.834) showed no significant
effect on 25(OH)D levels.
CONCLUSIONS: There is a high prevalence of 25(OH)D deficiency and insufficiency in alcohol use
disorder patients. Levels of 25(OH)D did not improve spontaneously with abstinence,
and N-acetylcysteine intervention did not significantly affect 25(OH)D concentrations.
CLINICAL TRIAL REGISTRATION: Clinical Trials, NCT03018236.
Keywords: Alcoholism; acetylcysteine; cholecalciferol; glutathione; liver.
FIGURES
| Note: How to cite this article: Piazza FRG, Schuch JB, Silvello D, Gabiatti MP, Kessler FHP, von Diemen L, et al. Serum 25-hydroxyvitamin D levels did not improve with N-Acetylcysteine administration or with abstinence in adults treated for alcohol use disorder: a secondary analysis of a randomized, double-blind, placebo-controlled clinical trial. Braz J Psychiatry. 2026;48:e20254304. Epub 2025 Oct 31. http://doi.org/10.47626/1516-4446-2025-4304 |
| Received: May 02 2025; Accepted: October 13 2025 |
INTRODUCTION
Alcohol use disorder (AUD) is a chronic condition characterized by compulsive alcohol consumption despite harmful consequences.1 It is among the most prevalent and least-treated mental disorders globally,2 contributing to approximately 10% of all deaths among individuals aged 15 to 49.3 In Brazil, 1.5% of the population is estimated to be alcohol dependent,4 with a higher prevalence among men.5
AUD is associated with various metabolic and nutritional deficiencies, including reduced serum levels of 25-hydroxyvitamin D (25[OH]D).6 Hypovitaminosis D can affect multiple physiological systems, such as bone and musculoskeletal health,7 as well as immune function,8 potentially worsening overall health in individuals with AUD. The mechanisms underlying this deficiency are not fully understood but likely involve alcohol-induced liver dysfunction, as excessive alcohol consumption can result in a spectrum of liver diseases.9 Vitamin D metabolism involves two hydroxylation steps: the first occurs in the liver, converting vitamin D2 or D3 into 25(OH)D; the second occurs in the kidneys, where 25(OH)D is converted into its biologically active form - vitamin D (1,25-dihydroxycholecalciferol - 1,25(OH)2D3).10
Despite the well-established diagnostic criteria for AUD, pharmacological treatment remains limited in both effectiveness and applicability.11 For instance, disulfiram is contraindicated in patients with certain chronic illnesses,12 and acamprosate is generally more effective following complete detoxification.13 Current treatment approaches prioritize motivational interviewing, relapse prevention, cognitive behavioral therapy, and hospitalization.14 N-acetylcysteine (NAC) has emerged as a potential adjuvant therapy due to its ability to reduce alcohol-seeking behavior and enhance abstinence maintenance in animal models.15,16 NAC also exhibits hepatoprotective properties, allowing for continuous administration even in patients with hepatic dysfunction.17
As a cysteine precursor, NAC is essential for the synthesis of glutathione (GSH), a major hepatic antioxidant.18 Thus, NAC may indirectly influence vitamin D metabolism, as GSH deficiency exacerbates oxidative stress and downregulates the expression of key components involved in vitamin D metabolism, such as vitamin D binding protein, vitamin D receptor, and the enzyme 25-hydroxylase.19 Additionally, L-cysteine supplementation has been shown to increase serum levels of GSH, vitamin D binding protein, and 25(OH)D.20 In patients with diabetes, GSH levels have been positively correlated to both L-cysteine and 25(OH)D concentrations,21 suggesting a potential regulatory axis between NAC, cysteine metabolism, antioxidant capacity, and vitamin D status.
While current clinical guidelines for AUD recommend B-complex vitamins (particularly thiamine) and folic acid, there are no formal recommendations regarding vitamin D supplementation or monitoring in this population.22 Most evidence on NAC in AUD is preclinical,23-29 and to date no studies have evaluated the effect of NAC on serum 25(OH)D levels in humans. Therefore, this study assessed the effects of NAC administration on serum 25(OH)D concentrations in men with AUD during hospitalization and early abstinence.
METHODS
Study design
This is a secondary analysis of a double-blind, placebo-controlled randomized clinical trial conducted exclusively with men diagnosed with AUD.30 The sample consisted of men hospitalized for detoxification treatment at the Unidade de Adição, Hospital de Clínicas de Porto Alegre, between January 2017 and March 2020. The inclusion criteria were: age 18 to 65 years, AUD diagnosis based on DSM-5 criteria, and minimum hospitalization of 7 days. The exclusion criteria were: dependence on other substances except tobacco; serious medical conditions (hepatic, renal, or cardiac); a history of asthma or use of anticonvulsant medications; recent (< 14 days) or current use of medications potentially harmful if combined with NAC (e.g., antiretrovirals, oral corticosteroids); a history of anaphylactic reaction to NAC; suicide risk; inability to understand the informed consent form and comply with the study requirements; and any serious neuropsychiatric condition not caused by substance use, including dementia, schizophrenia, psychosis in general, multiple sclerosis, severe depression, stroke, epilepsy, or bipolar disorder.
The 9-week randomized clinical trial included 8 weeks of intervention. During the first week of hospitalization (W0), the patients were screened for eligibility based on the inclusion and exclusion criteria and were invited to participate. Clinical, psychiatric, and anthropometric data were collected during this period. A blood sample was collected on the first day of hospitalization. At the beginning of the second week of hospitalization (W1, corresponding to the eighth day of hospitalization), the intervention phase was initiated, and participants began receiving either NAC or a placebo. Blood was collected just before the intervention began.
All patients were evaluated weekly for vital signs, body mass, AUD severity, and clinical outcomes. Patients who adhered to the study protocol were reassessed at the end of the 8-week intervention (W8), at which point the administration of NAC or placebo was completed. Final clinical evaluations and body mass measurements were performed, and the third blood sample was collected.
The researchers evaluated patients once or twice a week during hospitalization, which was approximately 4 weeks, although the length of stay varied among individuals. After hospital discharge, the participants attended weekly follow-up visits at the Hospital de Clínicas de Porto Alegre outpatient clinic. During these visits, a vial containing NAC or placebo capsules was dispensed in sufficient quantity to last until the next evaluation by the research team.
Sample calculation
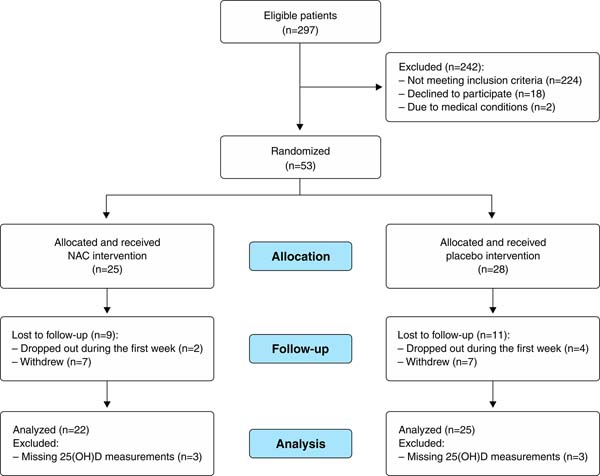
The randomized clinical trial's initial sample size was calculated based on Wu et al.,31 who assessed antioxidant levels in alcohol users (see more details in Schuch et al.30). The target sample size was set at 50 patients (25 for the placebo and 25 for the NAC group), considering an effect size of 1.093 with 80% power at a significance level (a) of 0.05 and a sample loss of 30%. The final sample size in the primary randomized clinical trial was 53 patients. For this secondary analysis, a total of 47 patients (22 from the placebo and 25 from the NAC) (Figure 1) were included. Six patients (three from each group) were excluded due to missing 25(OH)D measurements. For the primary endpoint of this study - serum 25(OH)D levels - considering SDs of 9.9 and 7.6, and a statistical significance of 5%, we estimated a power of 75.13% to detect a between-group difference of 7 ng/mL in vitamin D levels at the end of the study. This difference was considered sufficient to reflect a clinically meaningful change in vitamin D status in the study population.

Randomization, allocation concealment, and blinding
NAC or placebo was prescribed as an adjuvant therapy to conventional treatment. Capsules of the same shape and color, containing NAC or placebo, were used to ensure blinding, facilitate adherence, and complete intake of the daily dose. Patients received oral treatment with NAC 1,200 mg/day (600 mg twice daily) or placebo (magnesium stearate, colloidal silicon dioxide, sodium lauryl sulfate powder, pharmaceutical talc, and cornstarch) every 12 hours, together with breakfast or dinner, ingested with water, over a period of up to 8 weeks, in a double-blind design. During hospitalization, the nursing staff was responsible for administering the capsules.
Randomization for the drug intervention was performed using the urn method. The pharmacist responsible for the randomized clinical trial was the only unblinded member of the study team and dispensed the medication in vials labeled with the patient's name but not the treatment type (NAC or placebo). Randomization codes were obtained using the Randomizer tool (www.randomizer.org/).
For inpatients and randomized clinical trial participants, a bottle containing 14 capsules of NAC or placebo was dispensed weekly directly to the nursing department of the addiction unit. For patients in the outpatient phase, the bottle with the capsules was delivered to the patient through a study researcher responsible for weekly outpatient consultations and follow-up.
To monitor treatment adherence, the patients received a form on which they recorded whether they took the medication and at what time. In the hospitalization phase, adherence was similarly monitored through weekly capsule counts. Two researchers responded and applied a Treatment Opinion Form on a weekly basis to assess blinding integrity.
Clinical and psychiatric evaluation
Sociodemographic and anthropometric data - including race, marital status, education, occupation/employment, body mass, height, body mass index (BMI), seasonality, and age - were obtained from hospital records. Clinical data, including years of alcohol use, alcohol use in the last 30 days, number of previous hospitalizations for addiction treatment, and psychiatric comorbidities, were collected through interviews and questionnaires. The variable "seasonality," which identifies the time of year when blood was collected to assess vitamin D status, was categorized according to the four seasons.
Clinical and psychiatric assessments were conducted using a set of standardized instruments, applied either during the first week of hospitalization or weekly, depending on the characteristics and requirements of each scale. The following questionnaires were applied: Structured Clinical Interview for DSM-IV Axis I Disorders32; the sixth version of the Addiction Severity Index33,34; and the Clinical Institute Withdrawal Assessment for Alcohol scale. All clinical evaluations and applications of research instruments were collected by a physician or a researcher from the study team, respectively. These assessments were performed according to patient availability and study enrollment. All clinical, psychiatric, and psychological data were transcribed into individual case notebooks throughout the study period.
Safety procedures
The team member responsible for storing the randomization code and a member of the study team remained available 24 hours a day via mobile phone to provide guidance to study participants in the event of complications and to assess the need for unblinding. The Clinical Global Impression scale was used to assess disease severity.27 Adverse effects were evaluated using Systematic Assessment for Treatment Emergent Effects.35
Analysis of biological and anthropometric markers
Blood samples were collected after an 8-hour overnight fast, preferably via venipuncture in the forearm or another peripheral vein. Samples were drawn into tubes with and without coagulant and were then centrifuged at 1,500 rpm for 15 minutes at 4 °C. Plasma and serum samples were separated and stored at -80 °C until further analysis.
Laboratory tests were performed to evaluate liver and kidney function and vitamin D status. The tests conducted on serum samples at the three time points included 25(OH)D, gamma-glutamyl transferase, alanine aminotransferase, aspartate aminotransferase, and creatinine. All assays were performed using an automated standardized method at the hospital's clinical analysis laboratory. Serum 25(OH)D levels were analyzed using the microparticle chemiluminescent immunoassay method in an Alinity II analyzer (Abbott Diagnostics, Abbott Park, IL, USA). Vitamin D status was classified according to the cutoff points proposed in the Endocrine Society clinical practice guideline,36 which define deficiency as < 20 ng/mL, insufficiency as 21-29 ng/mL, sufficiency as > 30 ng/mL, and excess as > 150 ng/mL.
GSH peroxidase activity was measured using a commercial kit (Cayman Chemical Company, Ann Arbor, MI, USA), which assesses enzyme activity kinetics indirectly, with an absorbance reading at 340 nm. GSH disulfide (GSSG) and GSH levels were determined using a commercial kit (Sigma-Aldrich, Burlington, MA, USA). GSSG was quantified with the colorimetric method based on its reaction with 5,5'-dithiobis (2-nitrobenzoic acid) coupled to an enzymatic recycling system. GSH levels were calculated by subtracting the amount of GSSG from total GSH. All analyses were performed on plasma samples and were expressed as µmol/L for GSH and GSSG and nmol/min/mL for GSH peroxidase.
Body mass was measured using a scale (Líder P-200 C, Líder Balanças, Araçatuba, SP, Brazil; capacity: 200 kg, precision: 50 g), and height was measured using the scale's coupled stadiometer (capacity: 200 cm, precision 1 mm). Nutritional status was classified according to World Health Organization BMI cut-off points.37
Statistical analyses
Research data were entered into REDCap software. The normality of continuous variables was assessed using the Shapiro-Wilk test. Data were described as means (SD) or as median (interquartile range), depending on their distribution. Comparisons between groups (NAC vs. placebo) were performed using the Mann-Whitney test for continuous variables. Categorical variables were presented as absolute and relative frequency and were analyzed with the chi-square test. Associations between 25(OH)D and continuous variables (including body mass, BMI, aspartate aminotransferase, alanine aminotransferase, gamma-glutamyl transferase, and years of continuous alcohol use) were analyzed using Spearman correlation.
The generalized estimating equations method was used to analyze longitudinal data. In this model, the outcome variable was 25(OH)D level, and the factors included time (W0, W1, and W8), intervention group (NAC, placebo), and their interaction. Season at W0 was included in the model as a covariate to adjust for potential confounding effects.
A significance level of p < 0.05 was used for all tests. Data analysis was performed in IBM SPSS Statistics 20, and no imputation strategies were used for missing data.
Ethics statement
This study was conducted in accordance with Declaration of Helsinki guidelines, and all procedures involving human participants/patients were approved by the Hospital de Clínicas de Porto Alegre research ethics committee (15-0488, 21-0215) and were registered with ClinicalTrials.gov (NCT03018236). Written informed consent was obtained from all participants.
RESULTS
Figure 1 shows the flow of participants during the recruitment period. A total of 297 individuals with AUD were admitted, of whom 73 met the inclusion criteria. Among these, 53 were deemed eligible and were enrolled in the randomized clinical trial. A total of 47 participants were included in the present secondary analysis. Both NAC and placebo supplementation were well tolerated.
The patients' baseline characteristics (W0) are presented in Table 1. No statistically significant differences were observed between the NAC and placebo groups in terms of age, race, education, occupation, BMI, seasonality, biological markers, or alcohol use-related variables. Only marital status differed between groups, with a higher prevalence of single individuals in the NAC group than the placebo group (p = 0.023).
| NAC | Placebo | p-value | |
|---|---|---|---|
| Intervention | 22 (46.80) | 25 (53.19) | |
| Age (years), median (IQR) | 51.50 (41.00-56.00) | 53.00 (45.00-57.00) | 0.411 |
| Race (White) | 15 (68.2) | 16 (64.0) | 0.763 |
| Education | |||
| Up to high school | 2 (9.1) | 7 (28.0) | 0.144 |
| Higher education | 20 (90.9) | 18 (72.0) | |
| Marital status | |||
| Single | 19 (86.4) | 14 (56.0) | 0.023 |
| Not single | 3 (13.6) | 11 (44.0) | |
| Occupation/work | |||
| Employed | 12 (54.5) | 9 (36.0) | 0.202 |
| Without an occupation | 10 (45.5) | 16 (64.0) | |
| Vitamin D status | |||
| Deficient | 8 (36.4) | 13 (54.2) | 0.426 |
| Insufficient | 5 (22.7) | 5 (20.8) | |
| Sufficient | 9 (40.9) | 6 (25.0) | |
| BMI (kg/m2), median (IQR) | 23.41 (21.52-27.93) | 24.35 (20.95-26.57) | 0.639 |
| BMI (kg/m2) | |||
| Eutrophy | 12 (54.5) | 15 (60.0) | 0.497 |
| Pre-obesity | 7 (31.8) | 9 (36.0) | |
| Obesity class I | 3 (13.6) | 1 (4.0) | |
| Seasonality | |||
| Fall | 7 (31.8) | 8 (32.0) | 0.937 |
| Winter | 5 (22.7) | 6 (24.0) | |
| Spring | 3 (13.6) | 2 (8.0) | |
| Summer | 7 (31.8) | 9 (36.0) | |
| Creatinine (mg/dL), median (IQR) | 0.85 (0.79-0.99) | 0.85 (0.74-0.96) | 0.515 |
| GGT (U/L), median (IQR) | 84.50 (63.50-134.50) | 93.00 (50.50-191.50) | 0.909 |
| AST (U/L), median (IQR) | 38.50 (23.50-88.25) | 53.00 (24.00-99.50) | 0.831 |
| ALT (U/L), median (IQR) | 40.00 (23.00-75.75) | 38.00 (20.00-68.00) | 0.701 |
| GPx (nmol/min/mL), median (IQR) | 67.98 (42.69-80.63) | 56.05 (49.71-74.91) | 0.456 |
| GSH/GSSG (µmol/L), median (IQR) | 5.87 (2.75-9.90) | 3.66 (1.82-7.61) | 0.241 |
| Number of previous hospitalizations, median (IQR) | 2.50 (1.00-4.25) | 3.00 (1.00-7.50) | 0.264 |
| Years of alcohol use, median (IQR)┼ | 25.50 (9.50-35.00) | 21.00 (12.50-32.00) | 0.760 |
| Alcohol use in the last 30 days, median (IQR)╬ | 25.00 (13.75-30.00) | 30.00 (25.75-30.00) | 0.087 |
| ASI-6 - Alcohol, median (IQR) | 63.00 (58.00-68.75) | 69.00 (60.00-75.00) | 0.151 |
| CIWA - Ar, median (IQR) | 3.00 (1.00-6.50) | 3.00 (0.75-6.00) | 0.869 |
Data presented as n (%), unless otherwise specified.
Bold type denotes statistical significance.
Absolute frequency (relative frequency) data evaluated with the chi-square test; median (interquartile range) data assessed with the Mann-Whitney test.
ALT = alanine aminotransferase; ASI-6 - Alcohol = Addiction Severity Index - Alcohol (score related to alcohol use); AST = aspartate aminotransferase; AUD = alcohol use disorder; CIWA - Ar = Clinical Institute Withdrawal Assessment for Alcohol scale (highest score on the first day of hospitalization); GGT = gamma-glutamyl transferase; GPx = glutathione peroxidase; GSH/GSSG = glutathione/glutathione disulfide; NAC = N-acetylcysteine; W = week.
┼ Defined as years of life regularly consuming alcohol 3 or more days a week.
╬ Defined as number of days they consumed alcohol in the last month.
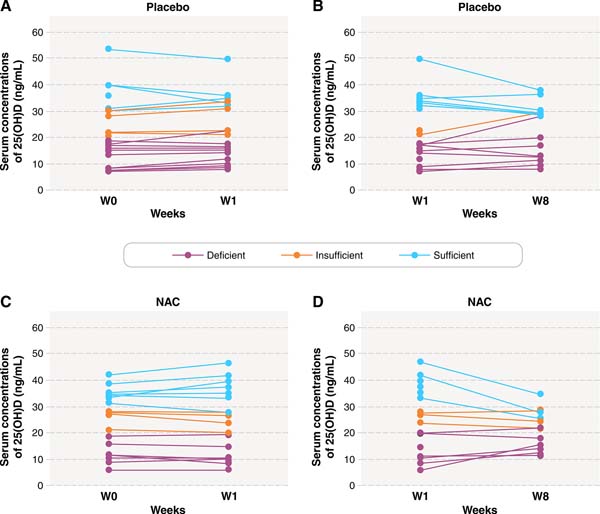
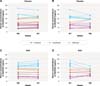
None of the participants took vitamin D supplements during the study period. Vitamin D status at W0 was similar between the NAC and placebo groups (p = 0.426) (Table 1). Likewise, no significant differences in 25(OH)D levels were observed between groups at W0 (p = 0.244), W1 (p = 0.411), and W8 (p = 0.999). Figure 2 presents the classification of 25(OH)D levels for each participant in both groups, which were categorized as sufficient, insufficient, or deficient. Additionally, 25(OH)D levels at W0 and W1 were compared between participants who completed the study and those who did not (adherence to W8 follow-up), but no significant differences were observed (p > 0.05).
The influence of race and seasonality on 25(OH)D levels was assessed. Race (White vs. non-White) was not significantly associated with 25(OH)D level at any time point: W0 (p = 0.937), W1 (p = 0.686), or W8 (p = 0.574). In contrast, seasonality at hospital admission (W0) was associated with 25(OH)D level (p = 0.010): individuals admitted during the winter had lower 25(OH)D levels (md = 15.80 ng/mL) than those admitted during the summer (md = 28.75 ng/mL, p = 0.043) (Supplementary Table S1).
There were no significant differences in biological markers between the NAC and placebo groups (Table 1). Therefore, correlation analyses were performed using the total sample of individuals with AUD at each time point (Table 2). There was a significant correlation between 25(OH)D level and aspartate aminotransferase level at W1 (r = -0.380, p = 0.014) and years of alcohol use at W8 (r = 0.383, p = 0.037). However, no significant correlations were observed between 25(OH)D level and GSH-related parameters at W0, W1, or W8.
| Variable | W0 25(OH)D ng/mL | W1 25(OH)D ng/mL | W8 25(OH)D ng/mL |
|---|---|---|---|
| Body mass (kg) | -0.024 (0.873) | 0.054 (0.733) | -0.019 (0.919) |
| BMI (kg/m2) | -0.022 (0.884) | 0.044 (0.780) | -0.054 (0.778) |
| Creatinine (mg/dL) | 0.173 (0.251) | 0.071 (0.664) | -0.006 (0.975) |
| GGT (U/L) | -0.231 (0.132) | -0.102 (0.532) | -0.070 (0.715) |
| AST (U/L) | -0.188 (0.210) | -0.380 (0.014) | -0.043 (0.823) |
| ALT (U/L) | -0.050 (0.742) | -0.155 (0.335) | -0.228 (0.226) |
| GPx (nmol/min/mL) | 0.203 (0.176) | 0.126 (0.434) | 0.126 (0.507) |
| GSH/GSSG (µmol/L) | 0.027 (0.866) | -0.065 (0.696) | 0.129 (0.496) |
| Years of alcohol use┼ | 0.220 (0.157) | 0.304 (0.060) | 0.383 (0.037) |
| Alcohol use in the last 30 days╬ | -0.011 (0.946) | 0.025 (0.881) | -0.072 (0.705) |
| ASI - Alcohol | 0.037 (0.815) | 0.054 (0.745) | -0.073 (0.702) |
Bold type denotes statistical significance.
Spearman correlation (p < 0.05).
25(OH)D = 25-hydroxyvitamin D; ASI - Alcohol = Addiction Severity Index - Alcohol (score related to alcohol use); AST = aspartate aminotransferase; AUD = alcohol use disorder; BMI = body mass index; GGT = gamma-glutamyl transferase; GPx = glutathione peroxidase; GSH/GSSG = glutathione/glutathione disulfide; W = week.
┼ Defined as years of life regularly consuming alcohol 3 or more days a week, 5 or more drinks per day.
╬ Defined as number of days they consumed alcohol in the last month.

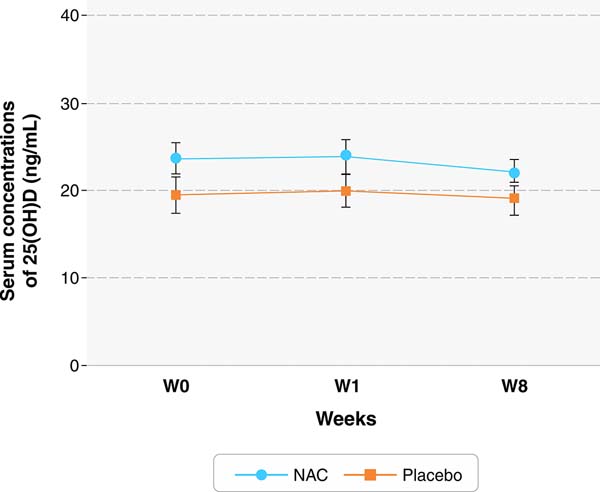
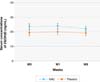
Figure 3 shows the mean serum 25(OH)D concentrations over time for the NAC and placebo groups. Neither the intervention group (p = 0.130), study time (p = 0.429), nor the interaction between these two factors (p = 0.834), had a significant effect on 25(OH)D levels in the AUD group.
DISCUSSION
This is the first randomized clinical trial to investigate the effects of NAC on serum 25(OH)D levels in individuals with AUD. Only one study has evaluated 25(OH)D levels in individuals with AUD, but it did not include NAC as an intervention.38 Our findings do not support the hypothesis that NAC influences serum levels of 25(OH)D. In this 8-week clinical trial administering NAC 1,200 mg/day, no significant changes were observed in mean 25(OH)D levels in patients treated with NAC or placebo at the end of the intervention.
Our study found a 66.7% prevalence of vitamin D insufficiency/deficiency prior to NAC treatment, corroborating similar findings of high rates of 25(OH)D deficiency and insufficiency among individuals with AUD,38-41 including rates up to 90% in adolescents.39 A Nepalese study of adult AUD patients of both sexes admitted to treatment centers for alcohol and drugs reported a 64% prevalence of 25(OH)D deficiency and identified an association between 25(OH)D deficiency and AUD severity.40 Our findings also align with Mobarhan et al.,38 who observed no spontaneous improvement in 25(OH)D levels after a period of alcohol abstinence. These results reinforce the importance of monitoring vitamin D status and evaluating the need for therapeutic supplementation with vitamin D in patients with AUD, both during and after treatment.
Evidence regarding the relationship between occasional or chronic alcohol consumption and serum 25(OH)D levels remains inconclusive.6 In our study, there was a positive correlation between years of alcohol use and 25(OH)D level in the final week of the study. However, this finding contrasts with other results involving 25(OH)D concentration and aspects related to alcohol use observed in our study. Individuals with the same (or similar) years of alcohol use may have distinct periods of heavy consumption, representing a wide heterogeneity in consumption.
Patients with AUD commonly present liver lesions and altered oxidative stress markers.23 GSH is a critical endogenous antioxidant, primarily synthesized in the liver. NAC, a precursor to cysteine, appears to be an option for alleviating drug-induced liver injury and increasing GSH synthesis.42 A study of diabetic patients without AUD found a positive correlation between serum levels of 25(OH)D, L-cysteine, and GSH.21In vitro and in vivo preclinical studies have also found increased GSH and 25(OH)D levels following cysteine supplementation.20 To date, no studies have evaluated the relationship between GSH or the GSH/GSSG ratio and vitamin D status in patients with AUD. In our randomized clinical trial, NAC administration did not influence GSH levels or the GSH/GSSG ratio.
Our study observed a negative correlation between 25(OH)D and aspartate aminotransferase levels after the first week of abstinence. This finding aligns with previous research. For instance, Darvishi-Khezri et al.43 reported that elevated aspartate aminotransferase is an independent risk factor for vitamin D insufficiency in patients with ß-thalassemia without AUD. Similarly, there was a negative correlation between these markers in patients with non-alcoholic hepatic steatosis.44 Moreover, vitamin D supplementation has been associated with reduced production of pro-fibrinogenic cytokines, while vitamin D deficiency is recognized as a risk factor for liver fibrosis.45 However, one study observed that vitamin D supplementation in non-alcoholic fatty liver disease did not improve liver function or glycemic and lipid markers.46 In our study, the alanine aminotransferase and gamma-glutamyl transferase markers, which have higher specificity in assessing liver function, did not significantly correlate with vitamin D levels.
Some factors are known to interfere with 25(OH)D level, such as BMI, sun exposure, and seasonality. In our study, BMI increased slightly over the treatment period but remained similar between the groups (data not shown). Patients with AUD are more prone to conditions such as sarcopenic obesity, edema, and ascites.47,48 Obesity is a recognized risk factor in vitamin D deficiency, supposedly due to greater retention in adipose tissue and its fat-soluble characteristics.49 Nevertheless, no significant changes in vitamin D status were observed throughout the intervention. Additionally, there were no significant correlations between BMI and 25(OH)D level at the three time points.
Despite evidence from preclinical models, some factors may explain NAC's lack of influence on 25(OH)D levels. The duration and/or dosage of NAC treatment may have been insufficient to produce measurable changes, including a possible restoration of liver function, which could aid vitamin D synthesis. Moreover, multiple and combined factors regulate vitamin D metabolism and could interfere with the interaction between NAC and 25(OH)D levels. For instance, factors that may interfere with vitamin D absorption and conversion include insufficient sun exposure,50,51 hospitalization, the amount of exposed skin,52 skin pigmentation,53 ethnicity,50,51 and baseline vitamin D status.54 In our study, were able to assess race and seasonality. Although race was not associated with 25(OH)D concentration, seasonality did appear to influence these levels, particularly at W0. This difference was most pronounced between winter and summer, likely due to variations in solar radiation. In adolescents with and without AUD, lower levels of 25(OH)D were observed in those with AUD across all seasons.39 Moreover, it was suggested that the AUD group may have had less sun exposure depending on the hospitalization period. In an Australian study, only 6% of the individuals dependent on alcohol and other drugs were vitamin D deficient. However, Australia has a high incidence of sunlight, and all patients received a multivitamin supplement, including vitamin D, prior to recruitment.55
Despite the methodological rigor of the clinical trial, some limitations should be mentioned. The study included only male inpatients with a severe clinical condition, which limits the generalizability of the findings to other populations, such as women, individuals with milder AUD, or those in outpatient care, since treatment characteristics, settings, and other factors may differ significantly between populations. Additionally, factors known to impact vitamin D concentrations, such as physical activity and sun exposure during the intervention,50,51,56,57 dietary intake of vitamin D, and use of nutritional supplements7 were not assessed and could be a confounding factor regarding serum 25(OH)D levels. Moreover, the study was conducted in southern Brazil, where solar incidence can differ from other locations in the country. Finally, the study's sample size and power are important considerations when interpreting the findings. Although the sample size was calculated a priori based on previous studies, the actual power was 75.13%, slightly below the conventional threshold of 80%. This moderate power level implies a non-negligible risk of type II error, meaning that small but potentially relevant effects of NAC on vitamin D status may not have been detected. Therefore, our negative findings - specifically, the lack of significant difference between NAC and placebo groups - should be interpreted with caution. Future studies with larger samples are necessary to confirm or refute these observations.
In conclusion, we observed a high prevalence of 25(OH)D deficiency and insufficiency among individuals with AUD, which was not significantly affected by NAC administration or alcohol abstinence during the hospitalization and follow-up period. These negative findings have important clinical implications, indicating that neither spontaneous recovery during withdrawal nor antioxidant therapy with NAC is sufficient to restore adequate vitamin D levels in this population. This underscores the need for proactive clinical interventions, including routine monitoring of serum vitamin D levels in patients with AUD, as hypovitaminosis D may persist even after cessation of alcohol consumption. The lack of a spontaneous increase in 25(OH)D during withdrawal, along with the lack of effect from NAC, suggests that direct vitamin D supplementation should be considered as an integral part of the therapeutic approach for these individuals, especially to prevent metabolic, musculoskeletal, and hepatic comorbidities. Therefore, assessing and correcting vitamin D status represents a simple, accessible, and potentially effective clinical strategy in multidisciplinary care for individuals with AUD.
SUPPLEMENTARY MATERIALS
ACKNOWLEDGEMENTS
The study was supported by Secretaria Nacional de Políticas Sobre Drogas (grant 08129.011787/2015-95), Fundo de Incentivo à Pesquisa e Eventos - Hospital de Clínicas de Porto Alegre (grant 2015-0488), and Coordenação de Aperfeiçoamento de Pessoal de Nível Superior (Finance Code 01).
 PDF
 Print
 Send this article by email
 How to cite this article
 Submit a comment
 Mendeley
 Pocket
 Share on Facebook
 Share on Twitter



